Highlight
- Tocilizumab initiation in giant cell arteritis (GCA) patients is associated with significantly fewer major adverse cardiovascular events (MACE) compared to methotrexate.
- The reduction in MACE primarily stems from decreased coronary events and all-cause mortality over two years.
- This large-scale, nationwide study used a target trial emulation approach to provide real-world evidence on cardiovascular outcomes linked to steroid-sparing therapies in GCA.
Study Background
Giant cell arteritis (GCA) is a systemic vasculitis predominantly affecting large- and medium-sized arteries, often seen in older adults. Clinical manifestations include headache, visual disturbances, and jaw claudication, with potential severe complications such as vision loss and aortic aneurysm. Importantly, GCA is associated with an elevated risk of cardiovascular events, including coronary artery disease and stroke, largely attributed to chronic inflammation and accelerated vascular injury. Standard treatment relies heavily on glucocorticoids, which, despite efficacy, carry significant cardiovascular and metabolic side effects. Consequently, steroid-sparing agents like tocilizumab, an interleukin-6 receptor antagonist, and methotrexate, a conventional immunosuppressant, have been increasingly utilized to mitigate long-term steroid exposure. However, it remains unclear whether these therapies differ in their impact on cardiovascular outcomes in GCA patients.
Study Design
This observational cohort study, conducted using the comprehensive French National Health Data System, emulated a randomized target trial to compare cardiovascular outcomes in newly diagnosed GCA patients initiating tocilizumab versus methotrexate. The study period extended from January 1, 2012, through December 31, 2024. Inclusion criteria encompassed patients hospitalized for incident GCA who commenced either tocilizumab or methotrexate treatment within six months after hospital discharge.
The primary endpoint was the occurrence of the first major adverse cardiovascular event (MACE), defined as a composite of coronary events, ischemic stroke, or all-cause mortality. To minimize immortal time bias and confounding, the investigators applied a clone-censor-weight approach incorporating inverse probability of censoring weighting. Cumulative incidences over two years, absolute risk differences, and hazard ratios (HR) with 95% confidence intervals (CI) were calculated. Multiple sensitivity analyses tested the robustness of findings.
Key Findings
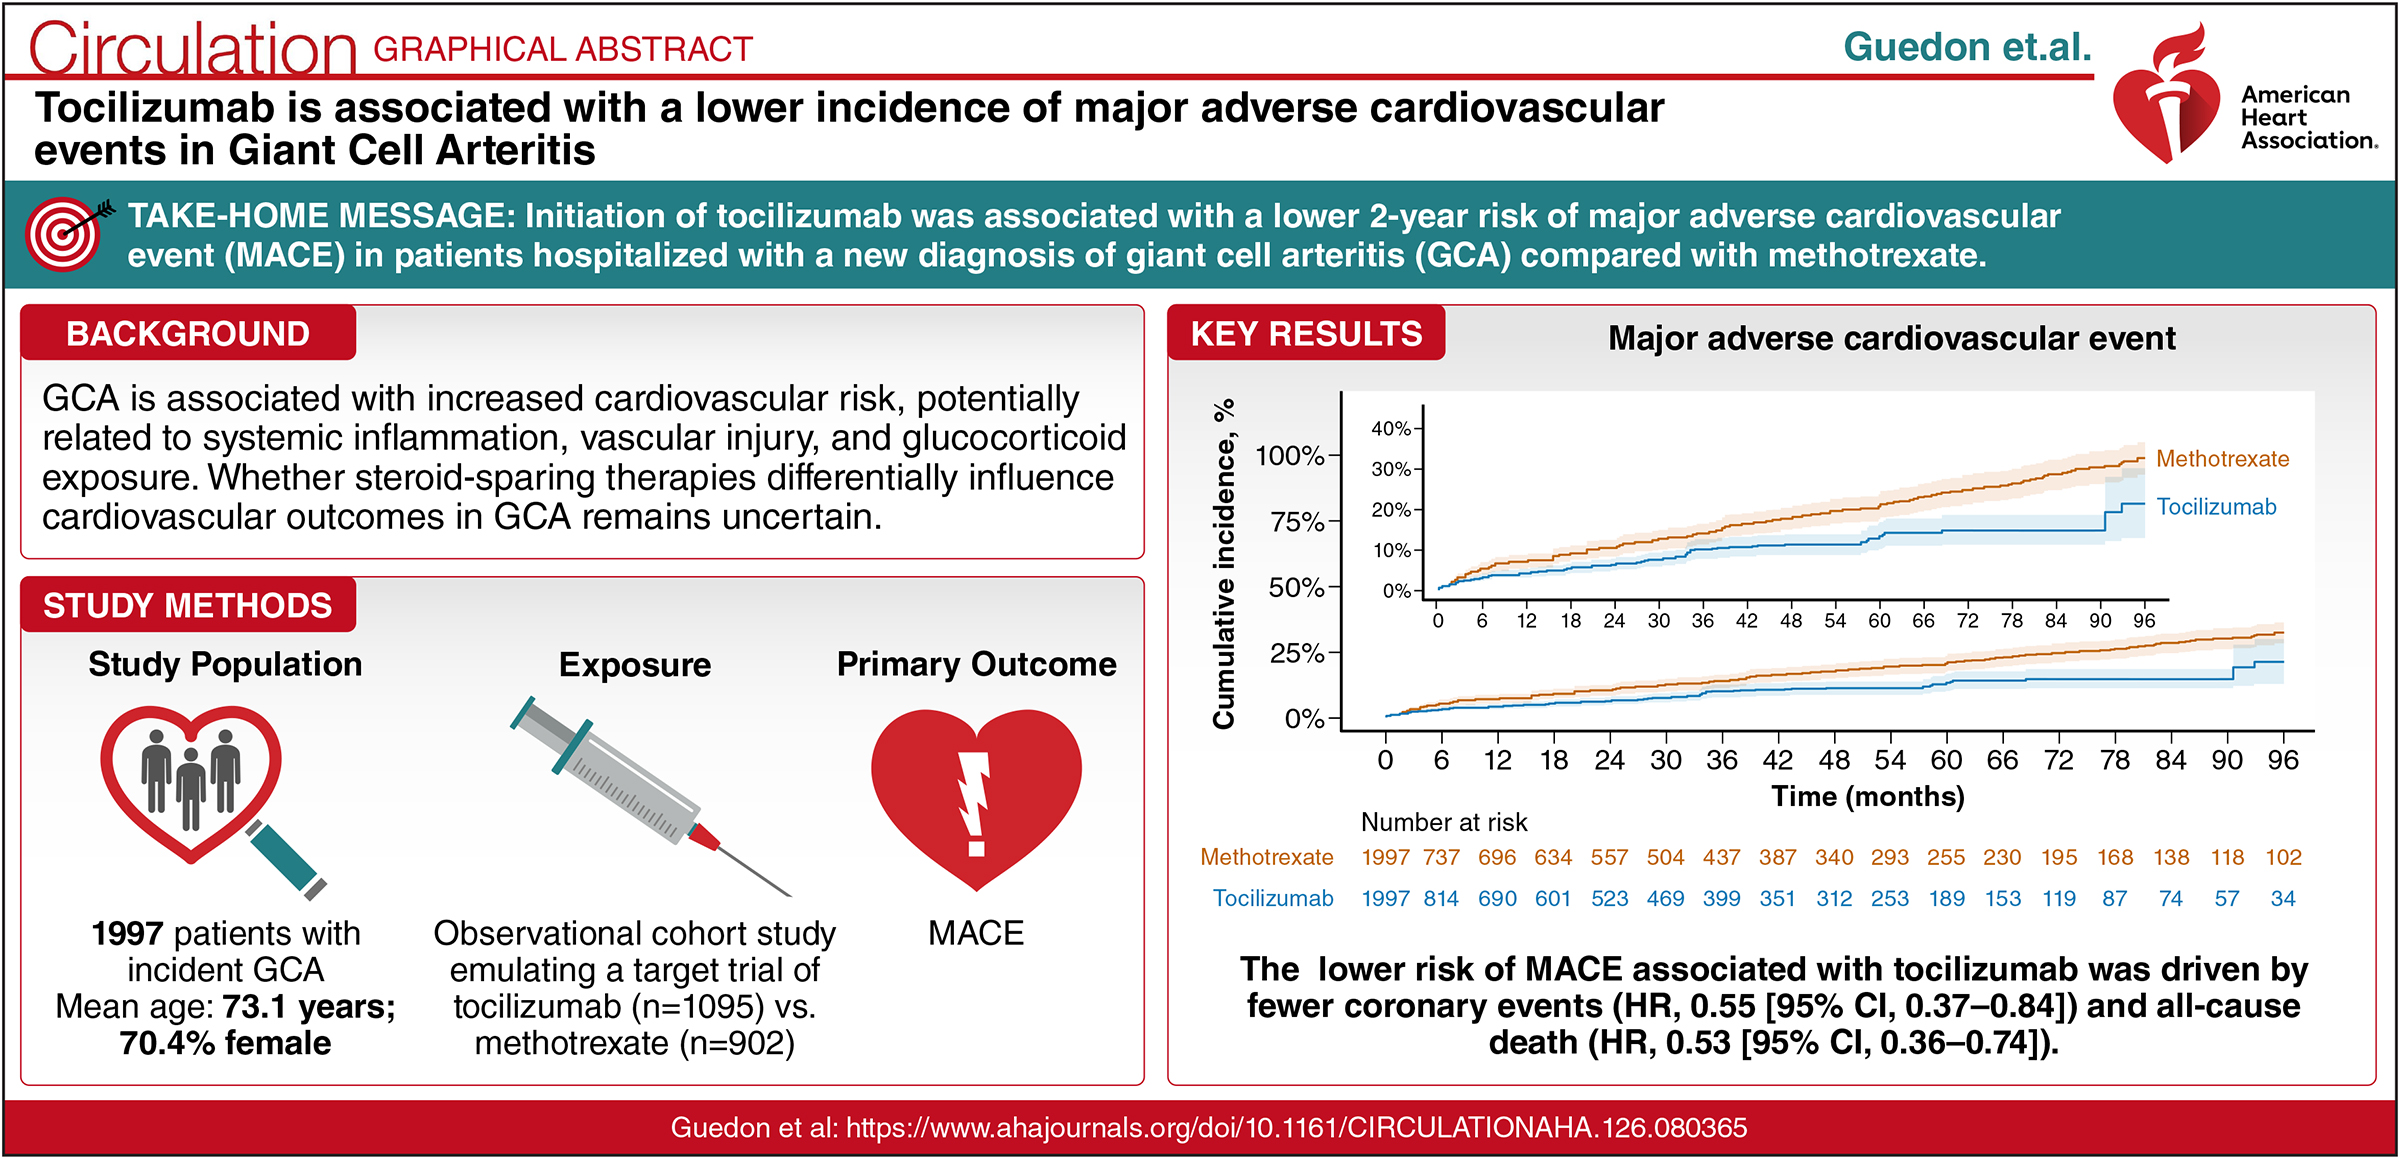
The study cohort comprised 1997 patients (mean age 73.1 ± 8.3 years; 70.4% women), with 1095 initiating tocilizumab and 902 initiating methotrexate within 6 months post-discharge. Over two years, the cumulative incidence of MACE was significantly lower among the tocilizumab group (6.4%; 95% CI, 4.9%-7.9%) compared to the methotrexate group (10.7%; 95% CI, 8.4%-12.9%), reflecting a risk difference of -4.3% (95% CI, -6.6% to -1.7%).
The adjusted hazard ratio for MACE with tocilizumab initiation was 0.60 (95% CI, 0.48-0.75), indicating a 40% risk reduction relative to methotrexate. This protective effect was primarily driven by fewer coronary events (HR 0.55; 95% CI, 0.37-0.84) and reduced all-cause mortality (HR 0.53; 95% CI, 0.36-0.74). The incidence of ischemic stroke did not differ significantly between groups.
Sensitivity analyses, including adjustments for glucocorticoid doses, varying treatment initiation grace periods, restriction to the more recent 2017–2024 period, and per-protocol-like analyses, consistently supported the primary findings. Negative control outcomes, used to assess residual confounding, showed no significant differences, enhancing confidence in the validity of the observed associations.
Expert Commentary
These findings add important real-world evidence supporting tocilizumab’s potential cardiovascular benefits in GCA beyond its anti-inflammatory efficacy. Chronic systemic inflammation in GCA promotes endothelial dysfunction and accelerates atherosclerosis, plausibly mitigated by interleukin-6 blockade. The observed reduction in coronary events aligns with mechanistic insights linking IL-6 pathway inhibition to improved vascular health. By contrast, methotrexate’s impact on cardiovascular risk appears less favorable or neutral in this population.
Limitations include the observational design with inherent residual confounding risk despite rigorous analytic methods. The findings are specific to a French healthcare context, which may limit generalizability. Further randomized controlled trials or prospective studies are warranted to confirm causality and explore the potential for tocilizumab to become preferred steroid-sparing therapy in GCA with cardiovascular risk mitigation as a key consideration.
Conclusion
In patients with newly diagnosed giant cell arteritis, tocilizumab initiation within six months of diagnosis is associated with a significantly lower incidence of major adverse cardiovascular events compared with methotrexate treatment. This benefit is mainly attributable to reductions in coronary events and overall mortality, underscoring tocilizumab’s role as a steroid-sparing agent that may also confer cardiovascular protection. These findings may inform therapeutic decision-making and risk stratification strategies in clinical practice.
Funding and Registration
The study was registered on ClinicalTrials.gov (identifier NCT07459335). Details on funding sources were not disclosed in the provided abstract but should be reviewed in the full published article.
References
1. Guedon AF, Cacoub P, Carrat F, et al. Tocilizumab Is Associated With a Lower Incidence of Major Adverse Cardiovascular Events in Giant Cell Arteritis. Circulation. 2026 Aug 29. PMID: 42667206.
2. Weyand CM, Goronzy JJ. Giant-cell arteritis and polymyalgia rheumatica. N Engl J Med. 2014 Jul 3;371(1):50-7.
3. Stone JH, Tuckwell K, Dimonaco S, et al. Trial of Tocilizumab in Giant-Cell Arteritis. N Engl J Med. 2017 Jul 27;377(4):317-328.
4. Nicola PJ et al. Cardiovascular disease risk in patients with giant cell arteritis: A population-based cohort study. Arthritis Rheumatol. 2020;72(9):1572-1580.