Highlight
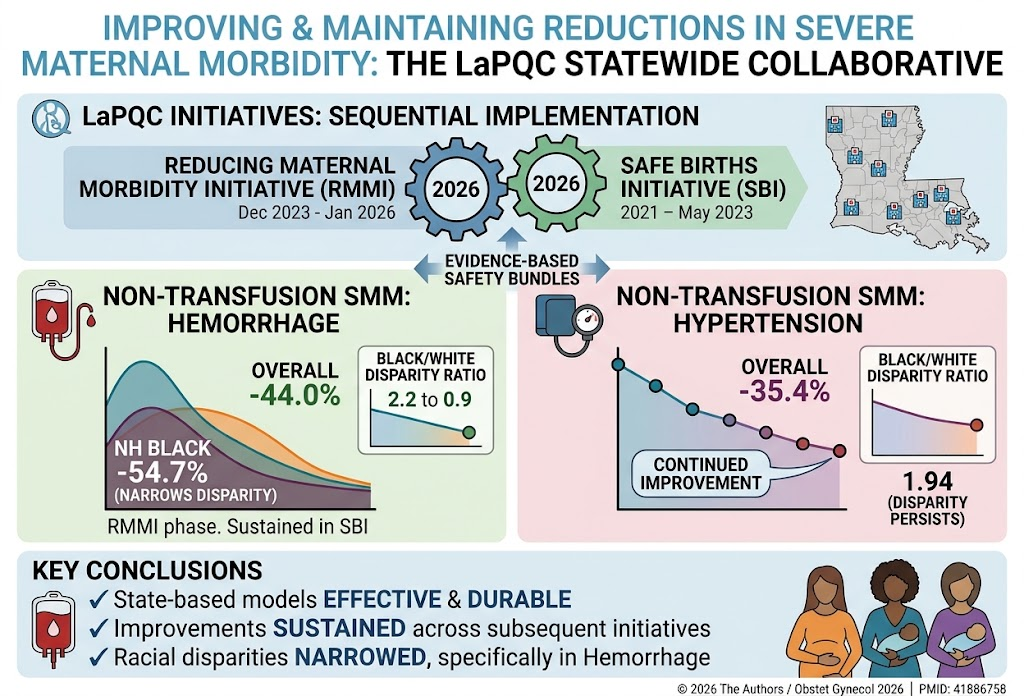
- Implementation of a statewide Perinatal Quality Collaborative (LaPQC) in Louisiana significantly reduced severe maternal morbidity (SMM) related to hemorrhage and hypertensive disorders.
- Two sequential quality improvement initiatives—Reducing Maternal Morbidity Initiative and Safe Births Initiative—achieved and maintained these improvements over multiple years.
- Marked reduction in racial disparities in hemorrhage-related SMM was observed, particularly among non-Hispanic Black individuals, with the Black/White disparity ratio narrowing substantially.
- Hypertension-related SMM also declined, though some racial disparities persisted by the end of the study period.
Study Background
Severe maternal morbidity (SMM)—life-threatening conditions related to pregnancy and childbirth—remains a critical public health issue in the United States. Hemorrhage and hypertensive disorders are among the leading contributors to SMM and maternal mortality. Despite advances in obstetric care, Louisiana has faced historically high rates of maternal complications and significant racial disparities, with non-Hispanic Black women disproportionately affected.
Perinatal Quality Collaboratives (PQCs) bring together multidisciplinary stakeholders to implement evidence-based safety bundles, improve clinical processes, and reduce adverse maternal outcomes at scale. Louisiana’s Perinatal Quality Collaborative (LaPQC) aimed to address severe maternal morbidity statewide through targeted quality improvement initiatives.
Study Design
The LaPQC implemented two sequential statewide quality improvement projects targeting hemorrhage and hypertension-related SMM: the Reducing Maternal Morbidity Initiative (August 2018-May 2020) and the Safe Births Initiative (January 2021-September 2022). Thirty-one birthing hospitals in Louisiana continuously participated in both projects.
Data on nontransfusion severe maternal morbidity indicators related to hemorrhage and hypertensive disorders were collected from the Louisiana Hospital Inpatient Discharge Database. Rates per 10,000 delivery hospitalizations were calculated quarterly. The study analyzed hospital-level aggregate data using percent change and Joinpoint regression to evaluate temporal trends.
Process measures incorporated in the interventions included accurate quantification of blood loss, systematic hemorrhage risk assessment, and timely treatment protocols for hypertensive emergencies. Collaborative learning methods and rapid response cycles underpinned the quality improvement efforts.
Key Findings
During the Reducing Maternal Morbidity Initiative, the overall rate of nontransfusion SMM related to hemorrhage decreased dramatically by 44.0%, falling from 1,162.4 to 650.8 per 10,000 deliveries by the second quarter of 2020.
Among non-Hispanic Black individuals, this decline was even more pronounced, with a 54.7% decrease—from 1,630.0 to 737.7 per 10,000 deliveries. This improvement narrowed the racial disparity ratio between Black and White patients from 2.2 at baseline to 0.9 by Q2 2020, effectively eliminating the disparity in hemorrhage-related morbidity during this period.
Crucially, these gains were sustained into and throughout the Safe Births Initiative, with overall hemorrhage-related SMM remaining 39.0% lower than baseline and 58.2% lower among Black women by the end of the study period in Q3 2022.
For hypertension-related SMM, the initial initiative achieved a reduction of 14.1% (847.5 to 727.6 per 10,000 deliveries by Q2 2020), with continued improvement during the Safe Births Initiative culminating in a 35.4% reduction by Q3 2022. However, unlike hemorrhage outcomes, the Black/White disparity ratio in hypertension-related SMM persisted at 1.94 by the conclusion of the study.
Expert Commentary
These findings substantiate the effectiveness of statewide Perinatal Quality Collaboratives in addressing severe maternal morbidity through structured, evidence-based bundled care and rapid-cycle improvement. The robustness of data collection, hospital engagement, and focus on both process and outcome metrics contributed to these durable improvements.
Of particular importance is the significant attenuation of racial disparities in hemorrhage-related morbidity, a historically challenging area. The persistent disparities seen in hypertension-related SMM highlight the complexity of hypertensive disorders in pregnancy and may suggest a need for additional focused interventions addressing social determinants and preconception care.
Limitations include the observational design and aggregate hospital-level data, which may obscure individual patient-level factors. Additionally, the study’s applicability beyond Louisiana’s unique healthcare landscape warrants further investigation.
Conclusion
The Louisiana Perinatal Quality Collaborative demonstrated that statewide implementation of standardized, evidence-based safety bundles with active data monitoring can substantially reduce severe maternal morbidity and diminish racial disparities in hemorrhage outcomes. The ability to sustain improvements across multiple initiatives reinforces the value of collaborative quality improvement infrastructure in perinatal care.
Ongoing efforts should prioritize closing remaining gaps in hypertensive morbidity and expanding these models to other regions. Integration of patient-centered approaches and addressing broader systemic inequities will be key to further enhancing maternal health equity.
Funding and Clinical Trials
The study supported by the Louisiana Perinatal Quality Collaborative’s infrastructure; specific funding details were not provided. No clinical trial registration number was reported.
References
1. Admon LK, Winkelman TNA, McKiever ME, et al. National and State Trends in Severe Maternal Morbidity Among Delivery Hospitalizations, 2012–2018. Matern Child Health J. 2022;26(6):1153-1161.
2. Main EK, McCain CL, Morton CH, et al. Pregnancy-related mortality in California: causes, characteristics, and improvement opportunities. Obstet Gynecol. 2015;125(4):938-947.
3. Austin DE, Janik MK, Skelton JB, et al. Implementation of a Severe Hypertension Safety Bundle in a Health Care System. Obstet Gynecol. 2020;136(5):969-977.
4. Howell EA, Egorova N, Balbierz A, Zeitlin J, Hebert PL. Black-White Differences in Severe Maternal Morbidity and Site of Care. Am J Obstet Gynecol. 2016;214(1):122.e1-122.e7.
5. Clark SL, Belfort MA, Dildy GA, et al. Improved outcomes from severe obstetric hemorrhage using a standardized management protocol. Am J Obstet Gynecol. 2013; 208(1):42.e1-42.e8.
6.Gillispie-Bell V, Wallace K. Improving and Maintaining Reductions in Severe Maternal Morbidity Through a Statewide Perinatal Quality Collaborative. Obstet Gynecol. 2026 Sep 1;148(3):e169-e176. doi: 10.1097/AOG.0000000000006269. Epub 2026 Mar 26. PMID: 41886758; PMCID: PMC13480315.