Hematoma Location as a Key Modifier of Intensive Blood Pressure Lowering Outcomes in Acute Intracerebral Hemorrhage
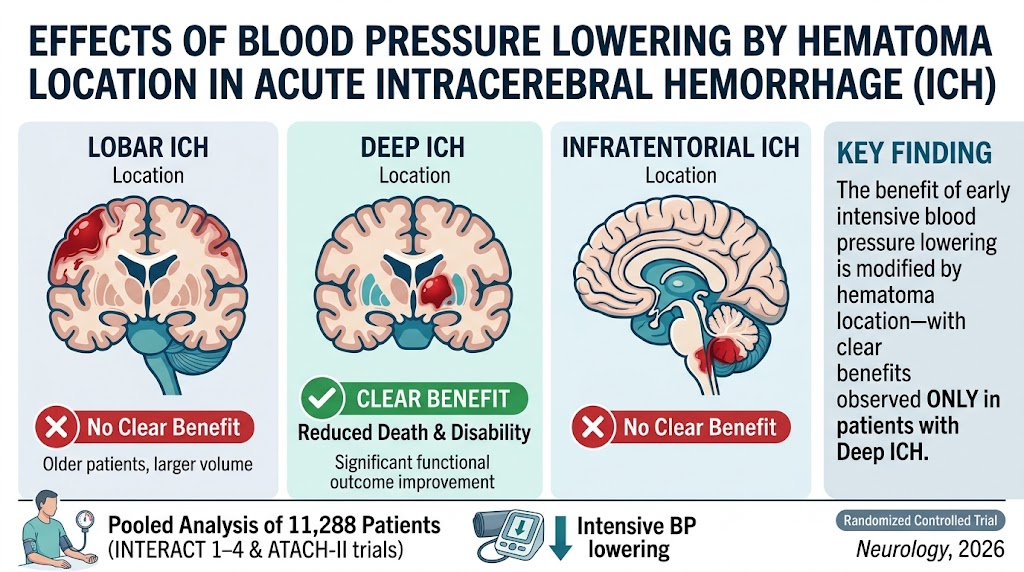
Highlight
- Intensive blood pressure (BP) lowering improves functional outcomes after acute intracerebral hemorrhage (ICH), but the benefit varies by hematoma location.
- Analysis of 11,288 patients shows treatment benefit is significant only in deep hemisphere hemorrhages.
- Lobar ICH patients tend to be older with larger hematoma volumes and less benefit from intensive BP lowering.
- Hematoma location should be considered in clinical decision-making around BP management in acute ICH.
Study Background
Acute intracerebral hemorrhage (ICH), a subtype of stroke caused by bleeding within the brain parenchyma, accounts for a substantial proportion of stroke-related morbidity and mortality worldwide. Early intensive blood pressure management is increasingly recognized as a critical intervention aimed at minimizing hematoma expansion and improving clinical outcomes. However, ICH is a heterogeneous condition with hematomas occurring in different brain locations—lobar, deep hemispheric, and infratentorial—that exhibit distinct pathophysiologic mechanisms, clinical presentations, and prognoses. This heterogeneity raises the question of whether the benefits of intensive blood pressure lowering are consistent across hematoma locations or if treatment effects vary. Resolving this uncertainty has important implications for personalized clinical management strategies to optimize functional recovery and survival after ICH.
Study Design and Methods
A pooled individual patient-level data (IPD) analysis was conducted using data from all four Intensive Blood Pressure Reduction in Acute Cerebral Hemorrhage Trials (INTERACT1, INTERACT2, INTERACT3, INTERACT4) and the second Antihypertensive Treatment of Acute Cerebral Hemorrhage (ATACH-II) trial. All trials were international, randomized, open-label, controlled studies with blinded endpoint assessment evaluating early intensive blood pressure control interventions against standard care in patients with acute ICH.
The analysis included 11,288 patients with confirmed ICH classified objectively based on hematoma location: lobar (cortical/subcortical), deep hemispheric (basal ganglia, thalamus), or infratentorial (brainstem and cerebellum). Key clinical variables, such as age, hematoma volume, and presence of intraventricular hemorrhage (IVH), were carefully documented and controlled for in statistical models.
The primary outcome was death or major disability at 90 days post-ICH (or 6 months for INTERACT3), defined by a modified Rankin Scale (mRS) score of 3 to 6. Treatment effects by hematoma location were examined using generalized linear mixed models incorporating a “treatment-by-location” interaction term and trial as a random effect to account for between-study variability.
Key Findings
Among the 11,288 patients analyzed, 10.1% had lobar ICH, 81.5% had deep hemispheric ICH, and 8.4% had infratentorial ICH. Patients with lobar ICH were noted to be older, had larger hematoma volumes, and a lower frequency of IVH compared to the other locations (all p < 0.001).
Critically, the benefit of intensive blood pressure lowering on the primary endpoint varied significantly by hematoma location (p for interaction = 0.033). Intensive BP lowering conferred a statistically robust reduction in death or disability only in patients with deep hemispheric hemorrhages, with an adjusted odds ratio (OR) of 0.81 (95% CI, 0.74–0.89; p < 0.001). No significant benefit was demonstrated in lobar or infratentorial hemorrhages.
These results suggest that intensive blood pressure lowering selectively mitigates secondary injury processes in deep hemorrhages, potentially by reducing hematoma expansion or perihematomal edema more effectively in these regions, whereas the pathophysiology or therapeutic responsiveness in lobar and infratentorial hemorrhages may be less favorable for this approach.
Expert Commentary
The differential impact of blood pressure control based on hematoma location underscores the biological and clinical heterogeneity inherent to ICH. Deep hemorrhages often result from hypertensive arteriopathy affecting small penetrating vessels, whereas lobar hemorrhages may be associated with cerebral amyloid angiopathy or other structural pathologies, which might render BP lowering less effective.
This pooled IPD meta-analysis leverages large-scale robust clinical trial data, enhanced by harmonized outcome assessment and adjustment for confounders, to clarify an important clinical question with direct therapeutic implications. However, limitations include potential residual confounding and the relatively smaller sample sizes in lobar and infratentorial groups reducing power to detect more modest benefits.
Current guidelines could consider these findings to refine clinical recommendations, advocating for aggressive blood pressure control particularly in deep ICH patients, while suggesting a more individualized approach in lobar and infratentorial cases. Further research is needed to elucidate mechanistic underpinnings and evaluate adjunctive therapies that may improve outcomes in non-deep hemorrhages.
Conclusion and Clinical Implications
This comprehensive analysis of multiple high-quality randomized controlled trials demonstrates that hematoma location significantly modifies the effectiveness of intensive blood pressure lowering in acute intracerebral hemorrhage. Specifically, patients with deep hemispheric ICH derive clear functional benefit from intensive BP reduction, whereas those with lobar or infratentorial hemorrhages do not show a similar advantage.
These findings advocate for a precision medicine approach in acute ICH management, integrating hematoma location as a key factor when considering blood pressure targets. Personalized treatment algorithms could optimize outcomes and resource utilization in this challenging neurological emergency.
Funding and Trial Registration
These trials received funding from multiple international health agencies and philanthropic organizations. The studies are registered at ClinicalTrials.gov with identifiers INTERACT1 (NCT00226096), INTERACT2 (NCT00716079), INTERACT3 (NCT03209258), INTERACT4 (NCT03790800), and ATACH-II (NCT01176565).
References
1. Ren X, Chen X, Hu X, et al. Effects of Blood Pressure Lowering by Hematoma Location in Acute Intracerebral Hemorrhage. Neurology. 2026;107(9):e218514. doi:10.1212/WNL.0000000000018514
2. Qureshi AI, Palesch YY, Barsan WG, et al. Intensive Blood-Pressure Lowering in Patients with Acute Cerebral Hemorrhage. N Engl J Med. 2016;375(11):1033-1043.
3. Anderson CS, Heeley E, Huang Y, et al. Rapid Blood-Pressure Lowering in Patients with Acute Intracerebral Hemorrhage. N Engl J Med. 2013;368(25):2355-2365.
4. Hemphill JC 3rd, Greenberg SM, Anderson CS, et al. Guidelines for the Management of Spontaneous Intracerebral Hemorrhage: A Guideline for Healthcare Professionals From the American Heart Association/American Stroke Association. Stroke. 2015;46(7):2032-2060.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.