Cilostazol Therapy in Intracerebral Hemorrhage: Enhancing Dural Lymphatic Function for Neuroprotection
Highlights
- Oral cilostazol enhances dural lymphatic growth and function in experimental intracerebral hemorrhage (ICH).
- Cilostazol treatment accelerates hematoma resolution and reduces neuronal injury without increasing bleeding risk.
- Dural lymphatic remodeling underpins improved long-term neurological recovery in ICH models.
- Findings provide a mechanistic rationale for ongoing clinical trials assessing cilostazol in ICH patients.
Background
Intracerebral hemorrhage (ICH) remains a devastating subtype of stroke characterized by high morbidity and mortality. Current therapeutic options are limited, with no FDA-approved pharmacological agents shown to improve outcomes substantially after ICH. The burden of neuronal injury and secondary brain damage following hematoma formation necessitates innovative therapeutic approaches that target hematoma clearance and neurorepair mechanisms.
Recent advances have uncovered the meningeal lymphatic system, particularly the dural lymphatics, as critical in brain homeostasis and clearance of intracranial waste products. Emerging evidence suggests that these lymphatics contribute to hematoma resolution after ICH, facilitating neurological recovery. However, therapeutic strategies to harness or augment this lymphatic function remain underexplored.
Cilostazol, a phosphodiesterase 3 inhibitor with antiplatelet and vasodilatory properties used in ischemic stroke and peripheral vascular disease, has demonstrated prolymphangiogenic effects in preclinical studies. Initial intraperitoneal administration of cilostazol promoted dural lymphatic growth and enhanced clearance of red blood cells in experimental ICH models. Nevertheless, concerns about the antiplatelet effect raising bleeding risk pose challenges for clinical translation in hemorrhagic stroke contexts.
Key Content
Chronological Development of Evidence on Cilostazol and Dural Lymphatics in ICH
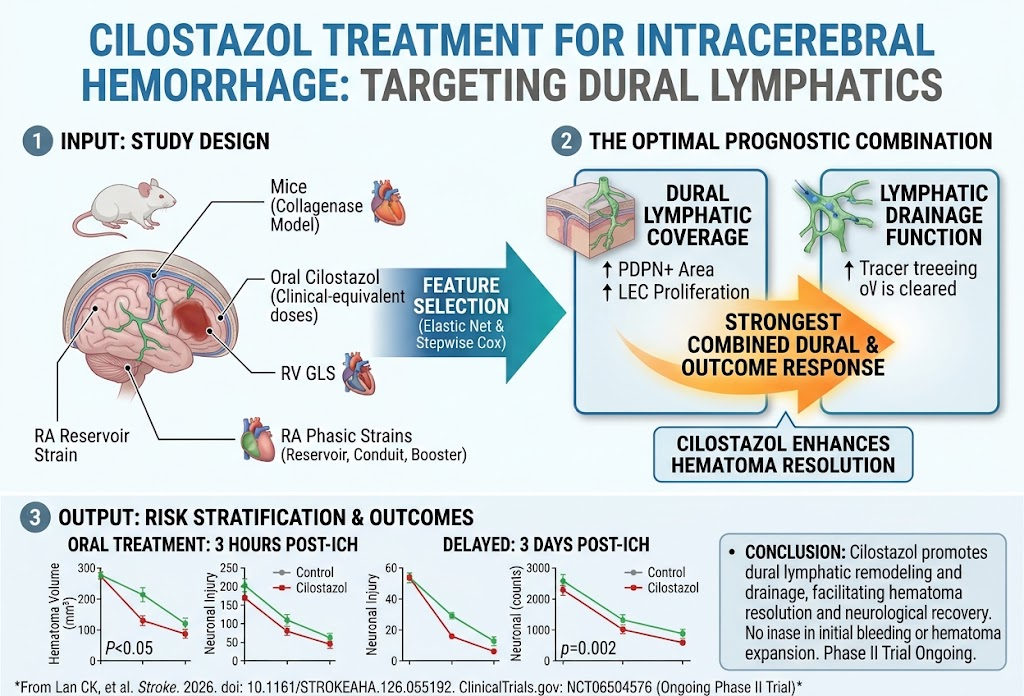
Early mechanistic studies identified the meningeal lymphatic system as an important mediator of brain fluid and waste clearance. Lan et al. (2026) provided pivotal data demonstrating oral cilostazol at clinical-equivalent doses in mice enhances dural lymphatic remodeling, improves lymphatic clearance function, and reduces hematoma volume following collagenase-induced ICH, a well-established model simulating microvascular rupture.
This study builds upon previous intraperitoneal dosing research by showing that oral administration—more clinically relevant—exerts similar prolymphangiogenic and neuroprotective effects without exacerbating hematoma expansion. Importantly, the timing of intervention was flexible; treatment initiated at either 3 hours or 3 days post-ICH improved outcomes, underscoring a therapeutic window addressing both acute and subacute phases.
Mechanistic Insights into Cilostazol-induced Dural Lymphatic Remodeling
Using flow cytometry and immunofluorescence, cilostazol increased CD31+PDPN+ lymphatic endothelial cell populations in ex vivo meninges, indicating endothelial proliferation and activation. Histological analyses revealed dural lymphatic hyperplasia and enhanced drainage of fluorescent tracer molecules in vivo, supporting functional augmentation of lymphatic clearance pathways.
These effects likely stem from cilostazol’s cyclic AMP (cAMP) elevation facilitating lymphangiogenesis and endothelial cell survival. Enhanced dural lymphatics accelerate hematoma resorption, limiting secondary neuronal injury such as synapse loss and preserving neurological function long-term.
Clinical-Equivalent Dosing and Safety Considerations
A major translational concern with cilostazol is its known antiplatelet effect, which could theoretically exacerbate bleeding in hemorrhagic stroke. However, the experimental results demonstrated that neither pretreatment nor delayed oral cilostazol administration increased hematoma volume or provoked rebleeding in mice. This safety profile supports further clinical evaluation.
Implications from Ongoing Clinical Trials
These preclinical findings underpin an ongoing phase II randomized clinical trial (NCT06504576) evaluating oral cilostazol’s safety and efficacy in ICH patients. Trial parameters reflect mechanistic insights from these studies, including dosing schedules and endpoints assessing hematoma resolution and functional recovery.
Expert Commentary
Lan et al.’s research provides a compelling mechanistic foundation linking cilostazol’s prolymphangiogenic properties to enhanced hematoma clearance and neurological recovery after ICH. The dural lymphatic system represents an emerging target with translational potential in hemorrhagic stroke.
While antiplatelet activity traditionally limits pharmacologic application post-ICH, the observed lack of hematoma exacerbation in the murine model is encouraging. Nonetheless, human physiology and comorbidities necessitate cautious interpretation. The flexible therapeutic window identified expands treatment feasibility beyond the hyperacute phase, aligning with real-world clinical scenarios.
This novel approach contrasts with classical neuroprotection or hemostasis strategies, instead harnessing endogenous clearance systems. Additionally, monitoring lymphatic remodeling via imaging biomarkers could advance patient stratification and therapeutic monitoring.
Limitations of current data include reliance on a single animal model and absence of detailed pharmacokinetic-pharmacodynamic correlation. Further studies to elucidate molecular pathways mediating lymphangiogenesis and investigate combinatory approaches with other neuroprotective agents are warranted.
Conclusion
Cilostazol enhances dural lymphatic remodeling and function, promoting hematoma resolution and improving neurological outcomes in experimental ICH without increasing bleeding risk. These findings open a new avenue for therapeutic intervention targeting meningeal lymphatics and support ongoing clinical trial efforts. Future research should focus on validating these results in diverse models, clarifying molecular mechanisms, and optimizing dosing protocols for maximal clinical benefit.
References
- Lan CK, Chen WR, Hsieh YC, Lin TY, Hsu SC, Jiang ZR, Chen SP, Jiang D, McCullough LD, Aronowski J, Tsai LK, Tsai HH, Chang CF. Cilostazol Treatment for Intracerebral Hemorrhage: Targeting Dural Lymphatics. Stroke. 2026 Sep 3; PMID: 42689324. https://pubmed.ncbi.nlm.nih.gov/42689324/
- Da Mesquita S, Louveau A, Vaccari A, et al. Functional aspects of meningeal lymphatics in ageing and Alzheimer’s disease. Nature. 2018;560(7717):185-191. doi:10.1038/s41586-018-0368-8
- Louveau A, Plog BA, Antila S, et al. Understanding the functions and relationships of the glymphatic system and meningeal lymphatics. J Clin Invest. 2017;127(9):3210-3219. doi:10.1172/JCI90603
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.