Differentiating Acute Imbalance Syndrome from Acute Vestibular Syndrome in Stroke-Related Vertigo: Clinical and Neuroanatomical Insights
Highlight
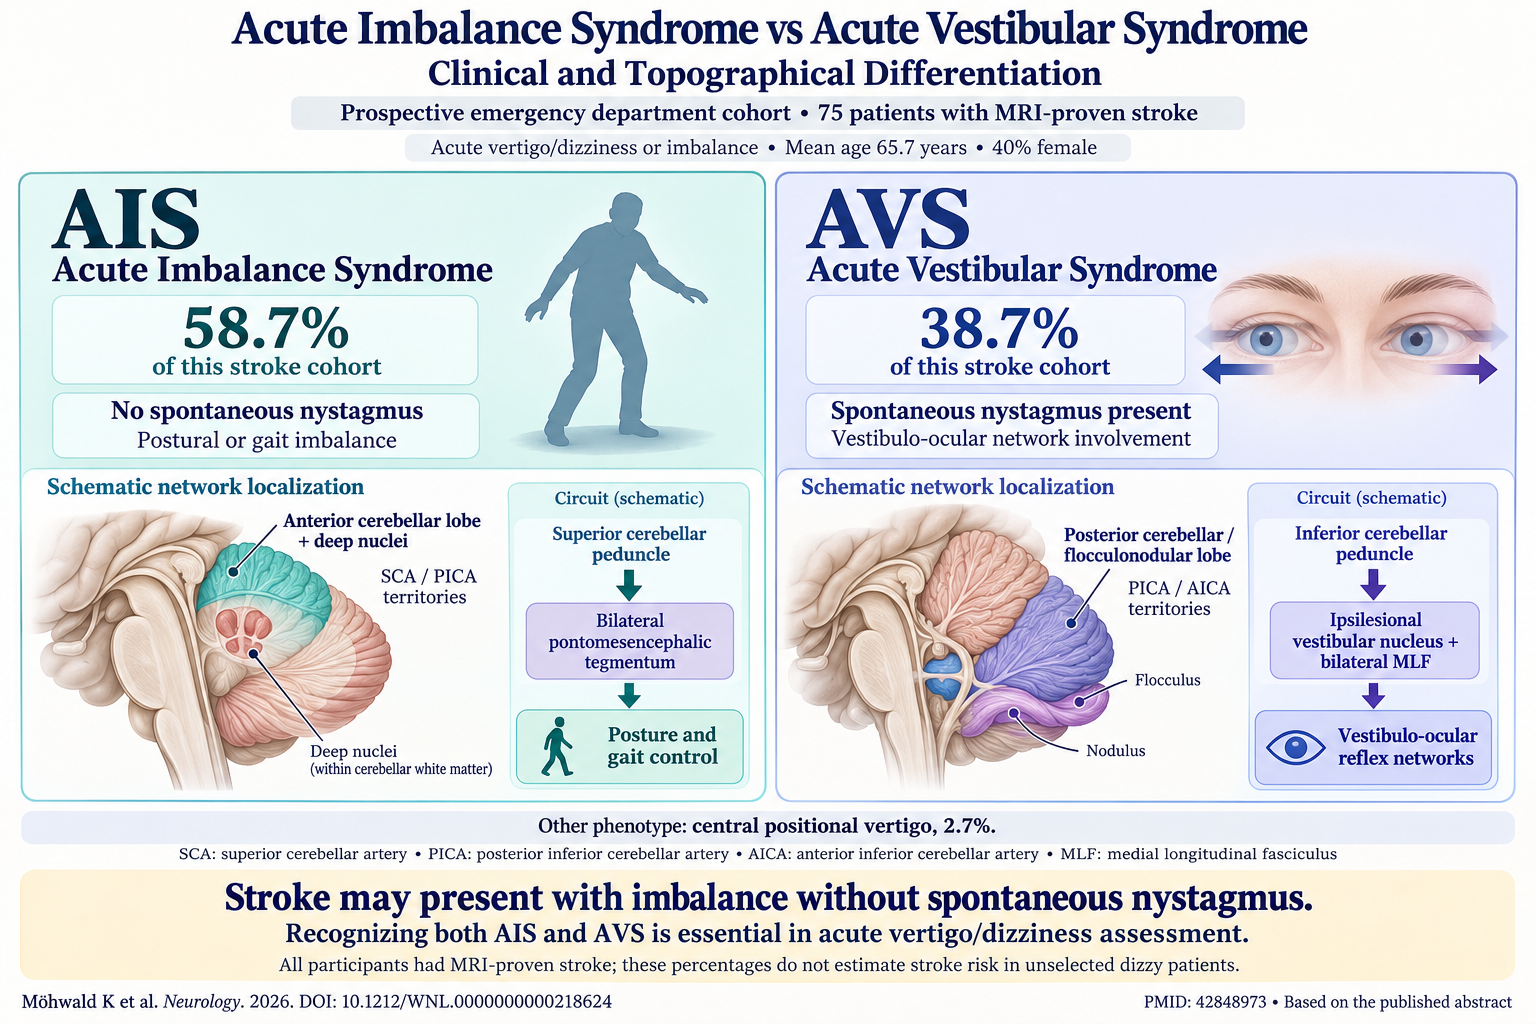
- Stroke can manifest as two distinct phenotypes in acute vertigo: Acute Vestibular Syndrome (AVS) with spontaneous nystagmus and Acute Imbalance Syndrome (AIS) without it.
- AIS accounts for over 58% of stroke-related vertigo/dizziness cases but remains under-recognized in emergency settings.
- Neuroanatomically, AIS lesions localize to the anterior cerebellar lobe and deep cerebellar nuclei affecting postural and gait control via cerebellar-pontomesencephalic networks.
- AVS lesions primarily involve the posterior cerebellar and flocculonodular lobes, with disruption of vestibulo-ocular reflex pathways.
Study Background
Acute vertigo and dizziness represent common but diagnostically challenging presentations in emergency medicine, with cerebrovascular stroke being a critical differential diagnosis due to its potentially devastating consequences. The acute vestibular syndrome (AVS) characterized by spontaneous nystagmus (SPN), gaze-evoked nystagmus, and positive head impulse test has served as the traditional clinical hallmark guiding suspicion toward stroke versus benign vestibular neuritis. However, recent evidence suggests that a significant subset of stroke patients present without spontaneous nystagmus but instead with predominant postural or gait imbalance, a phenotype now termed acute imbalance syndrome (AIS). This distinction has important implications as current stroke screening algorithms risk missing AIS cases. Understanding the clinical and topographical differences between AIS and AVS is essential for timely stroke diagnosis, targeted management, and appropriate prognostication.
Study Design
This prospective cohort study was conducted at the emergency department of LMU Hospital, enrolling patients with MRI-confirmed stroke presenting acutely with vertigo, dizziness, or imbalance. A total of 75 patients (mean age 65.7 ± 13.3 years, 40% female) were included. Clinical assessments comprised detailed vestibular, ocular motor, and postural evaluations, including quantification of spontaneous nystagmus intensity via video-oculography and postural instability through quantitative posturography. Patients were classified into AIS or AVS based on the presence or absence of SPN. Lesion localization was standardized in Montreal Neurological Institute space and further analyzed using structural disconnectome mapping to reveal broader network disturbances. Multivariate lesion-symptom mapping utilizing support-vector regression identified lesion correlates of SPN intensity (marker of AVS) and postural sway (marker of AIS).
Key Findings
Among the cohort, 58.7% of patients were diagnosed with AIS, 38.7% with AVS, and 2.7% had central positional vertigo. AIS lesions predominantly involved the anterior cerebellar lobe and deep cerebellar nuclei located in territories supplied by the superior cerebellar artery and posterior inferior cerebellar artery. These lesions were found to disrupt cerebellar-pontomesencephalic tracts via the superior cerebellar peduncle connecting with bilateral pontomesencephalic tegmentum, key regions implicated in posture and gait regulation.
Conversely, AVS lesions localized mainly in the posterior cerebellar lobe and flocculonodular region, territories supplied by the posterior inferior cerebellar artery and anterior inferior cerebellar artery. These lesions impacted ipsilesional vestibular nuclei and bilateral medial longitudinal fascicle pathways via the inferior cerebellar peduncle, central to the vestibulo-ocular reflex (VOR) circuitry. Importantly, SPN intensity positively correlated with lesions in cerebellar lobules VI-IX, which interface with vestibular nuclei and medial longitudinal fasciculus.
Postural sway, indicative of imbalance severity, was associated with a localized cluster within cerebellar Crus I, highlighting cerebellar involvement in fine motor and postural control.
These neuroanatomical dissociations corroborate the clinical differentiation in presentations — while AVS primarily manifests as spontaneous nystagmus and vertigo due to VOR network disruption, AIS presents with predominant imbalance and gait disturbance stemming from impaired cerebellar-postural control networks.
Expert Commentary
These findings underscore the necessity for heightened clinical vigilance for AIS in acute vertigo syndromes. Traditional bedside algorithms emphasize the head impulse test, nystagmus characterization, and skew deviation to identify AVS, potentially overlooking AIS patients who lack obvious nystagmus but harbor cerebellar strokes. Incorporating posturography or detailed postural assessments may improve AIS recognition. Furthermore, neuroimaging strategies should be tailored to focus on anterior cerebellar territories and associated brainstem connections when AIS is suspected.
While this study benefits from prospective design and advanced neuroimaging analytics including disconnectome mapping, limitations include the modest sample size and single-center setting, which may affect generalizability. Future larger multicenter studies could validate these topographical signatures and link them with long-term functional outcomes.
Conclusion
Acute Imbalance Syndrome is a frequently under-recognized stroke presentation in patients with acute vertigo/dizziness. Delineating AIS from the classical AVS phenotype based on clinical signs and specific lesion topography can enhance stroke detection and management in the emergency setting. Awareness of distinct cerebellar and brainstem network involvement guiding these phenotypes underscores the importance of comprehensive clinical assessment beyond spontaneous nystagmus. Integration of these insights into clinical practice may reduce stroke misdiagnosis and improve patient outcomes.
Funding and Clinical Trial Registrations
The study was registered prospectively under DRKS00008992 and U1111-1172-8719. Specific funding sources were not detailed in the publication.
References
1. Möhwald K, Hadzhikolev H, Eberle L, et al. Acute Imbalance Syndrome vs Acute Vestibular Syndrome: Clinical and Topographical Differentiation. Neurology. 2026 Oct 8;107(9):e218624. PMID: 42848973.
2. Kerber KA, Brown DL, Lisabeth LD, et al. Stroke risk stratification in ED patients with dizziness and vertigo: A population-based study. Neurology. 2013;81(12):1078-1086.
3. Brandt T, Dieterich M, Strupp M. Vertigo and Dizziness: Common Clinical Problems. Oxford University Press; 2014.
4. Kattah JC, Talkad AV, Wang DZ, et al. HINTS to diagnose stroke in the acute vestibular syndrome: Three-step bedside oculomotor examination more sensitive than early MRI diffusion-weighted imaging. Stroke. 2009;40(11):3504-3510.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.