Hospital Stroke Center Designation Influences Reported Stroke Rates After TAVR: Implications for Quality Assessment
Highlight
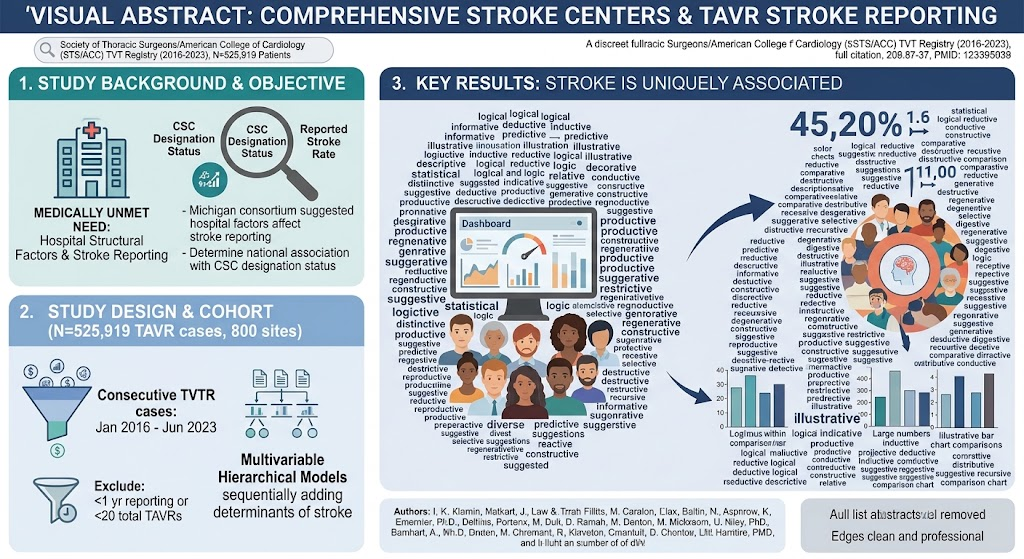
– Comprehensive Stroke Center (CSC) designation is independently associated with higher reported in-hospital and disabling stroke rates after transcatheter aortic valve replacement (TAVR).
– Participation in TAVR clinical trials and operator procedural volume also significantly influence stroke reporting.
– Correcting stroke rates for CSC status modestly improves hospital performance rankings in the Transcatheter Valve Therapy Registry public reporting.
– Findings suggest potential ascertainment bias impacting stroke reporting and quality metrics, warranting further evaluation.
Study Background
Transcatheter aortic valve replacement (TAVR) has become a cornerstone treatment for patients with aortic valve stenosis across a broad risk spectrum. Stroke remains a feared adverse event associated with TAVR, contributing to morbidity, mortality, and healthcare costs. Accurate reporting and benchmarking of stroke outcomes after TAVR are crucial for informing quality improvement, public reporting, and hospital accreditation.
The Michigan Structural Heart Consortium previously observed that hospitals with Comprehensive Stroke Center (CSC) designation reported higher stroke rates post-TAVR, suggesting hospital structural factors may influence stroke detection and reporting. However, whether this association holds at a national level and its impact on hospital performance assessment metrics have not been well studied.
Study Design
This retrospective observational study included consecutive TAVR procedures recorded in the Society of Thoracic Surgeons/American College of Cardiology Transcatheter Valve Therapy Registry (TVTR) from January 2016 through June 2023. Hospitals with fewer than 20 total TAVR procedures or reporting to the registry for less than one year were excluded to ensure data reliability.
The primary outcome was in-hospital stroke rate, with secondary outcomes including disabling stroke and 30-day stroke incidence. To explore the specificity of CSC status association with stroke reporting, falsification endpoints like major bleeding, death, and acute renal failure were examined. Multivariable hierarchical models adjusted initially for patient-level covariates, sequentially adding hospital-level variables including CSC designation, TAVR trial participation, and operator volume. The impact of CSC status on hospital composite performance scores from the validated TVTR 30-day composite model was analyzed to assess implications for public reporting.
Key Findings
The study included 525,919 TAVR cases across 800 hospitals, with an overall 30-day stroke rate of 2.1% (10,963 strokes). In-hospital strokes accounted for 1.6% (8,284) of cases, and disabling strokes constituted 0.9% (4,733). The remaining strokes occurred after discharge but within 30 days.
Multivariable analysis demonstrated that CSC hospital status was an independent predictor of both in-hospital stroke and disabling stroke, with statistical significance (P=0.033 for both). Participation in TAVR clinical trials also independently predicted these stroke outcomes (P=0.012 for in-hospital stroke, P=0.007 for disabling stroke). Notably, CSC designation was not associated with falsification endpoints such as major bleeding or acute renal failure, indicating a specific relationship to stroke detection and reporting rather than overall complication reporting.
Additionally, participation in TAVR trials and higher operator volume were independent predictors of 30-day stroke events (P=0.039 and P=0.041, respectively). These findings suggest hospitals more engaged in research and with experienced operators may more comprehensively detect or report strokes.
Accounting for CSC status in the TVTR 30-day composite hospital performance model resulted in improvement in performance measures for 8 of 153 CSC-designated hospitals, representing a modest but clinically relevant impact on publicly reported quality rankings.
Expert Commentary
This large national registry analysis corroborates earlier regional findings that hospital stroke center accreditation correlates with higher reported stroke rates following TAVR. The specificity of this association to stroke—without similar effects on other adverse events—supports the hypothesis of ascertainment bias rather than true differences in stroke incidence. CSC hospitals may have enhanced neurological evaluation capabilities, dedicated stroke teams, and stricter neurological monitoring protocols, leading to improved detection and reporting of cerebrovascular events.
Participation in clinical trials likely reflects centers with rigorous follow-up and reporting standards. Operator volume correlating with stroke rates may also reflect more detailed surveillance in high-volume centers.
The implications for hospital performance assessment and public reporting are significant. Current quality metrics may inadvertently penalize centers with advanced stroke detection capabilities, discouraging transparent adverse event reporting. Adjusting composite outcomes by CSC status could provide a fairer comparison across institutions.
Limitations include the observational study design, potential residual confounding, and lack of granular data on stroke severity or imaging protocols. Future prospective studies incorporating standardized neuroassessment protocols could validate these findings. Additionally, evaluating how stroke ascertainment affects clinical decision-making and patient outcomes is warranted.
Conclusion
The study highlights that Comprehensive Stroke Center designation and clinical trial participation are uniquely associated with higher reported stroke rates after TAVR, likely reflecting ascertainment bias rather than true increases in adverse events. Adjusting hospital performance assessments for these factors influences public reporting outcomes and underscores the need to refine quality metrics accounting for hospital structural characteristics. Further research should focus on standardizing stroke detection and reporting to ensure accurate benchmarking and quality improvement in structural heart interventions.
Funding and ClinicalTrials.gov
The original study does not explicitly mention funding sources or clinical trial registration numbers. The data derive from the Society of Thoracic Surgeons/American College of Cardiology Transcatheter Valve Therapy Registry, a national clinical registry.
References
1. Deeb GM, Grossman PM, Manandbar P, et al. The Association Between Hospital Comprehensive Stroke Center Designation Status and Stroke Rate Reporting in the Society of Thoracic Surgeons/American College of Cardiology Transcatheter Valve Therapy Registry After Transcatheter Aortic Valve Replacement: Implications for Hospital Performance Assessment. Circulation. 2026 Sep 29; PMID: 42808167.
2. Mack MJ, Leon MB, Smith CR, et al. 5-Year Outcomes of Transcatheter Aortic Valve Replacement or Surgical Aortic Valve Replacement for High Surgical Risk Patients With Severe Aortic Stenosis (PARTNER 1). J Am Coll Cardiol. 2015;66(25):2813-2822.
3. Khatri P, Dhamoon MS, Saver JL. Stroke center certification: is the pursuit continuous improvement or public relations? Stroke. 2010;41(10):2243-2245.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.