Reevaluating Colorectal Cancer Surveillance in Inflammatory Bowel Disease: The Role of Family History Beyond Early-Onset Cases
Highlight
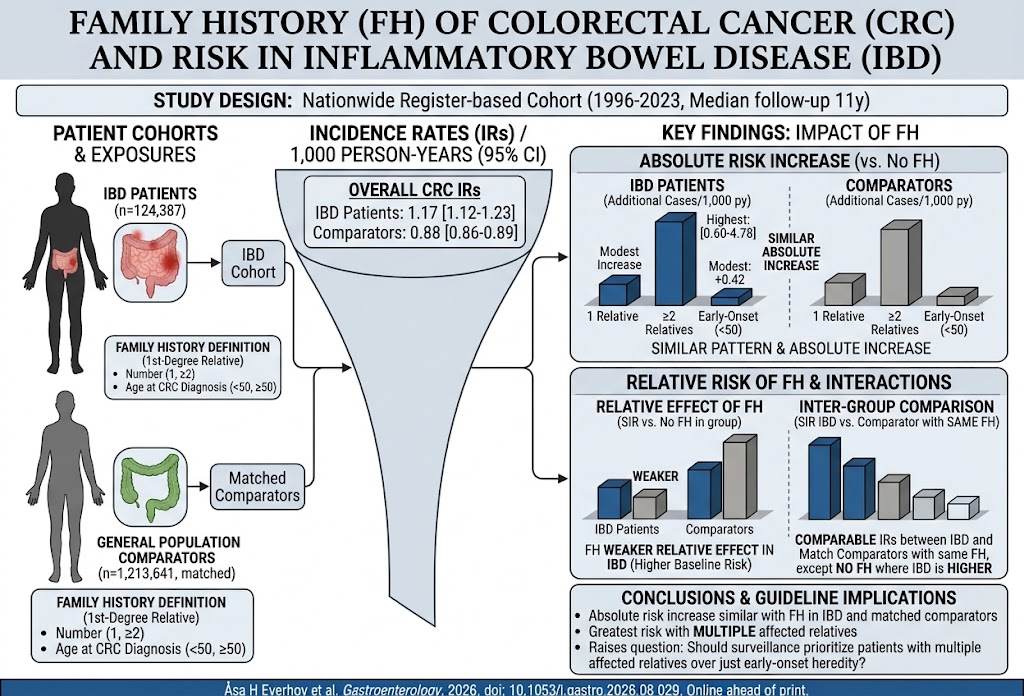
- Family history of colorectal cancer (CRC) increases absolute CRC incidence similarly in patients with inflammatory bowel disease (IBD) and general population comparators.
- The highest CRC risk in IBD is identified in individuals with two or more first-degree relatives affected by CRC, rather than those with early-onset family history.
- The relative effect of family history is attenuated in IBD due to the already elevated baseline CRC risk associated with chronic inflammation.
- These findings raise important questions about current surveillance prioritization focusing on early-onset family history over multiple affected relatives.
Study Background
Colorectal cancer (CRC) is a significant morbidity and mortality concern worldwide. Patients with inflammatory bowel disease (IBD), including ulcerative colitis and Crohn’s disease involving the colon, have a recognized elevated risk of CRC compared to the general population because of chronic intestinal inflammation driving carcinogenesis. Surveillance colonoscopy programs have been implemented to detect premalignant changes early and reduce CRC-related mortality in this high-risk group.
Family history of CRC is an established risk factor that independently elevates CRC risk in the general population, especially when multiple first-degree relatives are affected or when relatives were diagnosed at an early age (typically before 50 years). However, how family history modulates CRC risk specifically among patients with IBD is less thoroughly studied, and current guidelines emphasize special attention to patients with a family history of early-onset CRC. Understanding this interplay is crucial to tailoring surveillance strategies that effectively allocate resources and optimize patient outcomes.
Study Design
This investigation was a large, nationwide, register-based cohort study conducted from 1996 to 2023. The study included 124,387 patients diagnosed with IBD and 1,213,641 matched comparators from the general population, matched on key variables including age, sex, parish (geographical location), and calendar year.
The primary exposure was family history of CRC, categorized by the number of first-degree relatives (parents, siblings, children) affected and their age at diagnosis (<50 years versus ≥50 years). The primary outcome was the incidence rate (IR) of CRC during follow-up, measured per 1,000 person-years. Median follow-up duration was 11 years. Incidence rates and incidence rate differences were estimated, and interaction effects between family history and IBD status were analyzed.
Key Findings
During follow-up, there were 1,882 CRC events among patients with IBD (IR 1.17 per 1,000 person-years; 95% CI: 1.12–1.23) and 14,177 CRC events among matched comparators (IR 0.88 per 1,000 person-years; 95% CI: 0.86–0.89). This confirms the well-documented increased baseline risk of CRC in IBD.
When stratified by family history, the absolute increase in CRC incidence varied notably:
– In IBD patients with two or more affected relatives, the additional CRC incidence was 2.69 cases per 1,000 person-years (95% CI: 0.60–4.78) compared to those without a family history.
– In contrast, IBD patients with a family history of early-onset CRC (<50 years) had a more modest additional risk of 0.42 cases per 1,000 person-years (95% CI: -0.47 to 1.31), indicating a statistically weaker or nonsignificant increase.
For individuals without a family history, CRC incidence was higher in IBD patients than in their general population comparators, reflecting baseline risk elevation due to IBD.
Interestingly, relative risks associated with family history were generally lower in IBD patients compared to comparators since baseline CRC risk is already elevated in IBD, which reduces the relative effect magnitude of additional familial risk.
Overall, CRC incidence rates were similar when comparing IBD patients and matched controls who shared the same family history profile, except for those without family history where IBD conferred higher risk.
Expert Commentary
This comprehensive, population-based study leverages robust registry data to clarify the nuanced interplay between family history and IBD-related CRC risk. Importantly, it challenges the current guideline emphasis that prioritizes early-onset family history as the main familial CRC risk marker warranting intensified surveillance. Instead, the data point to a stronger impact from having multiple affected first-degree relatives irrespective of age at diagnosis.
Mechanistically, IBD-related CRC risk is largely driven by chronic mucosal inflammation, which may be relatively independent of hereditary genetic factors associated with early-onset CRC predisposition. However, the additive risk from multiple familial CRC cases could reflect greater underlying genetic susceptibility or shared environmental factors that amplify carcinogenic risk beyond IBD inflammation alone.
Limitations include the observational design, which cannot fully account for unmeasured confounders such as variation in surveillance practices, medication use, or lifestyle factors influencing CRC risk. Moreover, CRC subtypes and molecular characteristics were unavailable, limiting deeper insight into pathogenesis differences.
Nonetheless, the study’s strength lies in its large sample size, matched controls, and long-term follow-up, enabling precise incidence rate estimation.
Conclusion
This nationwide cohort study elucidates that family history of CRC increases the absolute risk of CRC in IBD patients similarly to the general population, with the most significant risk rise among those with multiple affected first-degree relatives. The relative effect appears attenuated in IBD due to already elevated cancer risk.
These findings suggest a need to reconsider current surveillance guidelines that prioritize early-onset family history. Instead, surveillance efforts might better focus on IBD patients with multiple affected first-degree relatives to improve risk stratification and optimize early CRC detection.
Future research should explore molecular and genetic markers to refine personalized risk prediction and surveillance recommendations further. Meanwhile, clinicians should carefully assess familial CRC burden beyond just early-onset cases during routine IBD care to guide timely and appropriate colonoscopy surveillance.
Funding and ClinicalTrials.gov
The study was supported by institutional grants and public research funding as disclosed by the original authors. No clinical trial registration number was reported since this was an observational registry study.
References
1. Everhov ÅH, Kristjánsson K, Ludvigsson JF, et al. Impact of Family History on Colorectal Cancer Risk in Inflammatory Bowel Disease and in Matched General Population Comparators. Gastroenterology. 2026 Sep 3. PMID: 42692118.
2. Jess T, Rungoe C, Peyrin-Biroulet L. Risk of colorectal cancer in patients with ulcerative colitis: a meta-analysis of population-based cohort studies. Clinical Gastroenterology and Hepatology. 2012;10(6):639-645.
3. Stoffel EM, Mangu PB, Gruber SB, et al. Hereditary colorectal cancer syndromes: American Society of Clinical Oncology Clinical Practice Guideline endorsement of the familial risk-colorectal cancer: European Society for Medical Oncology Clinical Practice Guidelines. Journal of Clinical Oncology. 2015;33(2):209-217.
4. Ullman TA, Croog VJ, Harpaz N, et al. Effects of immunosuppression (azathioprine and 6-mercaptopurine) on dysplasia and colorectal cancer in ulcerative colitis. Clinical Gastroenterology and Hepatology. 2009;7(10):1121-1128.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.