Ischaemic Stroke Risk in Atrial Flutter Versus Atrial Fibrillation: Insights from a Finnish Nationwide Registry Study
Highlight
- Patients with atrial flutter (AFL) exhibit a significantly lower incidence of ischaemic stroke compared to those with atrial fibrillation (AF).
- Combined presence of AF and AFL confers a slightly higher stroke risk than AF alone.
- The study leverages a large Finnish nationwide cohort with robust ECG documentation and long-term follow-up, enhancing the validity of findings.
- Results remained consistent across anticoagulation status and CHA2DS2-VA risk categories, underlining intrinsic differences in stroke risk between arrhythmias.
Study Background
Atrial fibrillation (AF) and atrial flutter (AFL) are common supraventricular arrhythmias associated with elevated risks of thromboembolic events, most notably ischaemic stroke (IS). Although AF has been extensively studied and linked to significant stroke risk, the thromboembolic risk associated with AFL has been less clear due to limited large-scale, well-characterized datasets. Prior smaller studies suggested that AFL may confer a lower stroke risk than AF, but these often suffered from limited electrocardiographic (ECG) verification and insufficient adjustment for confounders.
Given the clinical implications for anticoagulation management and stroke prevention, understanding the differential stroke risk in AFL versus AF is crucial. The present study, stemming from the Finnish AntiCoagulation in Atrial Fibrillation (FinACAF) study, addresses this gap by providing a comprehensive analysis of stroke incidence among patients with ECG-confirmed arrhythmia diagnoses within a nationwide cohort.
Study Design
This observational cohort study utilized registry linkage encompassing all patients in Finland diagnosed with AF and/or AFL from 2007 to 2018, integrating a comprehensive collection of digitally documented ECGs totaling over half a million records.
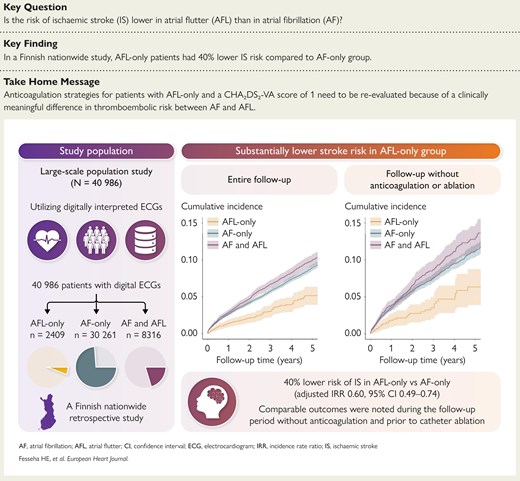
Patients were classified into three mutually exclusive groups based on ECG findings: AF-only, AFL-only, and combined AF & AFL. The study population included 40,986 patients with newly diagnosed arrhythmias; 30,261 had AF-only, 2,409 had AFL-only, and 8,316 had both AF and AFL detected.
Primary outcome measured was incidence of ischaemic stroke, with incidence rate ratios (IRRs) calculated adjusting for demographics, comorbidities, and anticoagulation status. Follow-up averaged 1.2 years with 77.6% of patients initiating anticoagulant therapy during observation. Additional analyses assessed stroke risk during anticoagulation-free periods and prior to catheter ablation. Stroke risk stratification utilized CHA2DS2-VA (excluding sex category) scores.
Key Findings
Over follow-up, 3,165 (7.7%) patients experienced ischaemic stroke. Crude incidence rates per 100 patient-years for IS were:
- AF-only: 1.9 (95% CI 1.8–1.9)
- AFL-only: 1.1 (95% CI 0.9–1.3)
- AF & AFL: 2.1 (95% CI 1.9–2.2)
Adjusted analyses revealed that the AFL-only group had a significantly lower IS risk compared to the AF-only group (adjusted IRR 0.60; 95% CI 0.49–0.74), indicating a 40% relative risk reduction. Meanwhile, patients with combined AF & AFL had a modestly elevated stroke risk relative to AF-only (adjusted IRR 1.11; 95% CI 1.02–1.20).
These risk differentials persisted even when analyses were restricted to periods without anticoagulation therapy and before catheter ablation, minimizing confounding by therapy or intervention. Furthermore, the findings remained consistent across different levels of CHA2DS2-VA score, supporting the notion that AFL intrinsically carries lower thromboembolic risk than AF.
Expert Commentary
The study provides compelling evidence for differentiated stroke risk profiles between AFL and AF, likely reflecting distinct electrophysiological and hemodynamic characteristics. Atrial flutter typically manifests as a more organized atrial activation with less stasis, possibly reducing thrombus formation compared to the chaotic atrial contractions in AF.
Clinical guidelines often extrapolate stroke risk estimates and anticoagulation recommendations from AF data to AFL; however, these findings challenge that uniform approach. Lower stroke risk in AFL patients may justify more individualized consideration regarding anticoagulation initiation, particularly in low- to intermediate-risk patients.
Nevertheless, the elevated stroke risk observed in patients exhibiting both AF and AFL underscores the complexity of arrhythmia phenotypes and necessitates vigilant risk assessment. One limitation inherent to observational registry studies includes residual confounding and potential misclassification despite rigorous ECG verification. Moreover, the relatively short mean follow-up of 1.2 years warrants confirmation of long-term risk patterns.
Future prospective studies are needed to explore underlying mechanisms and inform tailored stroke prevention strategies.
Conclusion
This large, nationwide Finnish study robustly demonstrates that patients with atrial flutter alone have a significantly lower risk of ischaemic stroke compared to those with atrial fibrillation, with combined arrhythmia patients facing the highest risk. These findings emphasize clinically meaningful differences in thromboembolic risk and advocate for differentiated therapeutic considerations in AF and AFL populations.
Integrated clinical assessment and ECG documentation remain critical to guiding anticoagulation decisions, optimizing stroke prevention, and improving patient outcomes across these common atrial arrhythmias.
Funding and Trial Registration
Details of funding sources or clinical trial registration were not specified in the source abstract.
References
1. Eyob Fesseha H, Aro AL, Teppo K, et al. Ischaemic stroke in atrial flutter vs fibrillation: a Finnish nationwide study. European Heart Journal. 2026; PMID: 42690735.
2. January CT, Wann LS, Calkins H, et al. 2019 AHA/ACC/HRS Focused Update on Atrial Fibrillation Management. Circulation. 2019;140(2):e125-e151.
3. Kirchhof P, Benussi S, Kotecha D, et al. 2016 ESC Guidelines for the management of atrial fibrillation developed in collaboration with EACTS. European Heart Journal. 2016;37(38):2893-2962.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.