How the 2026 Chinese Consensus Changes Use of Immune Checkpoint Inhibitors in Locally Advanced Rectal Cancer
Introduction and Context
Over the past five years the management paradigm for a biologically defined subset of colorectal cancers—those with deficient mismatch repair (dMMR) or high microsatellite instability (MSI‑H)—has shifted dramatically. Immune checkpoint inhibitors (ICIs) that release anti‑tumour T cells from inhibitory signals now produce deep responses in metastatic MSI‑H colorectal cancer and, strikingly, in some patients with locally advanced rectal cancer (LARC) treated before surgery. The most attention-grabbing data came from early neoadjuvant PD‑1 blockade in dMMR LARC producing high rates of clinical complete response (cCR), raising the possibility of non‑operative management for selected patients.
In response to this rapid progress and a growing body of trial evidence, the Chinese Society of Colorectal Surgery (CSCS) issued a formal expert consensus guidance published in Gut (Yang et al., 2026). The document sets unified standards for diagnosis, perioperative use of ICIs, organ-preserving strategies, safety and follow‑up in LARC. It aims to help surgeons, medical and radiation oncologists, pathologists, radiologists, nursing staff and health policymakers integrate ICIs responsibly into routine practice. This article summarizes the core recommendations and practical implications of that consensus, highlights key evidence driving the changes, and flags major controversies and research needs.
New Guideline Highlights
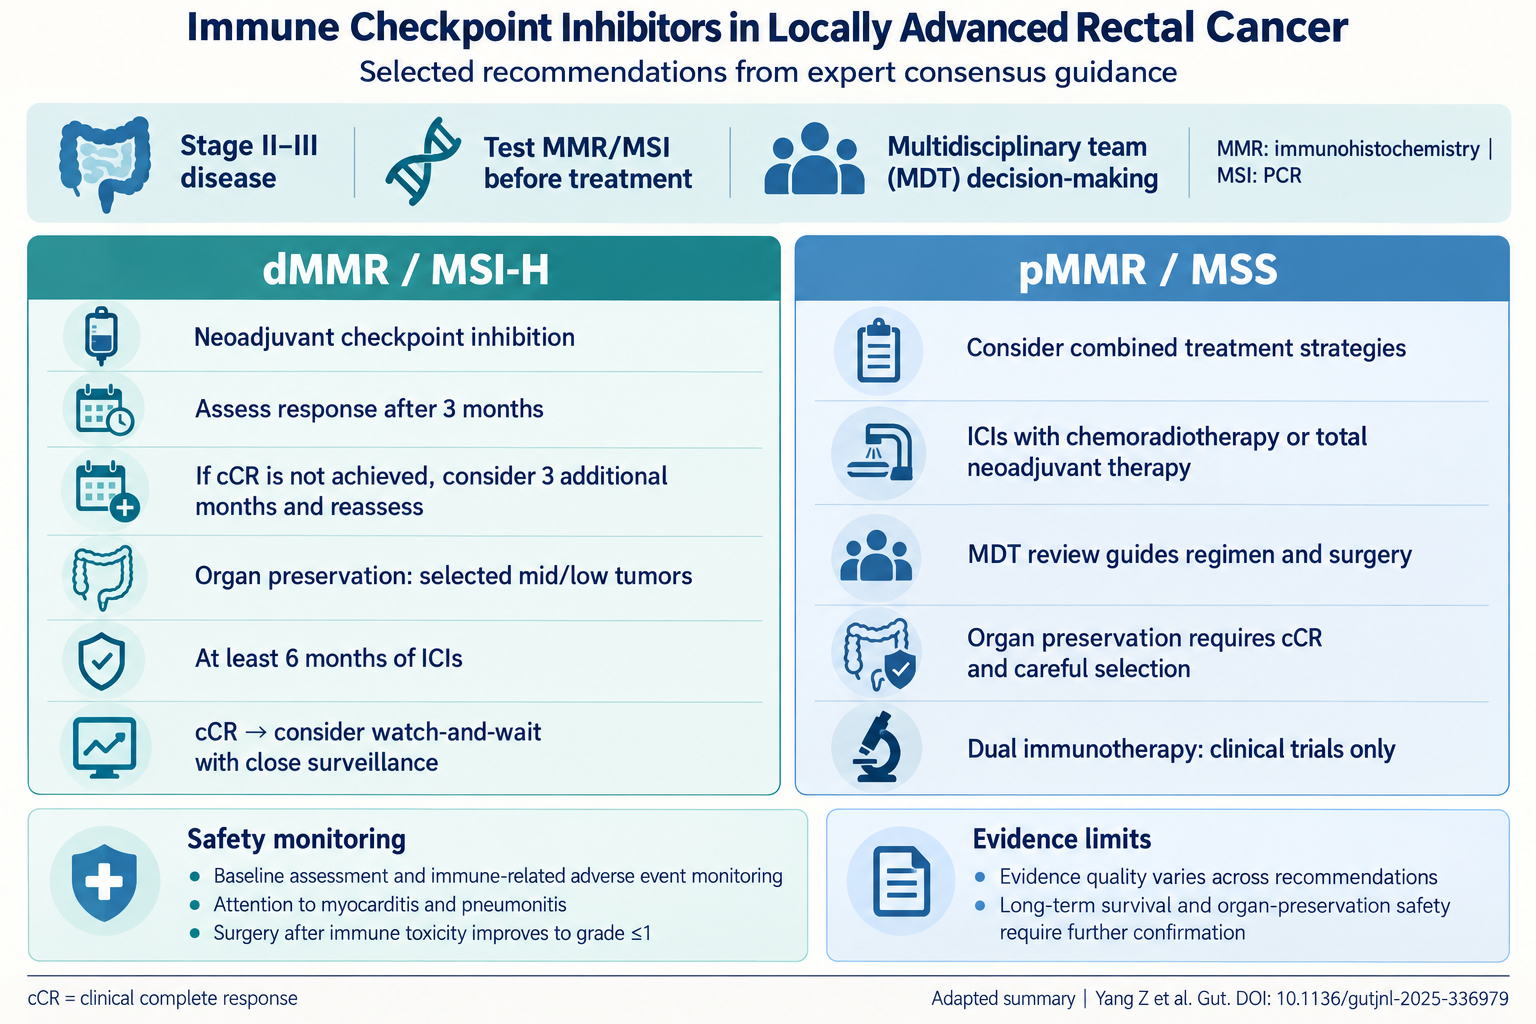
– Primary indication: For patients with LARC whose tumours show dMMR/MSI‑H, the consensus endorses neoadjuvant PD‑1 inhibitor–based therapy as a standard, especially when organ preservation is a priority.
– Diagnostic rigor: The guidance mandates standardized testing for mismatch repair status (IHC and/or PCR/NGS confirmation where indicated) and emphasizes multidisciplinary team (MDT) review for all ICI treatment decisions.
– Treatment pathways: Strong support is given for organ‑sparing strategies (local excision or watch‑and‑wait) after robust clinical response to neoadjuvant immunotherapy in appropriately staged patients, with detailed criteria for response assessment and surveillance.
– Perioperative and safety management: The consensus provides practical recommendations for timing of ICI relative to surgery, monitoring and managing immune‑related adverse events (irAEs), and special considerations for combining ICIs with chemoradiation or other agents.
– Evidence‑tiered recommendations: The document grades recommendations by strength and evidence level, and highlights where evidence remains limited (for example, use of ICIs in pMMR LARC outside of trials).
Key takeaways for clinicians: test all LARC patients for MMR/MSI; refer dMMR patients to MDTs early; consider neoadjuvant PD‑1 blockade for organ preservation; restrict ICI use in pMMR disease to clinical trials or combination regimens supported by data.
Updated Recommendations and Key Changes
Why an update was needed
– Breakthrough single‑arm and early-phase trials (notably PD‑1 monotherapy in dMMR LARC) reported unprecedented complete clinical and pathological responses that challenge the traditional surgery‑first paradigm.
– Competing approaches (neoadjuvant chemoradiotherapy, short‑course radiotherapy with consolidation chemotherapy, total neoadjuvant therapy) remain appropriate for pMMR tumours, but the rise of immunotherapy required clear guidance to avoid inconsistent off‑label use and to prioritize patient safety.
Major updates vs prior practice
– Universal MMR/MSI testing: The consensus elevates testing to a mandatory, early step for all LARC patients to identify possible candidates for neoadjuvant immunotherapy—this is now a workflow requirement rather than optional.
– Neoadjuvant ICI as a standard option for dMMR LARC: Whereas prior guidelines recommended trial enrollment or case‑by‑case use, the 2026 guidance recognizes PD‑1 inhibitor–based neoadjuvant therapy as a recommended pathway for many dMMR LARC patients.
– Clear organ‑preservation algorithms: The group formalizes criteria for selecting patients for non‑operative management after ICI response, standardizes timing and modalities for response assessment (endoscopy, MRI, PET where available), and prescribes surveillance frequency for watch‑and‑wait.
– Perioperative timing and safety pathways: New practical guidance describes optimal intervals between last ICI dose and elective surgery, preoperative assessment for irAEs, and perioperative steroid/immune‑modulating management to reduce surgical risk.
Evidence driving updates
– Single‑center neoadjuvant PD‑1 studies (e.g., dostarlimab series) have shown remarkably high cCR/pCR rates in dMMR LARC, generating the impetus for broader adoption under structured guidance (Cercek et al., NEJM 2022).
– Larger metastatic disease trials—pembrolizumab (KEYNOTE‑177) and nivolumab ± ipilimumab in MSI‑H metastatic colorectal cancer—demonstrate durable benefit of ICIs in MSI‑H CRC and support translation to earlier disease stages.
Topic‑by‑Topic Recommendations
Diagnostics and staging
– Mandatory MMR/MSI testing: All newly diagnosed LARC patients should undergo MMR IHC (MLH1, MSH2, MSH6, PMS2) as first line; abnormal/loss patterns should be confirmed or complemented by PCR/NGS MSI testing, and MLH1 loss with absent BRAF V600E and/or promoter methylation should prompt germline evaluation for Lynch syndrome.
– Imaging and baseline assessment: High‑resolution pelvic MRI, contrast CT of chest/abdomen/pelvis, and endoscopic assessment are required for baseline staging before neoadjuvant therapy. PET‑CT is optional, useful for ambiguous findings.
Recommendation strength (summary table)
– MMR/MSI testing: Strong recommendation, high-quality evidence (Consensus strength: Strong).
– MDT review for ICI candidacy: Strong recommendation, expert consensus.
Who should receive neoadjuvant ICI?
– Recommended candidates: Patients with resectable, locally advanced rectal adenocarcinoma that is dMMR/MSI‑H and who are motivated to pursue organ‑preservation strategies are prime candidates for neoadjuvant PD‑1 inhibitor therapy.
– Not routinely recommended: Patients with pMMR (MSI‑stable) disease should not receive single‑agent PD‑1 blockade off‑trial. Consideration of ICI within clinical trials or in combination with radiation/chemotherapy is appropriate for pMMR disease in selected protocols.
Treatment regimens and duration (practical framework)
– Regimen choice: The consensus supports anti‑PD‑1 monotherapy (e.g., pembrolizumab, nivolumab, dostarlimab) as an acceptable neoadjuvant option for dMMR LARC; combinations (e.g., anti‑PD1 + CTLA‑4) may be considered in trial contexts or when rapid response is needed.
– Treatment duration and monitoring: The guidance recommends regular clinical evaluation and imaging during neoadjuvant ICI, with response assessment typically every 6–12 weeks. Decisions to proceed to local excision, radical surgery, or watch‑and‑wait are made by MDTs based on endoscopy, MRI, biopsy when indicated, and clinical status.
– Organ‑preservation strategy: For patients achieving complete clinical response after ICI, the consensus endorses watch‑and‑wait with intensive surveillance or local excision (transanal approaches) when appropriate. Pathologic confirmation is preferred if local excision is done.
Postoperative and adjuvant therapy
– Pathology‑directed adjuvant therapy: The need for adjuvant therapy after neoadjuvant ICI depends on pathologic stage. For ypT0N0 (pathologic complete response) after neoadjuvant PD‑1 therapy, the consensus suggests individualized discussion; routine adjuvant chemotherapy is not mandatory and may be omitted in many patients, especially if organ preservation is achieved.
– Residual disease: Patients with residual tumour or nodal disease should be considered for standard adjuvant therapy per stage and may require combined modality treatment.
Follow‑up and surveillance
– Watch‑and‑wait surveillance protocol: Intensive first‑2‑year follow‑up (digital rectal exam and endoscopy every 3 months; pelvic MRI every 3–4 months) tapering thereafter. Prompt salvage surgery is recommended on signs of regrowth.
– Long‑term monitoring for late irAEs and functional outcomes: The consensus stresses monitoring for delayed immune toxicities and assessing bowel, urinary and sexual function as part of survivorship care.
Special populations and practical considerations
– Elderly and frail patients: Age alone should not exclude patients from ICI therapy, but frailty, comorbidity and life expectancy must be considered in MDT decisions.
– Lynch syndrome carriers: The consensus underscores the importance of germline testing and family counselling; ICI benefits in dMMR tumours apply, but surveillance and genetic considerations remain paramount.
– Perioperative timing and surgical safety: The guidance provides practical windows to minimize surgical complications—recommendations advise preoperative evaluation for irAEs, and suggest appropriate intervals between last ICI dose and elective surgery, tailored to the procedure, but stress individualized decision‑making by MDTs.
Expert Commentary and Insights
Committee perspectives
– The expert panel emphasized two themes: (1) the need to translate striking trial results into safe, standardized clinical practice, and (2) caution about overextending ICI use beyond the evidence base (for pMMR disease) without trial support.
– The document is deliberately pragmatic: it allows organ preservation driven by patient preference and response, but prescribes rigorous surveillance and clear criteria for salvage surgery to avoid compromising cure rates.
Key controversies
– Duration and optimal regimen: The precise number of cycles and the best PD‑1 agent (or combination) remain unsettled; the consensus provides flexible frameworks rather than prescriptive cycle counts because randomized comparative data are lacking.
– When to omit adjuvant therapy: While ypT0N0 patients may often safely avoid adjuvant chemotherapy, definitive data are not yet mature; the panel recommends individualized decision‑making and enrolment in registries or trials when possible.
– Application to pMMR tumours: Whether to combine radiation or chemotherapy with ICI to induce immunogenicity in pMMR tumours is under active investigation; routine use outside trials is discouraged.
Future research priorities
– Randomized trials comparing neoadjuvant ICI to standard neoadjuvant chemoradiotherapy in dMMR LARC.
– Trials defining optimal durations, schedules, and combinations (PD‑1 monotherapy vs PD‑1 + CTLA‑4 or ICI + RT/chemo) in both dMMR and pMMR LARC.
– Prospective registries tracking long‑term oncologic and functional outcomes after watch‑and‑wait following ICI.
Practical Implications
For surgeons
– Expect more referrals of dMMR LARC patients seeking organ preservation; coordinate early with medical/radiation oncology and pathology to plan neoadjuvant ICI and structured surveillance.
For medical oncologists
– Incorporate early MMR/MSI testing into initial workflows; counsel patients on the strong rationale for neoadjuvant ICI in dMMR disease and the limits of evidence in pMMR disease.
For multidisciplinary teams and institutions
– Implement standardized MDT pathways, ensure access to reliable MMR/MSI testing (IHC + confirmatory molecular testing), and set up robust watch‑and‑wait surveillance clinics with timely imaging and endoscopy.
For patients
– The consensus offers new options that may allow organ preservation, but requires engagement with intensive follow‑up and acceptance of the possibility of salvage surgery if regrowth occurs.
Clinical vignette (illustrative)
– John, a 58‑year‑old with low‑lying locally advanced rectal adenocarcinoma, undergoes standard staging and is found to have loss of MLH1/PMS2 on IHC and MSI‑H on PCR. After MDT discussion he receives neoadjuvant PD‑1 inhibitor therapy. At 12 weeks he has no residual tumor on endoscopy, MRI or biopsies. Following the consensus guidance he opts for watch‑and‑wait with close surveillance; at 18 months he remains disease‑free with preserved bowel function.
References
– Yang Z, Xia F, Li J, et al. Consensus guidance of immune checkpoint inhibitors in locally advanced rectal cancer. Gut. 2026 Oct 7;75(11):2102-2117. PMID: 41748160.
– Cercek A, et al. PD‑1 blockade in mismatch repair‑deficient, locally advanced rectal cancer. N Engl J Med. 2022;386:2363–2376. (Dostarlimab single‑center series reported dramatic clinical responses.)
– André T, Shiu KK, Kim TW, et al. Pembrolizumab versus chemotherapy for microsatellite‑instability‑high metastatic colorectal cancer (KEYNOTE‑177): final analysis of a randomized, open‑label, phase 3 study. N Engl J Med. 2020;383:2207–2218.
– Chalabi M, Fanchi LF, Dijkstra KK, et al. Neoadjuvant immunotherapy leads to major pathological responses in early‑stage colon cancer. Nat Med. 2020;26:566–576. (The NICHE study showed promising neoadjuvant responses in colorectal cancer.)
– NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®) Rectal Cancer. Latest version available via NCCN.org.
– ESMO Guidelines Committee. Rectal cancer: ESMO Clinical Practice Guidelines. Ann Oncol. (See latest ESMO guideline version.)
Bottom line
The 2026 CSCS consensus in Gut represents an important step in operationalizing checkpoint inhibitor therapy for LARC—defining who should be tested and treated, how to evaluate response, and when organ preservation may be reasonable. It balances enthusiasm for dramatic new results with the need for standardized diagnostics, MDT decision‑making, and careful long‑term monitoring. Clinicians should adopt these standards while supporting prospective data collection and patient enrollment in trials to refine optimal use of immunotherapy across the biologic spectrum of rectal cancer.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.