Hospital Variation in Early Tracheostomy and Life-Sustaining Treatment Withdrawal in Severe TBI: Insights from a Nationwide Study
Highlights
- Early tracheostomy (ET) rates in severe traumatic brain injury (TBI) vary widely across hospitals.
- Hospitals with higher hospital-level tendencies for ET have increased odds of withdrawal of life-sustaining treatment (WLST) after tracheostomy.
- WLST rates post-tracheostomy are age-dependent, increasing with older age groups.
- Practice variability in tracheostomy timing may influence care pathways amid prognostic uncertainty following severe TBI.
Study Background
Severe traumatic brain injury (TBI) is a critical condition characterized by major neurological impairment, often requiring prolonged mechanical ventilation. Tracheostomy, an artificial airway created through the neck, is a common intervention to facilitate prolonged respiratory support. The timing of tracheostomy — particularly early (within 7 days of injury) versus later — remains a topic of ongoing clinical debate due to prognostic uncertainty and complex decision-making regarding goals of care early post-injury.
Decisions surrounding early tracheostomy (ET) are intertwined with considerations about patient prognosis, resource utilization, and quality of life. Concurrently, withdrawal of life-sustaining treatment (WLST) is a critical and ethically sensitive endpoint that reflects decisions about the futility of continued intervention. Understanding hospital-level variation in ET practices and its association with WLST after tracheostomy can shed light on clinical decision-making and potential disparities in care for patients with severe TBI.
Study Design
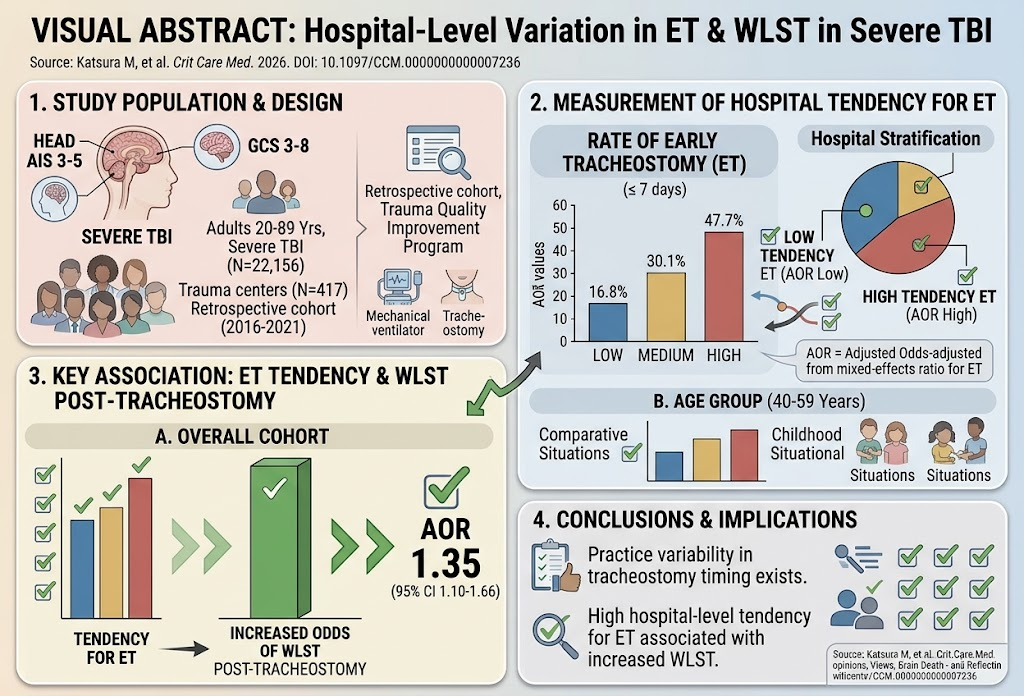
This study is a retrospective cohort analysis utilizing data from the American College of Surgeons Trauma Quality Improvement Program collected between 2016 and 2021. It included adult patients aged 20 to 89 years diagnosed with severe TBI, defined as a head Abbreviated Injury Scale (AIS) score of 3 to 5 and Glasgow Coma Scale (GCS) score of 3 to 8, who received mechanical ventilation and underwent tracheostomy.
The primary exposure was hospital-level tendency for early tracheostomy, operationalized as the adjusted odds ratio (AOR) for performing ET (within 7 days post-injury) derived from mixed-effects logistic regression models. Hospitals were then stratified into low-, medium-, and high-tendency groups based on these AORs.
The primary outcome was the frequency of withdrawal of life-sustaining treatment (WLST) following tracheostomy. The study controlled for patient factors to adjust for case mix and utilized multilevel modeling to evaluate associations between hospital ET tendency and WLST rates across different age strata.
Key Findings
The study cohort consisted of 22,156 patients treated at 417 hospitals nationwide. Hospital-level rates of early tracheostomy varied substantially: 16.8% in low-tendency hospitals, 30.1% in medium-tendency, and 47.7% in high-tendency hospitals.
Withdrawal of life-sustaining treatment following tracheostomy also showed an age-related gradient: 2.6% in patients aged 20-39 years, 4.8% in those aged 40-59 years, and 9.6% in patients 60-89 years old.
After adjusting for patient-level confounders and case mix, a high hospital-level tendency for early tracheostomy was independently associated with increased odds of WLST post-tracheostomy (AOR 1.35; 95% confidence interval [CI] 1.10-1.66; p=0.004). This association was most pronounced in the 40-59-year age group (AOR 1.39; 95% CI 1.01-1.91).
These findings demonstrate notable variability in the timing of tracheostomy practices across US trauma centers and suggest that hospitals favoring early tracheostomy may also have higher rates of subsequent WLST, potentially reflecting differences in prognostic counseling, clinical decision-making, and goals-of-care considerations.
Expert Commentary
This study addresses an important gap in our understanding of how institutional practices around early tracheostomy influence downstream care decisions in severe TBI patients. The observed associations underscore the complexity inherent in managing severe TBI, where prognostic uncertainty often complicates clinical pathways.
The relationship between early tracheostomy and increased likelihood of WLST may represent several underlying phenomena. First, earlier tracheostomy could serve as an institutional marker for more aggressive intervention early in care followed by timely reassessment and possible decision toward WLST when poor prognosis becomes apparent. Alternatively, hospitals with high ET proclivity might differ in communication strategies or end-of-life decision-making processes.
Limitations include the retrospective design and potential for unmeasured confounding related to severity of injury nuances, patient preferences, or institutional policies not captured in the dataset. Additionally, the observational nature precludes conclusions about causality between ET and WLST.
Clinical practice guidelines currently lack specific recommendations on optimal timing for tracheostomy in severe TBI, which may partly explain the observed practice variability. Future prospective studies or randomized trials incorporating prognostic biomarkers and patient-centered outcomes are warranted to clarify the optimal timing of tracheostomy and its impact on care trajectories.
Conclusion
This nationwide analysis reveals meaningful hospital-level variation in early tracheostomy timing among patients with severe TBI undergoing mechanical ventilation. Higher institutional tendencies toward early tracheostomy are associated with increased odds of withdrawal of life-sustaining treatment following the procedure, particularly among middle-aged patients.
The findings highlight the role of prognostic uncertainty and institutional practice patterns in shaping critical care pathways, including decisions to withdraw life-sustaining therapies. These insights call for further research aimed at standardizing tracheostomy timing protocols and enhancing shared decision-making frameworks to optimize outcomes and align treatments with patient values in severe TBI care.
Funding and ClinicalTrials.gov
The study was supported by institutional funding sources as reported by the authors. There is no clinicaltrials.gov registration number listed for this retrospective quality improvement program data analysis.
References
1. Katsura M, Ikenoue T, Ambrose C, Braschi C, Fukuma S, Matsushima K. Hospital-Level Variation in Early Tracheostomy and Withdrawal of Life-Sustaining Treatment in Severe Traumatic Brain Injury: A Nationwide Analysis. Crit Care Med. 2026 Jun 9;54(9):2256-2268. PMID: 42262510.
2. Manley GT, Davis SM, Burke JF, et al. Early versus late tracheostomy for patients with severe traumatic brain injury: a systematic review. J Neurotrauma. 2017;34(19):2541-2548.
3. Badjatia N, Carney N, Crocco TJ, et al. Guidelines for the Management of Severe Traumatic Brain Injury, Fourth Edition. Neurosurgery. 2017;80(1):6-15.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.