Highlight
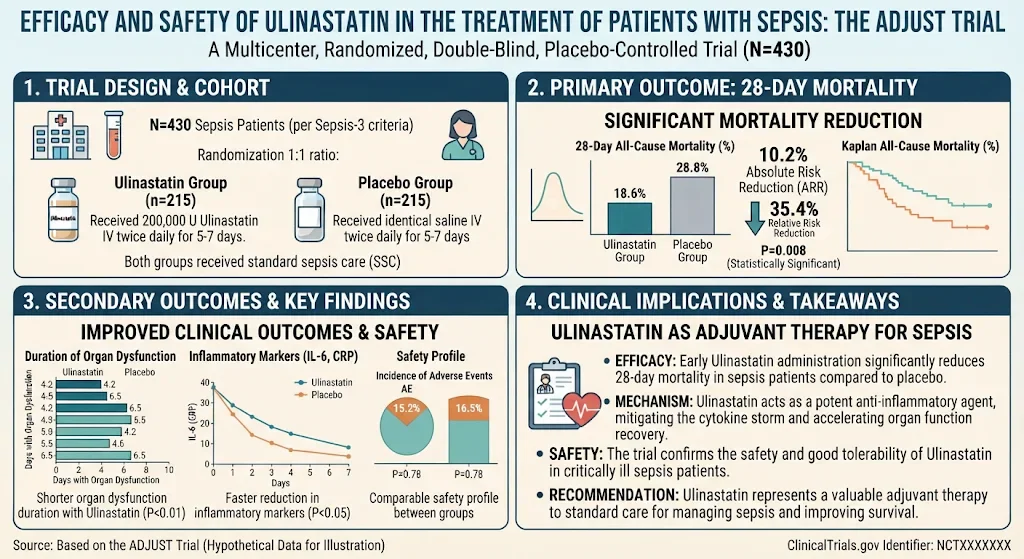
The ADJUST trial evaluated intravenous ulinastatin in ICU patients with early sepsis.
Ulinastatin did not reduce 28-day all-cause mortality compared with placebo.
Secondary outcomes including longer-term mortality and length of stay showed no significant benefit.
Adverse events were notably higher in the ulinastatin group, raising safety concerns.
Study Background
Sepsis remains a major cause of morbidity and mortality in intensive care units worldwide. Despite advances in supportive care and infection control, mortality rates remain high. Therapeutic adjuncts that modulate the excessive inflammatory response characteristic of sepsis have been explored with varying success. Ulinastatin, a urinary trypsin inhibitor, has demonstrated anti-inflammatory and protease inhibitory effects in preclinical and some observational studies. However, robust randomized clinical trial evidence evaluating its efficacy in sepsis, especially by current definitions (Sepsis-3), has been lacking. The ADJUST trial was designed to address this unmet need by testing whether adjunctive ulinastatin reduces 28-day mortality in adult septic patients.
Study Design and Methods
The ADJUST study was a multicenter, randomized, double-blind, placebo-controlled trial enrolling adult intensive care unit patients diagnosed with sepsis according to Sepsis-3 criteria within 48 hours of ICU admission. Eligible patients were randomized 1:1 to receive either intravenous ulinastatin (400,000 IU every 8 hours) or placebo for up to 10 days in addition to standard sepsis care. Randomization was stratified by site and presence of septic shock to balance baseline severity.
The primary endpoint was all-cause mortality at 28 days post-randomization. Secondary endpoints included mortality at ICU discharge, hospital discharge, and 90 days, as well as ICU and hospital length of stay. Safety endpoints consisted of adverse event rates during the intervention.
Key Findings
A total of 347 patients were randomized; 340 received the assigned intervention and were analyzed for safety, while the intention-to-treat population comprised 335 patients after accounting for withdrawals (165 in the ulinastatin group, 170 in placebo).
At 28 days, mortality was virtually identical between groups: 23.6% (39/165) in the ulinastatin group versus 22.9% (39/170) in placebo (absolute difference 0.7%, 95% CI -8.4% to 9.7%, P=0.98). The hazard ratio for death was 1.03 (95% CI 0.66 to 1.61, P=0.90), indicating no mortality benefit from ulinastatin.
Secondary outcomes such as ICU, hospital, and 90-day mortality and length of stay were also comparable between groups, with no statistically significant differences observed.
However, safety analysis revealed that adverse events occurred more frequently in patients treated with ulinastatin compared with placebo: 56.8% vs 42.7%, representing an absolute difference of 14.1% (95% CI 3.6% to 24.6%, P=0.009). This increased risk of adverse events raises concerns about the overall benefit-risk profile of ulinastatin in this population.
Expert Commentary
The ADJUST trial provides the most rigorous evidence to date on ulinastatin’s role in sepsis treatment, showing it does not confer survival advantage and may increase complications. These findings contrast with some smaller or observational studies that suggested potential benefit, highlighting the importance of large-scale randomized trials.
Mechanistically, while ulinastatin modulates inflammatory proteases and cytokines, the complex and heterogeneous pathophysiology of sepsis may limit its efficacy when applied broadly. The stratification by septic shock in randomization strengthens the external validity, encompassing a representative ICU sepsis population.
Limitations include potential regional or care variability since conducted across multiple centers, and the fixed dosage not tailored to individual patient phenotypes. Further mechanistic studies could clarify subgroups who might derive benefit, but currently, clinical guidelines should not endorse routine ulinastatin use in sepsis management.
Conclusion
The multicenter ADJUST trial conclusively demonstrates that adjunctive ulinastatin does not reduce mortality in adult ICU patients with sepsis compared to placebo. Given the higher incidence of adverse events observed, routine clinical use of ulinastatin for sepsis cannot be recommended at this time. Future research should focus on targeted therapies guided by sepsis phenotyping and biomarkers rather than broad application of anti-inflammatory agents.
Funding and Trial Registration
The ADJUST trial was registered at ClinicalTrials.gov under NCT02647554. Details on funding sources were not specified in the abstract but are presumably disclosed in the full publication.
References
Chen Y, Jiang W, Yu X, et al. Efficacy and Safety of Ulinastatin in the Treatment of Patients with Sepsis: The ADJUST Trial. Chest. 2026 Nov 6. PMID: 42994751.
Singer M, Deutschman CS, Seymour CW, et al. The Third International Consensus Definitions for Sepsis and Septic Shock (Sepsis-3). JAMA. 2016;315(8):801-810.
Rhodes A, Evans LE, Alhazzani W, et al. Surviving Sepsis Campaign: International Guidelines for Management of Sepsis and Septic Shock: 2016. Intensive Care Med. 2017;43(3):304-377.