Enhanced Risk Stratification for Pediatric Tracheostomy Hospitalizations: Evaluating a Novel Tracheostomy-Specific Tier System
Highlight
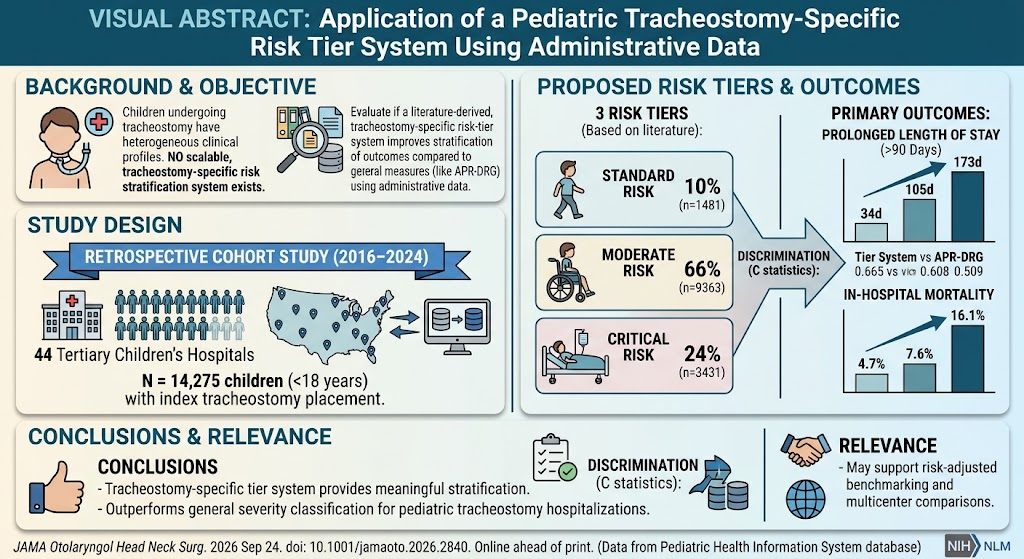
This study introduces a novel pediatric tracheostomy-specific risk-tier system derived from administrative data, demonstrating superior stratification of patient outcomes relative to general severity measures like APR-DRG. The system effectively differentiates risk tiers correlating with prolonged hospital stay and mortality and holds promise for risk-adjusted multicenter benchmarking, despite modest individual prognostic discrimination.
Background
Children undergoing tracheostomy—a procedure to create an airway opening through the neck into the trachea—represent a clinically diverse population with varying underlying conditions, comorbidities, and vulnerability to complications. This heterogeneity complicates efforts to predict outcomes such as length of hospitalization and in-hospital mortality. Currently, general hospital risk-adjustment tools, such as the All Patient Refined Diagnosis Related Group (APR-DRG) system, provide limited granularity and discriminative ability for this subgroup. Given the growing number of pediatric tracheostomy placements and associated resource utilization, a scalable, tracheostomy-specific risk stratification approach that leverages readily available administrative data is clinically valuable for quality assessment and benchmarking across institutions.
Study Design
This retrospective cohort study utilized the Pediatric Health Information System (PHIS) database encompassing 44 tertiary children’s hospitals across the United States. The study population included children under 18 years undergoing their first (index) tracheostomy placement from January 2016 through December 2024. Researchers applied a previously literature-derived tracheostomy-specific risk tier system to classify patients into three risk groups: standard, moderate, and critical risk. Outcomes assessed were prolonged length of stay (defined as hospitalization exceeding 90 days) and in-hospital mortality. The discriminative performance of the risk-tier classification was compared against APR-DRG severity measures using concordance (C) statistics. The study further employed intraclass correlation coefficients to explore variability of outcomes between hospitals.
Key Findings
A total of 14,275 pediatric patients met inclusion criteria with a median age of 0 years (interquartile range, 0–7). The risk-tier distribution was 10% in the standard-risk group, 66% moderate-risk, and 24% critical-risk. Prolonged length of stay substantially increased across tiers: median stays were 34 days (IQR 16–69) in the standard-risk group, 105 days (IQR 54–192) in the moderate-risk group, and 173 days (IQR 104–263) in the critical-risk group.
Correspondingly, mortality rates rose with increased risk: 4.7% in the standard-risk tier, 7.6% in moderate-risk, and 16.1% within the critical-risk group. The tracheostomy-specific tier system demonstrated superior discriminative ability compared with APR-DRG severity classifications. For prolonged hospitalization, the tier system’s C statistic was 0.665 (95% CI, 0.658–0.672) versus 0.521 (95% CI, 0.519–0.524) for APR-DRG. For mortality, it was 0.608 (95% CI, 0.594–0.622) versus 0.509 (95% CI, 0.507–0.511). These findings indicate moderate predictive performance, surpassing the near-random discrimination of APR-DRG. Analysis of intraclass correlation coefficients for hospital-level variance in outcomes suggested negligible between-hospital differences, with coefficients approximating zero, consistent with minimal variation in length of stay and mortality attributable to hospital factors.
Expert Commentary
The study addresses a clinically important gap by stratifying pediatric tracheostomy patients more accurately according to risk using only administrative data. General severity groupings like APR-DRG lack specificity for this heterogeneous patient subset, limiting meaningful benchmarking or outcome prediction. The novel tier framework reflects underlying comorbidity profiles and disease complexity, translating into meaningful differences in resource utilization and mortality risk.
However, the moderate C statistics highlight that although the system improves performance over conventional methods, it still has limitations predicting individual outcomes. This modest discrimination may reflect inherent clinical complexity and unmeasured variables such as functional status, nuances of airway anatomy, or socio-environmental factors. Further refinement combining clinical and administrative data could improve prognostic precision.
Importantly, the low between-hospital variance underscores a consistent standard of care or patient case mix homogenization across participating centers for these measures, reinforcing the potential utility of this system for multicenter quality comparisons without undue concern for institutional bias.
Conclusion
This study validates a pediatric tracheostomy-specific risk-tier system constructed from administrative data that meaningfully stratifies patient risk for prolonged hospitalization and in-hospital mortality. Compared to general severity classifications, it provides enhanced case mix adjustment, supporting its use in benchmarking and multicenter research. Although discrimination at the individual patient level remains modest, the approach sets an important foundation for further validation and refinement with integration of clinical parameters to advance personalized risk prediction and outcome improvement in this vulnerable population.
Funding and Clinical Trials
The original investigation does not specify funding sources or clinical trial registration.
References
Johnson RF, Zaniletti I, Wang CS, Kou YF, Chorney SR. Application of a Pediatric Tracheostomy-Specific Risk Tier System Using Administrative Data. JAMA Otolaryngol Head Neck Surg. 2026 Sep 24. PMID: 42783352.
Feudtner C, et al. Pediatric complex chronic conditions classification system version 2. Pediatrics. 2014;133(6):e1647-54.
Song L, et al. Predictors of adverse outcomes following pediatric tracheostomy placement. Otolaryngol Head Neck Surg. 2018;158(4):589-596.
Keren R, et al. A framework for the comparative effectiveness of pediatric health care: conceptual and practical issues. Pediatrics. 2014;133(1):e209-e218.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.