Unveiling Postpancreatectomy Hemorrhage: Bleeding Sources, Cryptogenic Events, and Predictors of Severity from a Large Cohort Analysis
Highlight
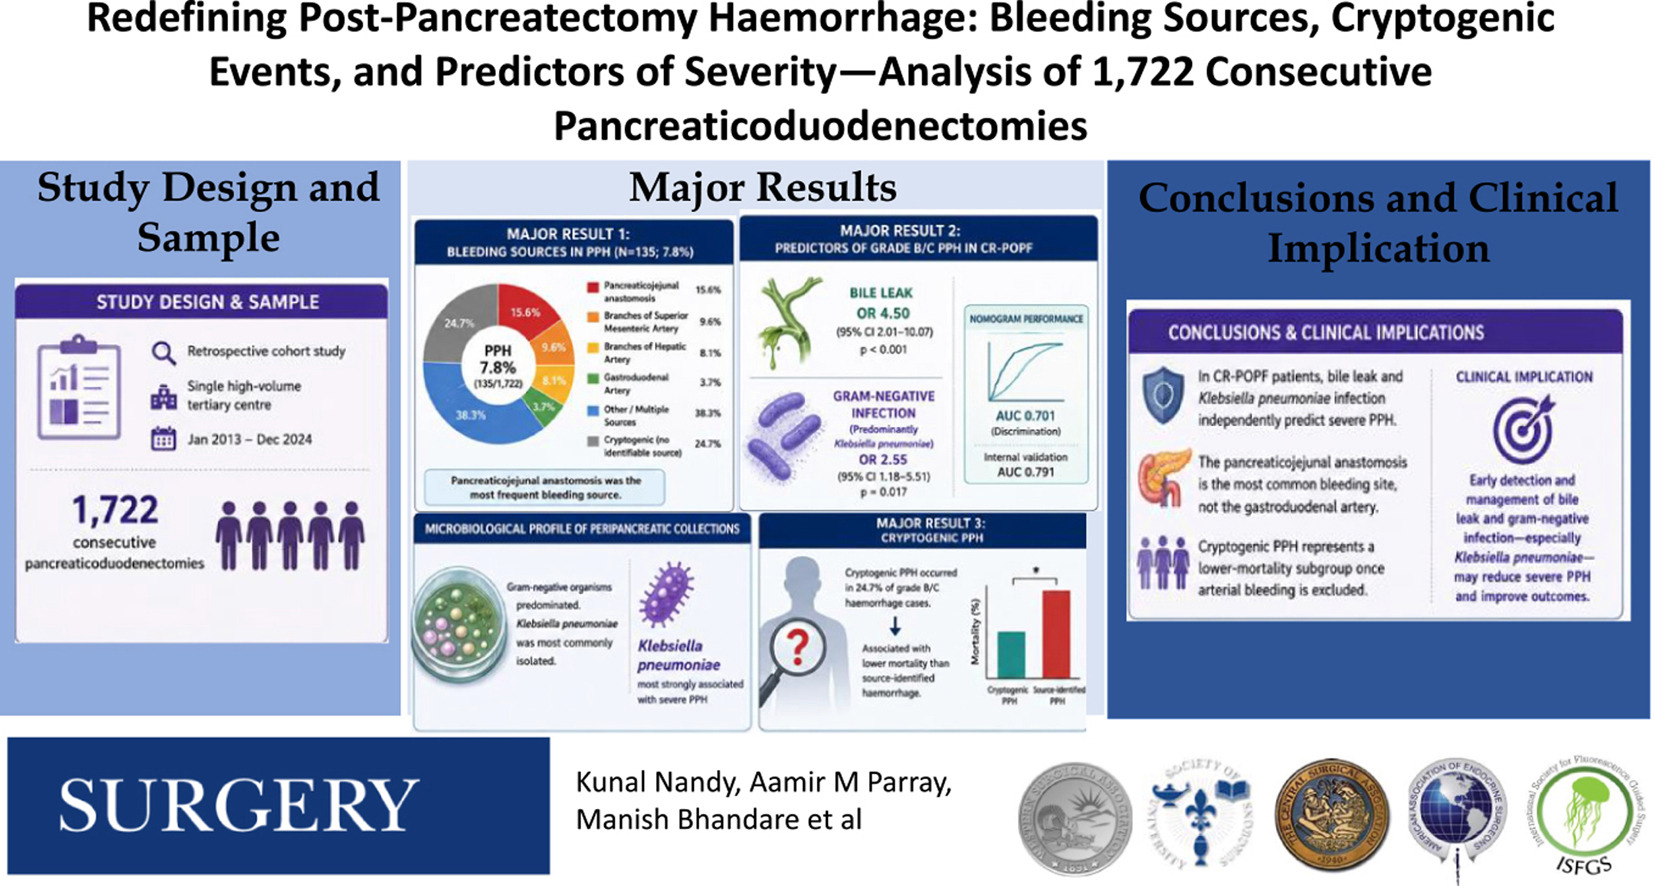
- Postpancreatectomy hemorrhage (PPH) occurred in 7.8% of 1,722 pancreaticoduodenectomies, with grade B/C hemorrhage comprising 5.2%.
- The pancreaticojejunal anastomosis was the most common bleeding source, exceeding traditionally implicated arteries such as the gastroduodenal artery.
- Bile leak and gram-negative infection, predominantly Klebsiella pneumoniae, independently predicted severe PPH in patients with clinically relevant postoperative pancreatic fistula (CR-POPF).
- Cryptogenic hemorrhage, defined as bleeding without an identifiable source, accounted for nearly a quarter of severe PPH cases and was associated with lower mortality.
Study Background
Postpancreatectomy hemorrhage (PPH) is a serious complication following pancreaticoduodenectomy (PD), occurring in 3%-10% of cases and linked with mortality rates up to 20%. The complex anatomy and vascularity around the pancreas, combined with the risk of pancreatic fistula formation, complicate management. Clinically relevant postoperative pancreatic fistula (CR-POPF), which impairs healing and predisposes to infection, amplifies the risk and severity of PPH. Despite advances in surgical techniques, precise characterization of bleeding sources and predictive factors for severe hemorrhage remains incomplete, limiting risk stratification and tailored interventions.
Study Design
This retrospective cohort study analyzed 1,722 consecutive PDs performed from January 2013 to December 2024 at a high-volume tertiary center. Patients were monitored for PPH events, with bleeding sources systematically classified through surgical re-exploration, imaging, and endoscopic assessment. Microbiological analyses of peripancreatic collections were reviewed to identify infectious contributors. The study focused on patients with CR-POPF to identify independent predictors of severe (grade B/C) PPH using multivariable logistic regression. A nomogram incorporating significant predictors was developed and internally validated for clinical utility. Cryptogenic PPH was defined as grade B/C hemorrhage cases without identifiable bleeding sources despite exhaustive evaluation.
Key Findings
PPH occurred in 135 patients (7.8%), with 89 cases (5.2%) classified as severe (grade B/C). Contrary to traditional emphasis on the gastroduodenal artery (GDA) stump, the most frequent bleeding source was the pancreaticojejunal anastomosis (15.6%). Other notable bleeding sites included branches of the superior mesenteric artery (9.6%) and hepatic artery (8.1%), whereas the GDA accounted for only 3.7% of cases.
The presence of bile leak was a powerful independent predictor of severe PPH, showing an odds ratio (OR) of 4.50 (95% confidence interval [CI], 2.01–10.07; P < .001). Additionally, gram-negative infections, mainly Klebsiella pneumoniae, were associated with increased risk (OR 2.55; 95% CI, 1.18–5.51; P = .017). These findings substantiate the clinical interplay between delayed healing, infectious complications, and hemorrhagic risk.
A nomogram integrating bile leak and gram-negative infection demonstrated acceptable discriminatory ability, with an area under the receiver operating characteristic curve (AUC) of 0.701 in the derivation cohort and 0.791 on internal validation, supporting its potential in clinical risk assessment.
Cryptogenic hemorrhage, identified in 24.7% of grade B/C PPH cases, was associated with lower mortality compared to hemorrhages with established bleeding sources. This suggests cryptogenic events might represent less aggressive bleeding or alternative pathophysiological mechanisms once arterial bleeding is excluded.
Expert Commentary
This study challenges traditional paradigms by elevating the pancreaticojejunal anastomosis as the most common bleeding site post-PD, rather than the GDA stump, which has historically been implicated in postpancreatectomy bleeding. The identification of bile leak and gram-negative infection, particularly Klebsiella pneumoniae, as independent predictors highlights the importance of meticulous perioperative infection control and early detection of bile leaks to mitigate hemorrhagic complications.
The concept of cryptogenic hemorrhage is particularly intriguing. Its association with lower mortality suggests a heterogeneous clinical entity that may not require the aggressive interventions reserved for recognized arterial bleeds. Nonetheless, the retrospective design limits causal inferences and may contribute to under-identification of subtle bleeding sources. Prospective validation of the nomogram and further molecular or imaging studies to elucidate cryptogenic hemorrhage pathogenesis are warranted.
Incorporating these findings into surgical practice could refine patient monitoring, prompt earlier interventions for bile leaks, and guide empiric antimicrobial strategies targeting gram-negative organisms to reduce PPH severity.
Conclusion
This extensive analysis of 1,722 pancreaticoduodenectomies redefines the landscape of postpancreatectomy hemorrhage by identifying the pancreaticojejunal anastomosis as the predominant bleeding source and emphasizing bile leak and Klebsiella pneumoniae infection as key predictors of severe hemorrhage in patients with clinically relevant pancreatic fistula. The recognition of cryptogenic hemorrhage as a distinct lower-risk subgroup may influence clinical management and prognostic counseling. Future studies should aim to prospectively validate predictive tools and explore interventions to prevent PPH, potentially improving postoperative outcomes and reducing mortality after pancreatic surgery.
Funding and ClinicalTrials.gov
No specific funding details or clinical trial registration were provided in the study abstract.
References
1. Nandy K, Parray AM, Karun H, et al. Redefining postpancreatectomy hemorrhage: Bleeding sources, cryptogenic events, and predictors of severity-analysis of 1,722 consecutive pancreaticoduodenectomies. Surgery. 2026 Jul 16;198:110460. PMID: 42594685.
2. Bassi C, Marchegiani G, Dervenis C, et al. The 2016 update of the International Study Group (ISGPS) definition and grading of postoperative pancreatic fistula: 11 years after. Surgery. 2017 Jul;161(3):584-591.
3. Tol JA, van Hooft JE, van Santvoort HC, et al. Treatment of postoperative pancreatic fistulas after pancreaticoduodenectomy: A comprehensive review. Dig Surg. 2013;30(2):132-142.
4. Shrikhande SV, Barreto SG, Kaman L, et al. Postpancreatectomy hemorrhage: Prevention and management. Indian J Surg Oncol. 2021 Jun;12(2):288-298.
5. Hackert T, Büchler MW. Bleeding after pancreatic surgery: predicting and managing postpancreatectomy hemorrhage. Curr Opin Gastroenterol. 2015 May;31(3):269-276.
6. Sarr MG, Kendrick ML. Management of postoperative pancreatic fistulas and related hemorrhages. Surg Oncol Clin N Am. 2016 Apr;25(2):279-292.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.