Ultra-Early Versus Early Vasopressin Initiation After Norepinephrine Escalation in Septic Shock: Insights from a Target Trial Emulation
Highlight
- Ultra-early vasopressin initiation (within 0-3 hours) after norepinephrine escalation is linked to lower 28-day mortality compared to early initiation (>3-6 hours) in septic shock patients.
- Ultra-early vasopressin reduces the incidence of renal replacement therapy and medically treated arrhythmias without significantly affecting acute kidney injury rates.
- The study utilized a robust target trial emulation approach, leveraging large electronic health record databases (MIMIC-IV and eICU-CRD) with advanced causal inference methods.
Study Background
Septic shock remains a critical condition with high mortality, characterized by profound circulatory, cellular, and metabolic abnormalities following infection. Vasopressor therapy, typically using norepinephrine, is the cornerstone of hemodynamic support to maintain adequate mean arterial pressure. Adjunctive vasopressin use has been suggested due to its vasoconstrictive properties via V1 receptors, potential to reduce norepinephrine dose, and associated lower catecholamine toxicity. However, the optimal timing of vasopressin initiation after norepinephrine escalation remains controversial. Previous studies and guidelines provide conflicting recommendations, and randomized controlled trials often fail to provide timely data on specific timing strategies. Thus, understanding the impact of ultra-early versus early vasopressin initiation on clinical outcomes is vital for optimizing septic shock management.
Study Design
This study emulated a target trial design using two large, publicly available electronic health record databases—the MIMIC-IV (2008-2022) and eICU-CRD (2014-2015). Eligible participants were adults diagnosed with septic shock who required norepinephrine infusion rates of 0.25 µg/kg/min or higher before any vasopressin use. Two treatment strategies were compared:
- Ultra-early vasopressin initiation: within 0-3 hours after reaching the norepinephrine threshold.
- Early vasopressin initiation: initiation >3 to 6 hours after reaching the norepinephrine threshold.
The clone-censor-weight method was employed to handle treatment assignment and adherence, mitigating immortal time bias. Weighted Cox proportional hazards models were used to estimate hazard ratios (HRs) for mortality and other complications. The primary endpoint was 28-day all-cause mortality, with secondary endpoints including renal replacement therapy (RRT), continuous renal replacement therapy (CRRT), acute kidney injury (AKI), and medically treated arrhythmias.
Key Findings
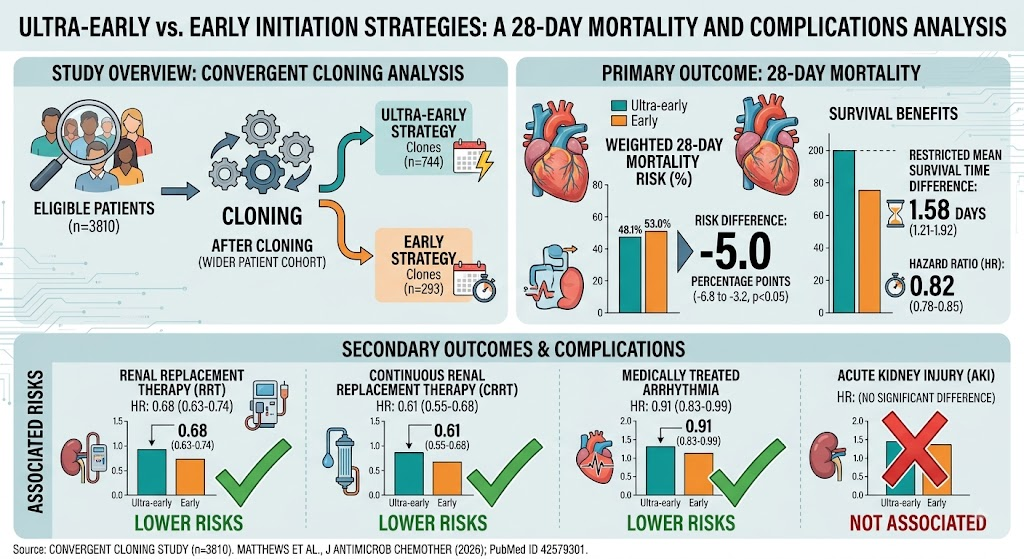
A total of 3,810 eligible patients were identified, and after cloning, 744 clones adhered to the ultra-early strategy and 293 adhered to the early initiation strategy.
- Mortality: The weighted 28-day mortality was 48.1% for the ultra-early group versus 53.0% for the early group. The absolute risk difference was -5.0 percentage points (95% CI -6.8 to -3.2), indicating a significant survival benefit with ultra-early vasopressin initiation. The hazard ratio was 0.82 (95% CI 0.78-0.85), confirming a 18% relative reduction in mortality hazard.
- Survival Time: The restricted mean survival time difference was 1.58 days favoring ultra-early initiation (95% CI 1.21-1.92), reflecting clinically meaningful prolongation of survival.
- Renal Outcomes: Ultra-early vasopressin use was associated with a lower hazard for renal replacement therapy (HR 0.68; 95% CI 0.63-0.74) and continuous renal replacement therapy (HR 0.61; 95% CI 0.55-0.68). However, rates of acute kidney injury per se were not significantly reduced, suggesting benefit on severe renal impairment requiring replacement rather than all AKI events.
- Arrhythmias: There was a modest but statistically significant reduction in medically treated arrhythmias with ultra-early vasopressin (HR 0.91; 95% CI 0.83-0.99), likely reflecting catecholamine sparing effects.
Expert Commentary
This study strengthens the clinical rationale for initiating vasopressin earlier than conventionally practiced once norepinephrine escalates beyond a moderate threshold. The observed mortality benefit aligns with vasopressin’s known pathophysiologic roles in restoring vascular tone and reducing exposure to high-dose catecholamines, which are associated with arrhythmogenesis and organ dysfunction. The use of robust target trial emulation methodology minimizes confounding typical of retrospective analyses and enhances causal interpretability.
Nonetheless, the observational nature and reliance on electronic health record data impose limitations related to potential residual confounding, misclassification of septic shock timing, and unmeasured clinical decision factors such as vasopressor dosing titration nuances and fluid management. Furthermore, findings may not fully generalize across all clinical settings, especially outside the US or in low-resource environments.
Notably, the lack of significant impact on AKI incidence challenges the assumption that early vasopressin universally protects the kidney, indicating that renal protection may manifest primarily by preventing progression to more severe dysfunction.
Conclusion
Among adults with septic shock requiring high-dose norepinephrine, initiating adjunctive vasopressin ultra-early (within 3 hours) after norepinephrine escalation significantly reduces 28-day mortality and the need for renal replacement therapy compared to initiating vasopressin later between 3 to 6 hours. These findings advocate for earlier vasopressin use in septic shock management algorithms to improve patient outcomes. Future randomized controlled trials should validate the optimal timing thresholds and assess long-term safety profiles.
Funding and ClinicalTrials.gov
This study was conducted using publicly available datasets without industry funding. Registration details for the target trial emulation were not specified.
References
1. Russell JA et al. Vasopressin versus norepinephrine infusion in patients with septic shock. N Engl J Med. 2008;358(9):877-887.
2. Gordon AC et al. Effect of early vasopressin vs norepinephrine on kidney failure in patients with septic shock: The VANISH randomized clinical trial. JAMA. 2016;316(5):509-518.
3. Evans L et al. Surviving Sepsis Campaign: International Guidelines for Management of Sepsis and Septic Shock 2021. Intensive Care Med. 2021;47(11):1181-1247.
4. Hernán MA, Robins JM. Using Big Data to Emulate a Target Trial When a Randomized Trial Is Not Available. Am J Epidemiol. 2016;183(8):758-764.
5. Johnson AEW et al. MIMIC-IV, a freely accessible electronic health record database for critical care research. Sci Data. 2023;10(1):250.
6.Nakashima T, Ichinomiya T, Nakajima M, Shinozaki T, Shibata J, Goto T, Sato S, Hara T. Ultra-early versus early adjunctive vasopressin initiation after norepinephrine escalation in septic shock: a target trial emulation. Intensive Care Med. 2026 Aug 11. doi: 10.1007/s00134-026-08575-3. Epub ahead of print. PMID: 42578996.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.