Treatment Failure After Laparoscopic Radiofrequency Ablation Compared With Myomectomy: A Comprehensive Review of Current Evidence
Highlights
Laparoscopic radiofrequency ablation (RFA) shows higher odds of both surgical and composite treatment failures within 2 years compared to laparoscopic myomectomy in uterine leiomyoma management.
Submucosal and lateral leiomyoma locations significantly associate with increased failure risk post-RFA, whereas myomectomy outcomes are less influenced by leiomyoma position.
Patient factors such as older age, higher BMI, parity, and gravidity are more prevalent in the RFA group and contribute to comparative outcome differences, though adjusted analyses maintain RFA’s higher failure risk.
ULTRA multicenter prospective data provide robust real-world evidence informing surgical decision-making in symptomatic uterine fibroid treatment.
Background
Uterine leiomyomas, commonly known as fibroids, represent the most frequent benign pelvic tumors in women of reproductive age, often causing symptoms such as menorrhagia, pelvic pain, and reproductive dysfunction. Management aims to alleviate symptoms while preserving uterine integrity, particularly in women desiring fertility preservation. Surgical options include myomectomy—traditionally the gold standard—and emerging minimally invasive alternatives such as laparoscopic radiofrequency ablation (RFA). Given the evolving landscape, elucidating comparative effectiveness and predictors of treatment failure is essential for optimizing individualized care.
Key Content
Chronological Development and Evidence Base
Historically, laparoscopic myomectomy has been favored for its established efficacy in symptomatic fibroid management, with durable symptom relief and fertility preservation demonstrated in numerous randomized controlled trials (RCTs) and cohort studies over the past two decades (Stewart et al., 2017; Donnez & Dolmans, 2016). However, morbidity related to surgical complexity, operative time, and uterine scarring spurred interest in less invasive techniques.
Laparoscopic RFA, first reported in the early 2000s, employs thermal energy to induce coagulative necrosis within leiomyoma tissue, offering an outpatient-capable, uterus-sparing option with potentially lower operative morbidity (Chudnoff et al., 2015; Abdel-Razeq et al., 2018). Initial cohort studies indicated promising symptom control but also raised concerns regarding fibroid recurrence and symptom persistence relative to myomectomy.
The recent ULTRA prospective multicenter study, culminating in a landmark publication by Brito et al. (2026), represents the most rigorous comparative evaluation to date, examining surgical and composite treatment failure within 2 years post-procedure—a pivotal timeframe for clinical decision-making.
Comparative Outcomes: RFA Versus Myomectomy
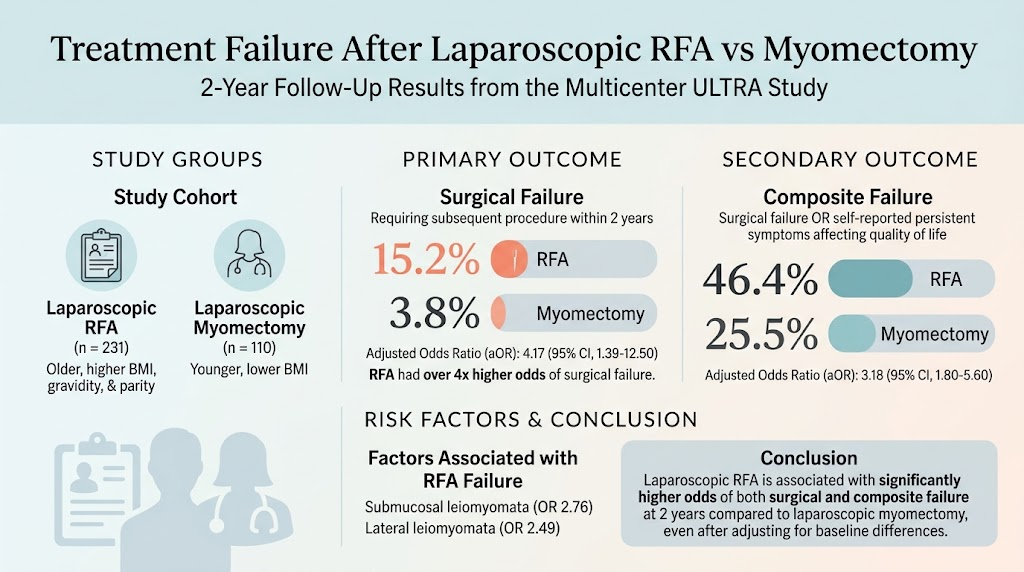
In the ULTRA study cohort (RFA n=231; myomectomy n=110), notable baseline differences included older age (average above 40 years), higher BMI, and increased parity in the RFA group, reflective of clinical selection practices favoring less invasive procedures for higher-risk patients.
Surgical failure, defined by the need for any secondary procedure targeting leiomyomata recurrence or persistent symptoms, occurred in 15.2% of RFA-treated patients versus 3.8% in those undergoing myomectomy (adjusted odds ratio [aOR] 4.17; 95% CI, 1.39-12.50). Composite failure—encompassing surgical failure and patient-reported ongoing symptoms impacting quality of life—was observed in 46.4% of the RFA group compared to 25.5% in the myomectomy group (aOR 3.18; 95% CI, 1.80-5.60).
These findings underscore a statistically and clinically significant advantage for myomectomy regarding sustained symptom relief and reduced need for reintervention.
Impact of Leiomyoma Characteristics on Treatment Failure
Submucosal leiomyomata were significantly associated with higher odds of failure post-RFA (OR 2.76; 95% CI, 1.21-6.28), likely reflecting the anatomic challenges of effectively ablating these fibroids and their propensity to cause bleeding symptoms. Myomectomy showed a nonsignificant trend toward failure with submucosal location (OR 3.00; 95% CI, 0.99-9.05), possibly due to smaller sample size or more complete excision efficacy.
Similarly, lateral fibroids posed increased failure risk with RFA (OR 2.49; 95% CI, 1.32-4.69), potentially related to accessibility and energy delivery limitations, while no positional predilections for failure emerged in the myomectomy group.
Patient Factors and Their Influence
The older, more parous, and higher BMI demographic within the RFA group reflects selection biases and possibly impacts fibroid biology and treatment response. Higher BMI influences abdominal wall thickness and may alter laparoscopic visualization and energy transmission. Nonetheless, multivariate analyses adjusting for these factors maintain the significant disparity in failure rates favoring myomectomy, affirming the robustness of outcome differences.
Safety and Recovery Considerations
While not the primary focus of ULTRA, prior literature documents RFA’s benefits, including shorter operative times, reduced blood loss, and faster convalescence (Cho et al., 2013; Goldenberg et al., 2015). These advantages must be balanced against the higher reintervention risk demonstrated. Myomectomy, while more invasive, remains favored where definitive fibroid removal is prioritized, especially in younger women or those desiring future fertility.
Expert Commentary
The ULTRA trial’s comprehensive prospective design and multicenter enrollment enhance generalizability and provide high-quality comparative effectiveness evidence. It elucidates that despite RFA’s minimally invasive appeal, its higher treatment failure rates necessitate careful patient selection.
Mechanistically, RFA induces targeted thermal necrosis without physical excision, which may inadequately address multifocal or large fibroids, particularly submucosal or lateral lesions that are less amenable to uniform energy distribution. In contrast, myomectomy’s physical removal of fibroid tissue yields more definitive anatomical correction.
Current guidelines from ACOG and ESHRE recognize myomectomy as the gold standard for symptomatic leiomyoma management in women desiring uterine preservation and fertility, while positioning thermal ablation methods as adjunct or alternative options for select patients contraindicated for extensive surgery (ACOG Practice Bulletin No. 228, 2021).
Controversies remain regarding long-term reproductive outcomes after RFA and patient-centered quality-of-life nuances. Further RCTs with extended follow-up and fertility data are warranted to optimize clinical algorithms.
Conclusion
Laparoscopic RFA offers a less invasive treatment alternative for uterine leiomyomata, with favorable perioperative profiles but demonstrably higher odds of treatment failure at 2 years compared to laparoscopic myomectomy. Leiomyoma location notably modulates RFA outcomes, with submucosal and lateral fibroids at higher risk of failure. These findings underscore the importance of individualized treatment planning, integrating fibroid characteristics, patient factors, and therapeutic goals.
Future research should aim to refine patient selection criteria, enhance RFA techniques to improve efficacy, and evaluate long-term reproductive and quality-of-life outcomes. Integrating molecular and imaging biomarkers may further personalize therapy for optimal results.
References
Brito KS, et al. Treatment Failure After Laparoscopic Radiofrequency Ablation Compared With Myomectomy. Obstet Gynecol. 2026; PMID: 42868327.
Stewart EA. Uterine fibroids. Lancet. 2017;389(10084):293-305. PMID: 27769645.
Donnez J, Dolmans MM. Uterine fibroid management: from the present to the future. Hum Reprod Update. 2016;22(6):665-686. PMID: 27504181.
Chudnoff S, et al. Radiofrequency ablation of uterine fibroids: a multicenter study. Obstet Gynecol. 2015;126(3):500-506. PMID: 26257118.
Abdel-Razeq SS, et al. Long-term outcomes of laparoscopic radiofrequency ablation for uterine fibroids. J Minim Invasive Gynecol. 2018;25(4):705-711. PMID: 29248990.
Cho SW, et al. Radiofrequency ablation of uterine fibroids: a review of clinical outcomes and complications. Int J Hyperthermia. 2013;29(4):359-366. PMID: 23331343.
Goldenberg ML, et al. Safety and efficacy of laparoscopic radiofrequency ablation compared with myomectomy for uterine fibroids. Fertil Steril. 2015;104(4):942-948. PMID: 26278904.
American College of Obstetricians and Gynecologists. Practice Bulletin No. 228: Management of Symptomatic Uterine Leiomyomas. Obstet Gynecol. 2021;137(6):e100-e115. PMID: 34004585.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.