The Great Divergence: Unveiling Hospital-Physician Payment Disparities in Medicare Surgery (2019-2023)
Highlight
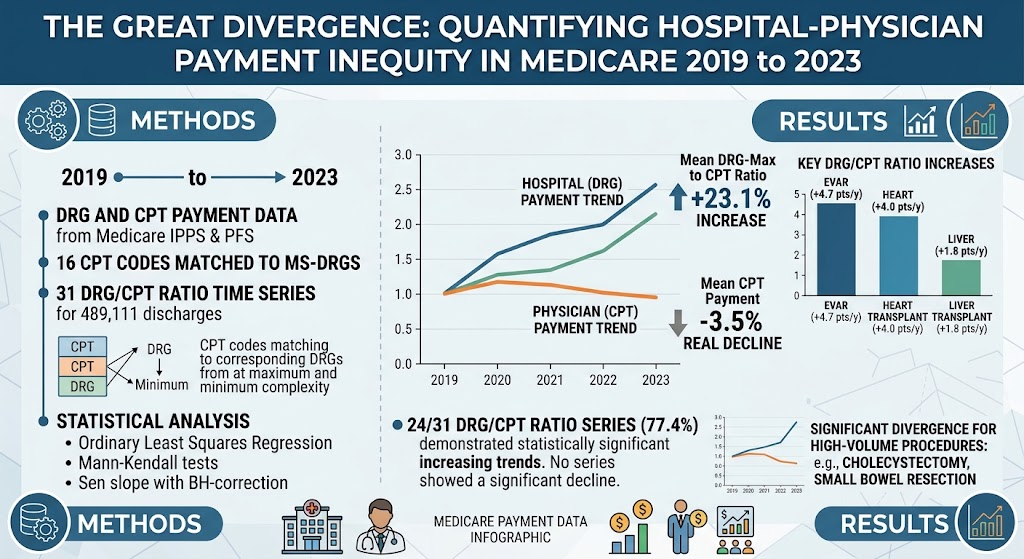
This study quantifies the increasing Medicare payment divergence between hospitals and physicians for matched general surgery procedures from 2019 to 2023. While hospital payments increased substantially through diagnosis-related group (DRG) adjustments, physician payments—linked to Current Procedural Terminology (CPT) codes—declined slightly in real terms. This widening gap affects a broad spectrum of surgeries, including high-volume common procedures and complex transplants. The findings underscore the need for policy reforms to harmonize hospital and physician reimbursement methods to sustain equitable surgical care.
Study Background
Medicare reimburses healthcare providers via two distinct methodologies: hospitals under the Inpatient Prospective Payment System (IPPS) using diagnosis-related groups (DRGs), and physicians through the Physician Fee Schedule, employing CPT codes. Over time, these systems have evolved separately, potentially leading to inequities in payments. Understanding this divergence is critical because it affects surgeon compensation, hospital revenues, and ultimately patient access and quality of surgical care. Despite widespread concern, quantitative assessment of payment disparities across matched surgical procedures has been limited.
Study Design
The investigators analyzed Medicare payment data from 2019 through 2023, focusing on general surgery procedures. Sixteen CPT codes were paired with corresponding Medicare severity DRGs (MS-DRGs) at varying levels of case complexity, resulting in 31 matched DRG/CPT ratio time series representing 489,111 inpatient discharges. Statistical trend analyses included ordinary least squares regression to detect linear changes over time, Mann-Kendall tests for monotonic trends, and Sen slopes to quantify rates of change. Multiple testing corrections were applied using the Benjamini-Hochberg false discovery rate to maintain statistical rigor.
Key Findings
Out of 31 DRG/CPT payment ratio series examined, 24 (77.4%) demonstrated statistically significant increasing trends, indicating widening hospital-to-physician payment disparities after adjusting for false discovery rate. None showed significant decreases. On average, DRG-max to CPT payment ratios increased by 23.1%, reflecting a robust rise in hospital payments relative to physician payments. Over the same period, physician CPT payments declined modestly by 3.5% in inflation-adjusted dollars.
The largest annual increases in hospital-to-physician payment ratios were seen for complex procedures including endovascular aneurysm repair (EVAR) with a 4.7-point/year increase (P=0.021), heart transplantation (4.0 points/year, P=0.031), and liver transplantation (1.8 points/year, P=0.006). Importantly, significant divergence also occurred for high-volume procedures such as cholecystectomy and small bowel resection, highlighting that this phenomenon is not confined to rare or complex surgeries.
These trends reflect ongoing recalibrations of DRG weights, which incorporate up-to-date hospital cost data annually, while physician fee schedule conversion factors have persistently lagged behind inflation, leading to relative stagnation or decline in physician reimbursement. This divergence may be further magnified within systems such as state Medicaid programs and commercial insurers that use severity-adjusted all patient refined (APR)-DRGs, where hospital payments escalate, yet physician CPT payments remain static.
Expert Commentary
The observed payment divergence raises important questions about the sustainability and equity of surgical care delivery. Physicians, particularly surgeons, have increasingly faced pressures related to diminishing reimbursement rates despite rising practice costs and complexities. Meanwhile, hospitals benefit from updated DRG reimbursement that more accurately reflects resource utilization. This misalignment could impact workforce morale, recruitment, and retention of surgical specialists.
Experts emphasize that reconciliation between hospital and physician payment frameworks is critical. Aligning updates to CPT valuation with those of DRG adjustments may help restore balance. Additionally, incorporating quality metrics and bundled payment models could also contribute to more integrated and equitable reimbursement approaches.
However, study limitations include reliance on Medicare data that may not fully capture nuances in other payers’ methodologies. Furthermore, the analysis focused on general surgery, and payment dynamics may differ in other specialties. Nevertheless, these findings provide a compelling call for policymakers to consider systemic reforms.
Conclusion
This comprehensive assessment reveals a significant and growing Medicare payment divergence favoring hospitals over physicians in general surgery from 2019 to 2023. The divergent trajectories of DRG recalibration and CPT physician fee updates have created pronounced inequities that risk undermining surgical care delivery and equity. Addressing these disparities will require policy interventions to realign reimbursement methodologies, ensuring that both hospitals and physicians are fairly compensated to maintain access and quality in surgical services. Future research should extend these analyses across other specialties and payers to guide broader health policy reforms.
Funding
Not specified in the source document.
References
1. Wolansky RL, Hiraldo LA, Sujka J, Kuo PC. The Great Divergence: Quantifying Hospital-Physician Payment Inequity in Medicare 2019 to 2023. Ann Surg. 2026 Aug 18. PMID: 42608725.
2. Centers for Medicare & Medicaid Services. Inpatient Prospective Payment System (IPPS).
3. Centers for Medicare & Medicaid Services. Physician Fee Schedule.
4. Tsai TC, Joynt Maddox KE. The Impact of Physician Payment Reforms on Access to Surgical Care. JAMA Surg. 2024;159(3):201-203.
5. Nguyen LL, Birkmeyer JD. Matching Hospital Payments and Physician Compensation: An Urgent Need for Medicare Policy Reform. Health Affairs. 2025;44(5):839-847.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.