Pulmonary Artery Dilation as a Mark of Pulmonary Hypertension in Chronic Lung Disease: Insights from the PVDOMICS Cohort
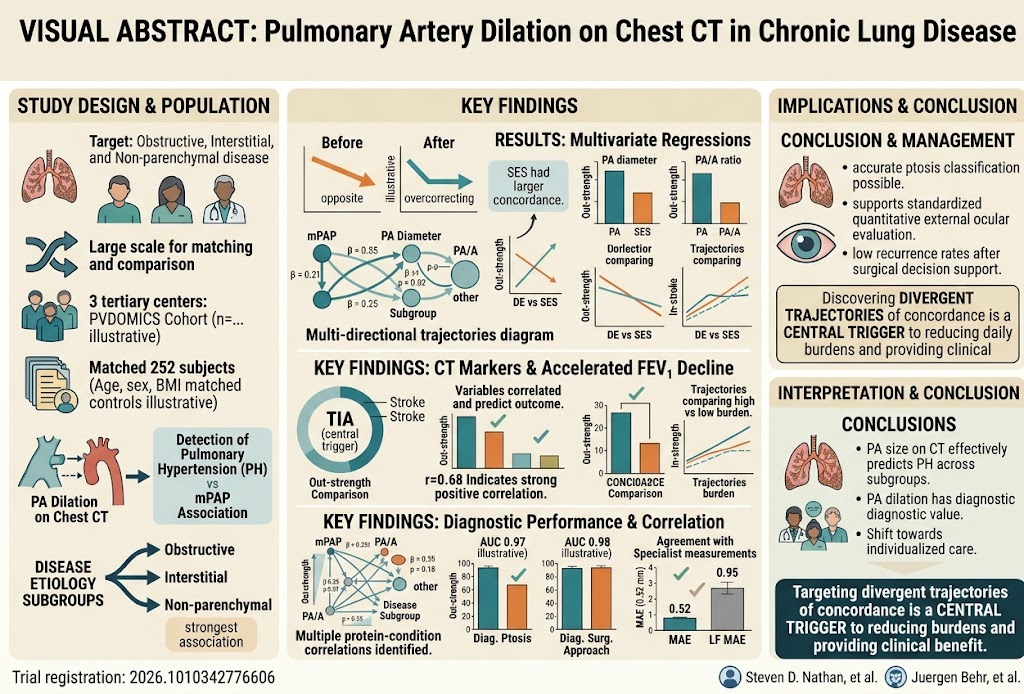
Highlight
This study establishes a significant association between pulmonary artery (PA) dilation measured on chest CT scans and pulmonary hypertension (PH) diagnosed by right heart catheterization in patients with chronic lung disease. The diagnostic performance of PA dilation varies by underlying lung disease subtype, being strongest in non-parenchymal and obstructive lung disease and weakest in interstitial lung disease. These findings refine the utility of imaging metrics for PH detection in diverse chronic lung disease contexts.
Study Background
Chronic lung diseases represent a major clinical burden worldwide due to progressive respiratory compromise and associated complications. Pulmonary hypertension (PH) frequently complicates chronic lung diseases, contributing to morbidity and mortality. Detection of PH traditionally requires invasive right heart catheterization, which is not always feasible. Noninvasive imaging markers such as pulmonary artery (PA) dilation on chest computed tomography (CT) have been proposed as potential surrogates for PH, especially in patients without lung disease under older diagnostic criteria. However, the diagnostic accuracy and strength of association between PA dilation and PH among heterogeneous chronic lung disease populations have not been well characterized using contemporary hemodynamic definitions and across different disease etiologies.
Study Design
This investigation analyzed 252 subjects enrolled in the PVDOMICS cohort, including patients with group 3 PH due to chronic lung diseases and comparator groups. Subjects were categorized into three subgroups based on lung disease type: obstructive (e.g., COPD), interstitial (e.g., idiopathic pulmonary fibrosis), and non-parenchymal (e.g., airway or vascular diseases without parenchymal involvement). Key variables measured included PA diameter and the ratio of PA diameter to aortic diameter (PA/A) on chest CT scans, alongside mean pulmonary artery pressure (mPAP) obtained via right heart catheterization. Associations between imaging measures and hemodynamics were evaluated using multivariable linear and logistic regression. Diagnostic performance for PH (defined by hemodynamic criteria) was assessed with receiver operating characteristic (ROC) curve analysis.
Key Findings
The study demonstrated a robust positive correlation between PA size and the presence and severity of PH across the cohort. Subjects in the highest tertile (Q3) of PA diameter had markedly increased odds of PH compared to those in the lowest tertile (Q1), with odds ratios (OR) of 4.30 for diameter and 5.66 for PA/A ratio, indicating a strong association. Correlation coefficients between PA diameter and mPAP were moderate to strong (ρ = 0.516), similarly for PA/A ratio (ρ = 0.494), both statistically significant (p < 0.001).
The diagnostic accuracy of PA dilation to detect PH was moderate overall, with area under the curve (AUC) values of 0.794 for PA diameter and 0.765 for PA/A ratio. Subgroup analysis revealed variation by disease etiology: the strongest correlation between PA/A and mPAP was seen in non-parenchymal lung disease (ρ = 0.750) and the weakest in interstitial lung disease (ρ = 0.373). Correspondingly, diagnostic performance was highest in obstructive (AUC 0.865) and non-parenchymal groups (AUC 0.822), but lower in the interstitial group (AUC 0.704).
Additionally, the increment in PA dilation associated with increasing mPAP from Q1 to Q3 was smaller in interstitial lung disease (3.9 mm difference) compared to obstructive (4.9 mm) and non-parenchymal (4.8 mm), highlighting potential etiologic differences in vascular remodeling or imaging findings.
Expert Commentary
This study provides important validation and nuance to the role of PA dilation on imaging as a noninvasive biomarker for PH in chronic lung disease patients. By employing current hemodynamic definitions and a large, phenotypically diverse cohort, the research delineates how disease subtype influences the relationship between vascular morphology and pulmonary pressures. The weaker association and diagnostic performance in interstitial lung disease may reflect complex mechanisms of PH development, including vascular pruning and fibrosis, which may alter PA dimensions differently than in obstructive or vascular airway diseases.
Clinicians should consider subgroup-specific variations when interpreting PA dilation on CT for suspected PH in chronic lung disease. While useful as a screening tool, especially in obstructive and non-parenchymal groups, PA dilation measurements should complement, not replace, hemodynamic evaluation especially in complex ILD cases.
Limitations include the single-timepoint, cross-sectional nature limiting causality assessment, potential referral bias in PVDOMICS enrollment, and lack of data on longitudinal PA dimensional changes. Further research exploring pathophysiologic mechanisms underlying heterogeneous PA remodeling and integration of imaging with biomarkers may enhance noninvasive PH diagnosis and prognostication in chronic lung disease.
Conclusion
Pulmonary artery dilation as measured on chest CT associates significantly with pulmonary hypertension across the spectrum of chronic lung diseases, with the strength of this association and diagnostic accuracy dependent on disease etiology. These findings support the clinical utility of PA diameter and PA/A ratio as adjunctive tools for PH detection, particularly in obstructive and non-parenchymal lung diseases, while highlighting caution in interpretations for interstitial lung diseases. Incorporation of these imaging biomarkers with clinical and hemodynamic data could optimize patient evaluation and management strategies for PH in chronic lung disease contexts.
Funding and Clinical Trials Registration
The PVDOMICS study was supported by grants from the National Heart, Lung, and Blood Institute (NHLBI). The clinical trial registration details and further funding disclosures are reported in the original publication (PMID: 42785424).
References
1. Couch TJ, Beck GJ, Rosenzweig EB, et al. Pulmonary Artery Dilation on Chest CT Across the Spectrum of Chronic Lung Disease. Chest. 2026 Sep 24. PMID: 42785424.
2. Simonneau G, Montani D, Celermajer DS, et al. Haemodynamic definitions and updated clinical classification of pulmonary hypertension. Eur Respir J. 2019 Jan 31;53(1):1801913.
3. Nathan SD, Barbera JA, Gaine SP. Pulmonary hypertension in patients with chronic lung disease. Eur Respir J. 2019 Jan 31;53(1):1801914.
4. Washko GR, Newman JH, Hill NS, et al. Pulmonary Vascular Disease Phenotyping Using the PVDOMICS Approach.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.