Navigating Prolactinomas in Pregnancy: An Evidence-Based Approach for Optimal Maternal and Fetal Outcomes
Introduction
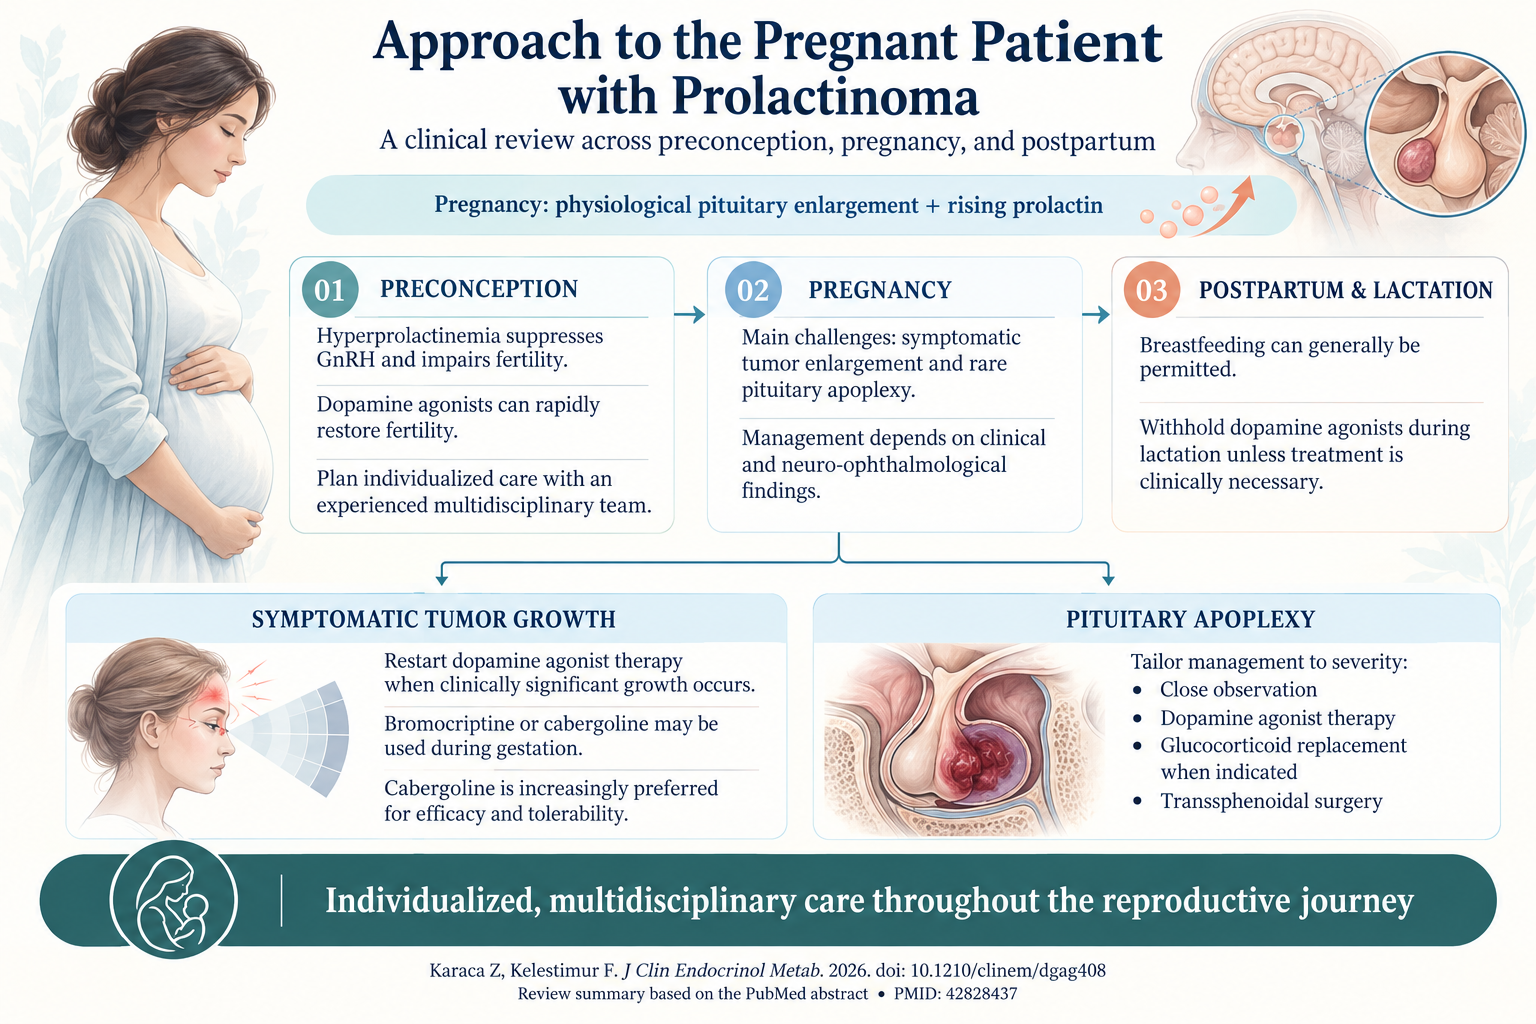
Prolactinomas represent approximately 50% of pituitary adenomas and predominantly affect women of reproductive age. These hormonally active tumors secrete prolactin, leading to hyperprolactinemia, which disrupts the hypothalamic-pituitary-gonadal axis and commonly causes infertility. With advances in dopamine agonist therapy, fertility can be rapidly restored, allowing affected women to conceive. However, pregnancy introduces notable physiological changes—including pituitary gland enlargement and further elevation of prolactin levels—posing significant challenges in management. This comprehensive review synthesizes evidence-based strategies for managing prolactinomas before conception, throughout pregnancy, and postpartum to optimize maternal and fetal outcomes.
Highlight
- Prolactinomas are a leading cause of hyperprolactinemia-induced infertility in women, effectively treated by dopamine agonists.
- Pregnancy physiologically enlarges the anterior pituitary and increases prolactin levels, increasing risk of symptomatic tumor growth or pituitary apoplexy.
- Bromocriptine and cabergoline are safe during pregnancy; cabergoline is favored for its superior efficacy and tolerability.
- Multidisciplinary individualized management throughout preconception, gestation, and postpartum, including careful monitoring and selective dopamine agonist use, ensures best outcomes.
Study Background and Clinical Context
Prolactinomas result from hyperplasia or adenoma formation of lactotroph cells in the anterior pituitary. The resulting hypersecretion of prolactin suppresses hypothalamic secretion of gonadotropin-releasing hormone (GnRH), thereby inhibiting luteinizing hormone (LH) and follicle-stimulating hormone (FSH) release. This leads to anovulation and infertility, making prolactinomas a key treatable cause of reproductive dysfunction in women of childbearing age. Pregnancy in women with prolactinomas must be carefully managed due to physiological pituitary enlargement secondary to placental estrogen and associated risks including tumor growth and, though rare, pituitary apoplexy (hemorrhage or infarction within the tumor).
Study Design and Patient Management Strategies
Although large randomized controlled trials specifically addressing prolactinoma management during pregnancy are scarce due to ethical and practical constraints, numerous prospective cohort studies, retrospective analyses, and clinical guidelines inform current practice. The management approach encompasses three stages:
Preconception
– Confirm diagnosis with magnetic resonance imaging (MRI) and baseline prolactin measurements.
– Initiate dopamine agonist therapy, typically bromocriptine or cabergoline, to normalize prolactin levels and restore ovulation.
– Surgical intervention is considered when dopaminergic therapy is contraindicated or ineffective.
– Advise conception once prolactin normalizes and tumor size is controlled.
During Pregnancy
– Discontinue dopamine agonist upon pregnancy confirmation for most patients with microprolactinomas and noninvasive macroadenomas.
– Monitor clinically and with imaging reserved for symptomatic tumor enlargement (headache, visual disturbances).
– Reinitiate dopamine agonist therapy if significant tumor growth occurs.
– Bromocriptine, supported by historical safety data, and cabergoline, with increasing favorable safety evidence, are options.
Postpartum and Lactation
– Breastfeeding is generally safe and encouraged.
– Dopamine agonists are withheld during lactation unless tumors enlarge or symptoms require treatment.
– Regular endocrine follow-up and prolactin monitoring recommended.
Key Findings and Clinical Evidence
Hyperprolactinemia due to prolactinomas is effectively managed in reproductive-age women using dopamine agonists—primarily bromocriptine and cabergoline—both of which normalize serum prolactin levels and induce tumor shrinkage. This restores GnRH pulsatility and ovulatory cycles, enabling successful conception.
Physiological pituitary enlargement in pregnancy stems mainly from escalating placental estrogen levels, which stimulate lactotroph hyperplasia, sometimes up to 30-40% increase in pituitary volume. This creates a risk of tumor mass effect symptoms such as headache and visual field deficits, especially in macroadenomas.
The risk of symptomatic tumor enlargement during pregnancy is approximately 2-3% for microadenomas but rises to around 20-30% for macroadenomas without prior debulking therapy. Pituitary apoplexy is rare but serious, necessitating prompt recognition and intervention.
Current evidence supports the safe use of bromocriptine throughout pregnancy, with decade-long data demonstrating minimal risk to fetal development, miscarriage, or congenital anomalies. Cabergoline, offering a longer half-life and improved tolerability, is increasingly employed with accumulating data confirming the absence of teratogenicity or adverse pregnancy outcomes.
In cases of symptomatic tumor growth or apoplexy during pregnancy, dopamine agonist therapy should be promptly restarted. Glucocorticoid replacement may be necessary if hypopituitarism develops. Surgical intervention, typically transsphenoidal resection, is reserved for patients with severe neuro-ophthalmologic compromise refractory to medical therapy.
Breastfeeding stimulates endogenous prolactin but is not generally contraindicated. Dopamine agonists suppress lactation and are thus withheld during breastfeeding unless tumor control mandates pharmacologic intervention.
Expert Commentary
Current clinical guidelines, such as those from the Endocrine Society and Pituitary Society, advocate for individualized, multidisciplinary care involving endocrinologists, obstetricians, neurosurgeons, and ophthalmologists. Particularly critical is detailed counseling regarding risks of tumor growth, drug safety profiles, and lactation considerations. Emerging evidence suggests cabergoline’s superior efficacy and convenience may shift standard practice, but bromocriptine remains a first-line agent in many centers due to more extensive safety data.
Limitations in available data include lack of large randomized trials during pregnancy due to ethical concerns and reliance on observational registry studies and meta-analyses. Close clinical vigilance and prompt intervention are paramount to mitigate adverse outcomes.
The complex interplay between prolactinomas, pregnancy-induced pituitary changes, and dopaminergic treatments underscores the necessity of personalized risk-benefit assessment and adaptive management strategies.
Conclusion
Prolactinomas pose unique challenges throughout the reproductive journey, requiring astute clinical management to optimize fertility while safeguarding maternal and fetal health. Dopamine agonist therapy effectively restores fertility preconception and can be safely reintroduced during pregnancy if tumor enlargement occurs. Both bromocriptine and cabergoline demonstrate robust safety profiles, with cabergoline increasingly preferred. Pituitary apoplexy, while rare, mandates immediate multidisciplinary evaluation. Breastfeeding is encouraged unless tumor management necessitates treatment resumption.
Overall, a tailored and multidisciplinary approach—anchored in evidence-based medicine and close monitoring—enables favorable pregnancy and lactation outcomes for women with prolactinomas.
References
1. Karaca Z, Kelestimur F. Approach to the pregnant patient with prolactinoma. J Clin Endocrinol Metab. 2026;111(10):42828437.
2. Molitch ME. Management of medically resistant prolactinoma. J Neurooncol. 2009;94(1):1-6.
3. Verhelst J, Abs R, Maiter D, et al. Cabergoline in the treatment of hyperprolactinemia: a study in 455 patients. J Clin Endocrinol Metab. 1999;84(5):1657-1662.
4. Colao A, Di Sarno A, Landi ML, et al. Dopamine agonist therapy for prolactinomas in pregnancy. Ann Endocrinol (Paris). 2002;63(5):401-405.
5. Endocrine Society Clinical Practice Guideline. Diagnosis and treatment of hyperprolactinemia. J Clin Endocrinol Metab. 2011;96(2):273-288.
6. Molitch ME. Prolactin and pregnancy in patients with prolactinomas. Endocrinol Metab Clin North Am. 1999;28(1):99-119.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.