Medicare Advantage and Type 2 Diabetes Outcomes: Evaluating Clinical and Social Impacts Amid Rising Costs
Highlights
- Medicare Advantage (MA) incurs 22% higher costs than Original Medicare (OM) but does not confer superior improvements in type 2 diabetes (T2D) clinical outcomes.
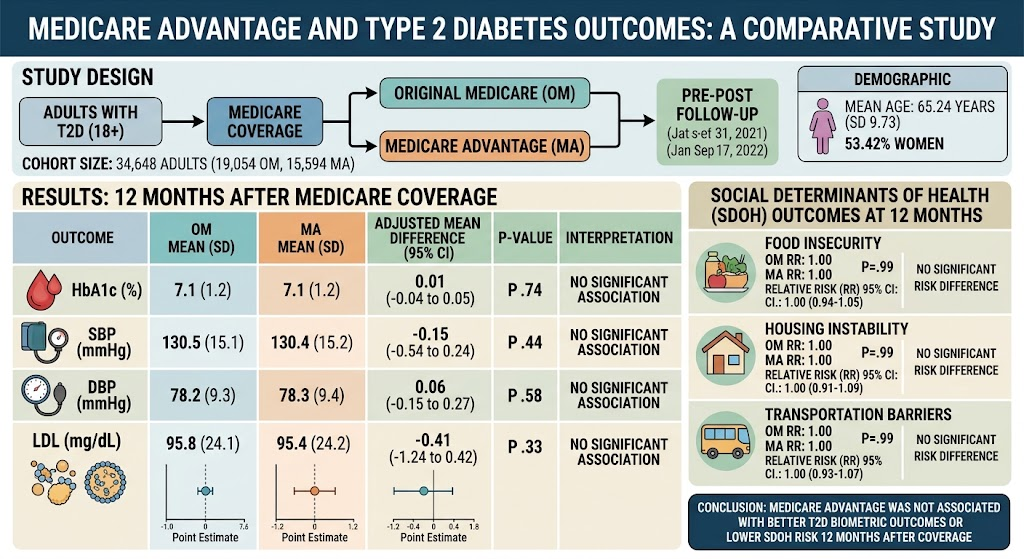
- Longitudinal cohort study using rigorous target trial emulation reveals no significant differences in HbA1c, blood pressure, LDL cholesterol, or social determinants such as food insecurity between MA and OM beneficiaries.
- Disparities in advanced diabetes pharmacotherapy utilization, including SGLT2 inhibitors and GLP-1 receptor agonists, persist across insurance types, socioeconomic status, and demographic groups.
- Educational interventions targeting treatment intensification in managed care have shown limited efficacy in improving glycemic control or medication initiation, highlighting challenges in overcoming clinical inertia.
Background
Type 2 diabetes mellitus (T2D) represents a major public health burden, with high prevalence in the Medicare population due to age-related risk and comorbidities. Optimal diabetes management reduces the risk of microvascular and macrovascular complications. Medicare Advantage (MA), a managed care alternative to Original Medicare (OM), incurs substantially higher expenditures—approximately 22% more per beneficiary, translating to $83 billion in excess public costs annually in the US. Proponents argue that MA’s supplemental benefits, such as out-of-pocket spending caps and services addressing social determinants of health (SDOH), could improve clinical outcomes in T2D compared with OM.
However, whether these theoretical advantages translate into measurable improvements in diabetes control or reduction in health-related social needs remains understudied. Given the immense financial implications, it is critical to evaluate comparative effectiveness of MA versus OM for T2D outcomes and associated social determinants.
Key Content
1. Longitudinal Study Comparing MA and OM Outcomes in T2D
The pivotal study by Berkowitz et al. (2026) utilized target trial emulation principles to analyze 34,648 adults with T2D enrolled in community-based health centers across 44 US states from January 2021 to June 2024. Participants transitioned to either OM (n=19,054) or MA (n=15,594) Medicare coverage and were followed longitudinally before and after Medicare enrollment.
Primary outcomes included hemoglobin A1c (HbA1c), systolic and diastolic blood pressures (SBP, DBP), and low-density lipoprotein (LDL) cholesterol measured at 6, 12, 18, and 24 months post-Medicare enrollment. Secondary outcomes incorporated assessments of food insecurity, housing instability, and transportation barriers—key social determinants impacting diabetes care.
Adjustments for confounders and selection bias involved targeted minimum loss estimation incorporating demographic variables, comorbidities, pre-Medicare insurance status, Medicaid coverage, and pre-Medicare clinical values.
Results demonstrated no statistically significant differences between MA and OM in the mean HbA1c change at 12 months (mean difference 0.01; 95% CI, –0.04 to 0.05; P = .74), SBP, DBP, or LDL cholesterol. Similarly, risks of food insecurity, housing instability, and transportation barriers remained comparable. Findings persisted consistently across all time points.
2. Influence of Insurance and Social Determinants on Advanced Diabetes Pharmacotherapy
Khatri et al. (2026) conducted a systematic review and meta-analysis including >14.6 million patients to investigate social determinants affecting utilization of SGLT2 inhibitors (SGLT2i) and GLP-1 receptor agonists (GLP-1RA)—therapies with proven cardiovascular and metabolic benefit in T2D.
Findings highlighted that patients with Medicare, including MA beneficiaries, had substantially lower odds of utilizing these agents (adjusted odds ratio [aOR] 0.68 for Medicare and 0.41 for MA) compared to those with private insurance. Additional barriers included low socioeconomic status (aOR 0.73), Medicaid coverage, lower educational attainment, rural residence, and residing in high-deprivation neighborhoods. Racial and ethnic disparities were also evident, with Black, Hispanic, and Asian patients showing reduced utilization.
These disparities suggest that access to newer and effective diabetes pharmacotherapies is limited within Medicare populations, potentially influencing clinical outcomes adversely regardless of coverage type.
3. Educational Interventions to Improve Glycemic Control in Managed Care
In attempts to overcome clinical inertia—the failure to intensify treatment appropriately—educational programs such as the “Act on Threes” intervention were deployed among Medicare Advantage beneficiaries (Reynolds et al., 2016).
This randomized controlled trial targeted timely HbA1c testing, treatment intensification, and insulin initiation according to ADA guidelines. Despite increased awareness, the intervention did not significantly improve the frequency of HbA1c testing or insulin initiation compared with standard care, nor did it improve glycemic levels. The majority of improvement was attributed to temporal trends unrelated to the intervention.
This underscores the complexity of diabetes management and the limited impact of isolated educational efforts without systemic change.
Expert Commentary
The lack of improvement in T2D outcomes and social needs among Medicare Advantage enrollees versus those in Original Medicare, as demonstrated by Berkowitz et al., calls into question the value proposition of the higher spending on MA. Although MA plans offer supplemental benefits and theoretically address barriers such as food insecurity and transportation, this longitudinal, rigorously adjusted analysis did not reveal actual clinical or social benefit.
Furthermore, the meta-analysis showing lower uptake of advanced glucose-lowering therapies in MA patients highlights possible systemic access issues within these plans, including formulary restrictions or higher out-of-pocket costs. This diminished access to efficacious medications may attenuate any potential clinical advantage of MA.
The failure of targeted educational interventions like “Act on Threes” to significantly improve treatment intensification reflects persistent clinical inertia and suggests that broader organizational and policy-level reforms may be necessary to optimize diabetes care within managed care settings.
The findings also align with the broader literature indicating that social determinants profoundly influence health outcomes and pharmacotherapy utilization beyond insurance coverage alone. Successful interventions may require integration of clinical care with social services and policy adjustments to enhance access, adherence, and address systemic inequalities.
Conclusion
Despite the higher costs associated with Medicare Advantage, current evidence does not support its superiority over Original Medicare in improving type 2 diabetes control or mitigating health-related social needs. Persistent disparities in access to advanced diabetes therapies and limited efficacy of educational interventions emphasize the need for comprehensive strategies that integrate social determinants and optimize pharmacologic management.
Future research should focus on refining supplemental benefits, removing barriers to effective diabetes medications, and developing more robust multi-level interventions that bridge clinical care with social support frameworks. Policymakers should critically evaluate the cost-effectiveness of Medicare Advantage programs relative to health outcomes and equity in diabetes care.
References
- Berkowitz SA, LaPoint M, Kuhn ML, Basu S, Hudgens MG, Gold R, Park S. `. JAMA Internal Medicine. 2026 Aug 10; PMCID: PMC13421548. doi:10.1001/jamainternmed.2026.42573997. Available at: https://pubmed.ncbi.nlm.nih.gov/42573997/
- Khatri U, et al. Association of Social Determinants of Health with Utilization of SGLT2 Inhibitors and GLP1 Receptor Agonists: A Systematic Review and Meta-Analysis. J Gen Intern Med. 2026 Aug;41(10):2859-2872. doi:10.1007/s11606-026-10178-z. PMID: 41838266. Available at: https://pubmed.ncbi.nlm.nih.gov/41838266/
- Reynolds R, Davis T, Kamble P, Uribe C, Bieszk N, Wei C. “Act on Threes” Paradigm for Treatment Intensification of Type 2 Diabetes in Managed Care: Results of a Randomized Controlled Study with an Educational Intervention Targeting Improved Glycemic Control. J Manag Care Spec Pharm. 2016 Sep;22(9):1028-38. doi:10.18553/jmcp.2016.22.9.1028. PMID: 27579824. Available at: https://pubmed.ncbi.nlm.nih.gov/27579824/
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.