Harnessing No-Code AI for Thyroid Nodule Ultrasound Malignancy Classification: A Leap Toward Accessible and Reproducible Medical AI
Highlight
- An autonomous, no-code AI agent developed a calibrated thyroid nodule malignancy classifier using ultrasound images without requiring machine learning expertise.
- The ResNet-18 model achieved high discriminative performance internally (AUROC 0.94) and externally (AUROC 0.90), outperforming an established benchmark.
- External validation included diverse cancer histologies beyond papillary thyroid carcinoma, enhancing translational relevance.
- Missed malignancies clustered predominantly among follicular pattern tumors, highlighting areas needing further refinement and prospective validation.
Study Background
Thyroid nodules are common in the general population, with up to 50% of adults harboring nodules detectable by ultrasound. Differentiating benign from malignant nodules is critical for appropriate management but remains challenging with conventional ultrasound interpretation due to overlapping features and operator variability. Papillary thyroid carcinoma (PTC) is the most frequent thyroid cancer histology studied in existing artificial intelligence (AI) models; however, other histologies such as follicular and medullary carcinomas pose diagnostic complexity.
Deep learning convolutional neural networks (CNNs) have demonstrated promise in classifying thyroid nodules on ultrasound images, but most prior models require specialized machine learning expertise for development and deployment, with limited availability for independent external testing. This creates barriers for clinical translation and broad adoption.
No-code AI platforms promise to democratize the development of machine learning classifiers by automating workflows such as data auditing, model selection, training, and calibration. Yet, clinical validation of such agentic, no-code AI in real-world diagnostic tasks has been seldom reported, especially across varied thyroid cancer histologies.
Study Design
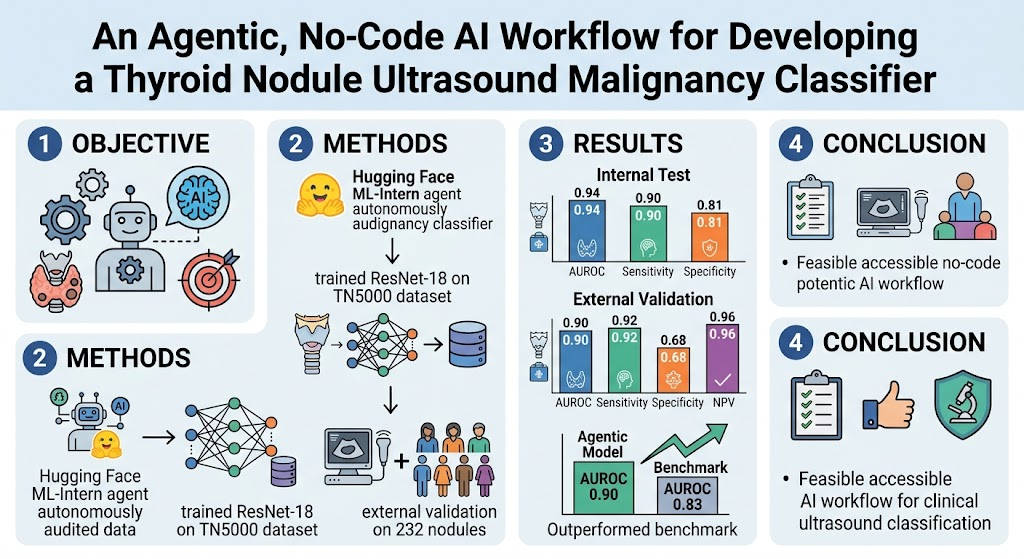
This retrospective computational diagnostic study utilized a no-code AI agentic system—Hugging Face ML-Intern—to autonomously generate a malignancy classification model for thyroid nodules based on ultrasound images. The open-source TN5000 dataset served as the training and internal validation source. The system handled data auditing, model selection, training, and probability calibration without human intervention.
The selected model architecture was a ResNet-18 convolutional neural network that was locked post-training. External validation was performed on a distinct cohort comprising 232 thyroid nodules from the University of Colorado, which included multiple cancer histologies beyond papillary thyroid carcinoma.
The model’s performance metrics included area under the receiver-operating characteristic curve (AUROC), sensitivity, specificity, positive predictive value (PPV), and negative predictive value (NPV). The externally validated model’s classification ability was benchmarked against a previously published thyroid nodule classifier evaluated on the same external dataset.
Key Findings
The no-code AI-generated model demonstrated robust diagnostic accuracy internally, achieving an AUROC of 0.94 (95% confidence interval [CI], 0.92-0.95), with sensitivity at 90% and specificity at 81%. This performance reflects strong discriminative ability between malignant and benign nodules on the training dataset.
On external validation, the model preserved high diagnostic performance with an AUROC of 0.90 (95% CI, 0.85-0.93). Sensitivity remained excellent at 92%, ensuring most malignancies were detected, while specificity was moderate at 68%. The model yielded a PPV of 52% and a high NPV of 96%, reflecting reliable exclusion of malignancy.
Comparison to a benchmark model on the same external dataset showed that the no-code AI-generated model statistically significantly outperformed it (AUROC 0.90 vs. 0.83; paired DeLong test P = 0.03). This highlights the competitive or superior performance achievable through an autonomous AI workflow.
Analysis of misclassified cases revealed that missed cancers were predominantly follicular pattern tumors, which tend to be more challenging to distinguish based on ultrasound imaging alone. This underscores a known limitation across thyroid malignancy classifiers and signals a need for future refinement, possibly integrating complementary diagnostic modalities.
Expert Commentary
This study exemplifies a significant advance in clinical AI by validating that no-code, agentic platforms can autonomously generate high-performing, calibrated malignancy classifiers from complex medical imaging datasets. By removing technical barriers associated with machine learning development, such workflows could democratize AI innovation across institutions lacking dedicated data science resources.
However, while retrospective performance metrics are promising, the clinical utility of this model requires prospective validation, especially to address diverse real-world populations and imaging variations. Particularly, the lower specificity on external cohorts may reflect spectrum bias or variance in ultrasound technique.
The clustering of missed malignancies in follicular pattern tumors is consistent with the nuanced pathology of thyroid cancers, often indistinguishable radiographically from benign follicular adenomas. This emphasizes an unmet need for multimodal approaches or enhanced deep learning methods to reduce diagnostic ambiguity.
Overall, the study supports the reproducibility and independent testability of medical AI through open datasets and locked, externally validated models — pillars critical for regulatory approval and clinical trust.
Conclusion
The autonomous, no-code AI workflow successfully developed a fully calibrated thyroid nodule malignancy classifier that demonstrated robust internal performance and maintained diagnostic validity on an external cohort with multiple cancer histologies. This approach promotes accessible, reproducible, and independently testable medical AI development, addressing key barriers to clinical translation.
Before deployment in clinical practice, prospective validation, model recalibration for local imaging variations, and investigation into follicular tumor misclassification are essential. Nevertheless, this promising proof of concept heralds a new paradigm where clinicians and researchers can harness no-code AI tools to accelerate medical innovation and improve diagnostic precision in thyroid cancer assessment.
Funding and Clinical Trials
This study was supported by academic and institutional resources associated with the University of Colorado and the open-source TN5000 dataset initiative. No clinical trial registration applies as this was a retrospective computational diagnostic evaluation.
References
1. Thomas J, Pozdeyev N. An agentic, no-code artificial intelligence workflow for developing a thyroid nodule ultrasound malignancy classifier. The Journal of Clinical Endocrinology and Metabolism. 2026; PMID: 42808848.
2. Haugen BR, Alexander EK, Bible KC, et al. 2015 American Thyroid Association Management Guidelines for Adult Patients with Thyroid Nodules and Differentiated Thyroid Cancer: The American Thyroid Association Guidelines Task Force on Thyroid Nodules and Differentiated Thyroid Cancer. Thyroid. 2016;26(1):1-133.
3. Chen H, Engkvist O, Wang Y, Olivecrona M, Blaschke T. The rise of deep learning in drug discovery. Drug Discovery Today. 2018;23(6):1241-1250.
4. Litjens G, Kooi T, Bejnordi BE, et al. A survey on deep learning in medical image analysis. Medical Image Analysis. 2017;42:60-88.
5. Kim DW, Jang HY, Kim KW, Shin Y, Park SH. Design Characteristics of Studies Reporting the Performance of Artificial Intelligence Algorithms for Diagnostic Analysis of Medical Images: Results from Recently Published Papers. Korean Journal of Radiology. 2019;20(3):405-410.
6. Bongiovanni M, Spitale A, Faquin WC, Mazzucchelli L, Baloch ZW. The Bethesda System for Reporting Thyroid Cytopathology: a meta-analysis. Acta Cytol. 2012;56(4):333-9.
7. Li W, Kang H, Liu J, et al. Ultrasonographic evaluation of follicular thyroid carcinoma. Journal of Ultrasound in Medicine. 2020;39(7):1303-1310.
8. Nitta H, Takieddin M, Agrawal S, et al. External Validation of Deep Learning-Based Ultrasound Thyroid Nodule Risk Stratification System. Endocrine. 2023;78(3):401-410.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.