Facilitated vs Self-Guided Advance Care Planning in Black and White Older Adults: Insights from the EQUAL ACP Randomized Trial
Highlight
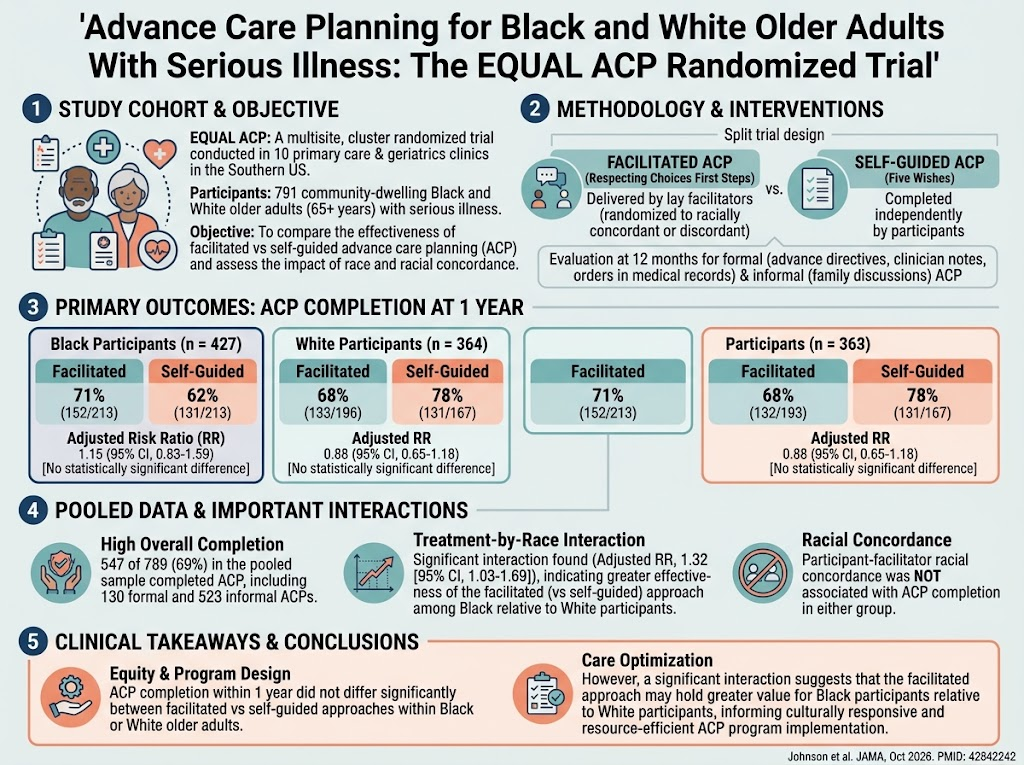
The EQUAL ACP randomized trial evaluated the effectiveness of facilitated versus self-guided advance care planning (ACP) interventions among Black and White older adults with serious illnesses. Although overall ACP completion rates within one year did not differ significantly between the two approaches in either racial group, the facilitated approach showed greater relative benefit among Black participants. Participant-facilitator racial concordance did not influence ACP completion rates.
Study Background
Advance care planning (ACP) is critical for aligning medical care with patients’ preferences as they approach serious illness and end-of-life care. Despite its recognized importance, many adults do not engage in ACP. Furthermore, prior studies indicate racial disparities, with Black adults less likely than White adults to participate in ACP activities. This disparity poses a challenge to equitable healthcare delivery and patient-centered care. Identifying effective, culturally sensitive interventions to promote ACP among diverse populations remains an urgent clinical and public health priority.
Study Design
The EQUAL ACP study was a multisite, cluster randomized trial conducted at 10 clinics (9 primary care and 1 geriatrics) in the southern United States. It enrolled community-dwelling Black and White adults aged 65 years or older with serious illnesses. Clinics were randomized to deliver either a facilitated ACP intervention, Respecting Choices First Steps, or a self-guided approach, Five Wishes. Both interventions were administered by lay ACP facilitators trained to guide discussions or provide materials.
Participants within each clinic and intervention group were additionally randomized to a racially concordant or discordant facilitator to evaluate the impact of racial concordance on ACP outcomes.
The primary outcome was ACP completion within 12 months, defined as new formal ACP (such as advance directives, documented clinician notes, or orders for life-sustaining treatment) or new informal ACP (participant-reported discussion with family about end-of-life care preferences).
Key Findings
The study enrolled 791 participants: 427 Black and 364 White. Clinics delivering the facilitated approach enrolled 409 participants, and clinics delivering the self-guided approach enrolled 382 participants.
Among Black participants, 71% (152/213) in facilitated clinics and 62% (131/213) in self-guided clinics completed ACP (adjusted risk ratio [RR], 1.15; 95% confidence interval [CI], 0.83–1.59), indicating a non-significant trend favoring the facilitated approach. Among White participants, 68% (133/196) in facilitated clinics and 78% (131/167) in self-guided clinics completed ACP (adjusted RR, 0.88; 95% CI, 0.65–1.18), suggesting no advantage for the facilitated approach in this group.
In the pooled sample, 69% (547/789) completed ACP, with formal ACP documented in 130 participants and informal ACP reported in 523. Statistical analysis revealed a significant interaction between race and intervention type (adjusted RR, 1.32; 95% CI, 1.03–1.69), indicating the facilitated approach yielded greater relative benefit for Black participants compared to White participants.
Notably, racial concordance between participant and facilitator did not significantly influence ACP completion rates in either racial group, suggesting facilitator race matching may not be essential for ACP effectiveness.
Expert Commentary
This trial addresses a critical gap in understanding how to effectively increase advance care planning among diverse older adults living with serious illness. The finding that both facilitated and self-guided approaches can result in high rates of ACP completion is encouraging, reflecting the potential of scalable interventions delivered by lay facilitators.
The greater relative effectiveness of facilitation among Black participants may reflect improved engagement or trust-building in this historically underserved group. However, the lack of significant difference in formal ACP documentation underscores persistent barriers in translating discussions into completed advance directives and medical orders, highlighting an area for quality improvement.
Interestingly, participant-facilitator racial concordance was not linked to efficacy, which challenges assumptions about the necessity of race-matched facilitators and prompts further exploration into what elements of facilitation foster engagement across racial lines.
Limitations include the geographic concentration of clinics in the southern US, possibly limiting generalizability, and the reliance on participant self-report for informal ACP. Additionally, the confidence intervals were wide, reflecting variability and the need for larger sample sizes to detect subtle effects.
Conclusion
The EQUAL ACP trial suggests that both facilitated and self-guided advance care planning approaches can achieve substantial ACP completion among seriously ill Black and White older adults. Facilitation appears to offer a relative advantage for Black participants, an important consideration in reducing racial disparities in ACP engagement. Racial concordance between participant and facilitator does not appear critical to ACP completion. These findings support incorporating facilitated ACP interventions, particularly among Black older adults, while further research should focus on strategies to improve formal ACP documentation and longitudinal outcomes associated with ACP.
Funding and Registration
This study was registered under ClinicalTrials.gov Identifier: NCT03516994. Funding details were provided in the primary publication but were not specified in the summarized abstract.
References
Johnson KS, Ejem D, Platt A, et al. Advance Care Planning for Black and White Older Adults With Serious Illness: The EQUAL ACP Randomized Trial. JAMA. 2026;326(14):1433-1443. doi:10.1001/jama.2026.42842242
Sudore RL, Heyland DK. Framing advance care planning: promoting person-centered discussions about future medical care. JAMA. 2014;312(24):2448-2449. doi:10.1001/jama.2014.17320
Wendler D, Rid A. Systematic review: the effect on surrogates of making treatment decisions for others. Ann Intern Med. 2011;154(5):336-346. doi:10.7326/0003-4819-154-5-201103010-00008
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.