Enhanced Diagnosis of Primary Aldosteronism: Comparing LC-MS/MS and Immunoassay for Urinary Aldosterone Measurement
Highlight
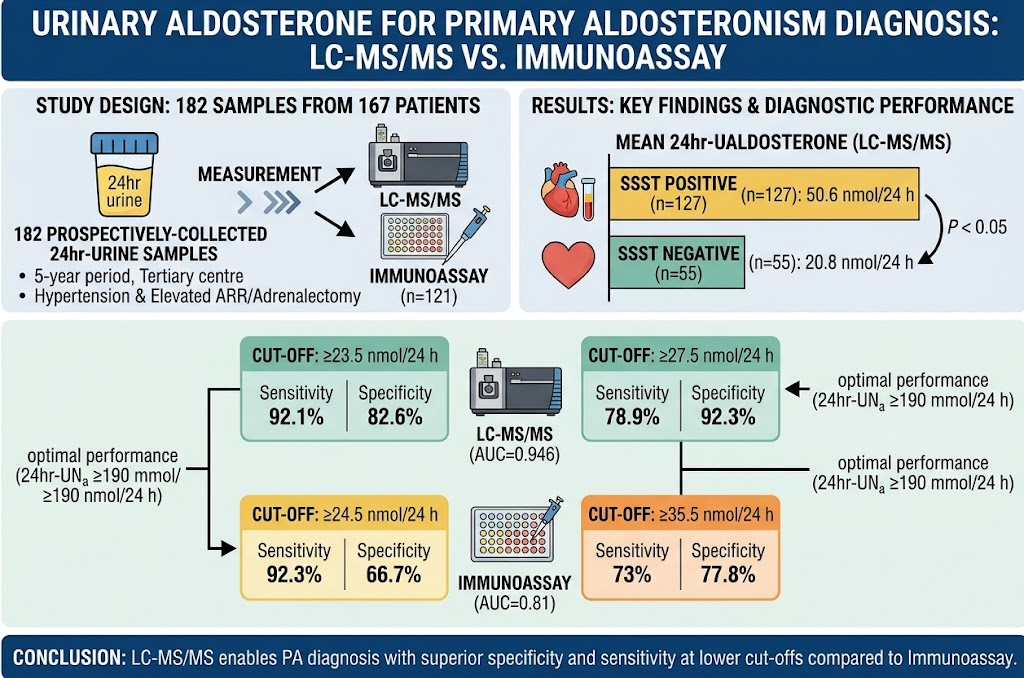
- Urinary aldosterone measured by LC-MS/MS shows higher diagnostic accuracy for primary aldosteronism (PA) compared to immunoassay.
- Optimal diagnostic performance occurs with 24-hour urinary sodium (24hr-UNa) levels ≥190 mmol/24 h.
- LC-MS/MS enables lower diagnostic cutoff thresholds with superior sensitivity (92.1%) and specificity (82.6%) for PA detection.
- Immunoassay methods demonstrate inferior specificity, limiting their clinical utility for PA diagnosis.
Study Background
Primary aldosteronism is a common and potentially curable cause of secondary hypertension characterized by overproduction of aldosterone, leading to sodium retention, potassium excretion, and increased cardiovascular risk. Accurate biochemical diagnosis of PA is crucial for appropriate treatment allocation, including targeted surgical intervention in unilateral disease. Traditionally, 24-hour urinary aldosterone (24hr-UAldo) has been measured with immunoassays; however, these assays often suffer from cross-reactivity and lower analytical specificity. Liquid chromatography coupled with tandem mass spectrometry (LC-MS/MS) offers enhanced analytical specificity and sensitivity, yet its diagnostic performance in PA detection from 24-hour urine collections remains under-characterized, especially considering the influence of sodium intake as reflected by 24hr-UNa values. This study addresses this gap by prospectively comparing LC-MS/MS versus immunoassay-based urinary aldosterone measurements within a clinically well-defined hypertensive cohort.
Study Design
The investigation was a prospective cohort study conducted over five years at a tertiary referral center specializing in hypertension and adrenal disorders. A total of 182 24-hour urine samples were collected from 167 hypertensive patients with elevated plasma aldosterone-renin ratio (ARR) or patients undergoing adrenalectomy for confirmed unilateral PA. Participants were off interfering medications and maintained an unrestricted sodium diet. The clinical reference test was the seated saline suppression test (SSST), with 127 patients positive and 55 patients negative for PA.
Urinary aldosterone was analyzed using LC-MS/MS in all 182 samples, while 121 stored samples underwent immunoassay testing concurrently. Additionally, 24-hour urinary sodium was measured in all samples to evaluate the impact of sodium excretion on diagnostic accuracy. Receiver operating characteristic (ROC) analyses assessed performance metrics of 24hr-UAldo measured by both methods, stratified by urinary sodium levels, using SSST results as the criterion standard.
Key Findings
The study found significantly elevated 24hr-UAldo-LCMS concentrations in patients with positive SSST compared to negatives (50.6 ± 35.7 nmol/24 h vs. 20.8 ± 13.9 nmol/24 h; P < 0.05). Using a diagnostic cutoff of ≥23.5 nmol/24 h, LC-MS/MS yielded a sensitivity of 92.1% and specificity of 82.6%, with an area under the ROC curve (AUC) of 0.946, indicating excellent discriminative capacity.
In patients with 24hr-UNa ≥190 mmol/24 h, the optimal sodium threshold, a higher cutoff of ≥27.5 nmol/24 h improved specificity to 92.3%, albeit with slightly reduced sensitivity of 78.9%. This emphasizes that adequate sodium intake during testing enhances diagnostic accuracy using LC-MS/MS.
In contrast, immunoassay-based 24hr-UAldo displayed lower specificity. At a cutoff of ≥24.5 nmol/24 h, sensitivity was comparable at 92.3%, but specificity dropped to 66.7% with an AUC of 0.81. At a higher cutoff of ≥35.5 nmol/24 h and 24hr-UNa ≥190 mmol/24 h, specificity improved to 77.8% but sensitivity declined to 73.0%, thereby limiting clinical reliability.
The data collectively indicate that LC-MS/MS measurement of urinary aldosterone provides superior diagnostic performance relative to immunoassay, particularly when urinary sodium is sufficiently high, reducing false positives and supporting confident PA diagnosis.
Expert Commentary
The findings align with growing evidence endorsing LC-MS/MS as the gold standard for steroid hormone quantification, overcoming the cross-reactivity and lower specificity inherent to immunoassays. Sodium intake, reflected by 24hr-UNa, is a critical modifier of aldosterone excretion and influences diagnostic accuracy; hence, controlling or at least accounting for sodium status is essential when interpreting 24hr-UAldo results.
While SSST remains a valuable functional confirmation test for PA, the use of 24hr-UAldo-LCMS as a noninvasive, easily obtainable biomarker may streamline screening and reduce reliance on more cumbersome confirmatory tests. However, the requirement for specialized equipment and expertise for LC-MS/MS analysis limits widespread availability currently.
Limitations include the single-center design and the subset analyzed by immunoassay on stored samples, which may introduce degradation or bias. Future multicenter validation and standardization of cutoff values incorporating sodium adjustment are warranted.
Conclusion
This study substantiates 24-hour urinary aldosterone measurement by LC-MS/MS as a highly sensitive and specific biomarker for diagnosing primary aldosteronism, outperforming traditional immunoassays, particularly when urinary sodium is ≥190 mmol/24 h. Incorporating LC-MS/MS in clinical protocols could improve diagnostic accuracy, enabling timely and precise management of PA. Future research should focus on establishing standardized diagnostic thresholds, accessibility optimization, and integration into clinical pathways to better mitigate cardiovascular risk in hypertensive populations.
Funding and ClinicalTrials.gov
The study was conducted without stated external funding. No ClinicalTrials.gov registration was referenced.
References
1. Mulatero P, Monticone S, Bertello C, et al. Diagnosis and treatment of primary aldosteronism. Nat Rev Endocrinol. 2023;19(1):18-29.
2. Rossi GP, Bernini G, Caliumi C, et al. A prospective study of the prevalence of primary aldosteronism in 1,125 hypertensive patients. J Am Coll Cardiol. 2006 Mar 7;48(11):2293-300.
3. Williams TA, Monticone S, Schack VR, et al. Genomic, transcriptomic, and immunohistochemical characterization of aldosterone-producing adenomas. Hypertension. 2019 Feb;73(2):387-397.
4. Stowasser M, Gordon RD, Tunny TJ, et al. Mineralocorticoid hypertension: plasma aldosterone and plasma renin activity measurement. Clinical diagnosis and differentiation of adrenal adenoma from idiopathic hyperplasia. Hypertension. 1989 Mar;13(3):422-9.
5. Eisenhofer G, Stowasser M, Defronzo RA, et al. Biochemical Diagnosis of Endocrine Hypertension Using Urinary Metabolomics and Mass Spectrometry. Horm Metab Res. 2021 Jun;53(7):409-427.
6.Thuzar M, Matthews A, Je D, He J, Stoner S, Ward G, Ng E, Yang J, Cowley D, Li B, McWhinney BC, Ungerer JP, Stowasser M. Urinary Aldosterone Analysed by LC-MS/MS vs Immunoassay for Diagnosis of Primary Aldosteronism. J Clin Endocrinol Metab. 2026 Aug 26:dgag349. doi: 10.1210/clinem/dgag349. Epub ahead of print. PMID: 42644281.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.