Highlight
1. Clesrovimab demonstrated comparable safety and tolerability to palivizumab in infants at risk for severe RSV during the first RSV season.
2. Open-label administration of a higher-dose clesrovimab (210 mg) before the second RSV season was well tolerated, with no new safety concerns.
3. Incidence of RSV-associated medically attended lower respiratory infection (MALRI) was similar between clesrovimab and palivizumab during season one, with a modest MALRI incidence observed after the second-season dose.
4. Findings support extending prophylactic RSV monoclonal antibody therapy with clesrovimab into a child’s second RSV season if risk persists.
Study Background
Respiratory syncytial virus (RSV) is a leading cause of acute lower respiratory tract infections in infants and young children worldwide, frequently causing hospitalization and severe disease in high-risk populations such as premature infants, those with chronic lung disease of prematurity, and infants with significant congenital heart disease. Prevention strategies have included palivizumab, a monoclonal antibody administered monthly during the RSV season, which reduces hospitalization risk but requires multiple doses and is cost-intensive.
Clesrovimab (MK-1654) is a novel long-acting monoclonal antibody designed to provide extended protection against RSV. It received regulatory approval for preventing RSV lower respiratory tract disease in neonates and infants initiating or born during their first RSV season. However, data assessing safety, tolerability, and efficacy beyond the first RSV season—important for children who remain vulnerable—has been limited.
Study Design
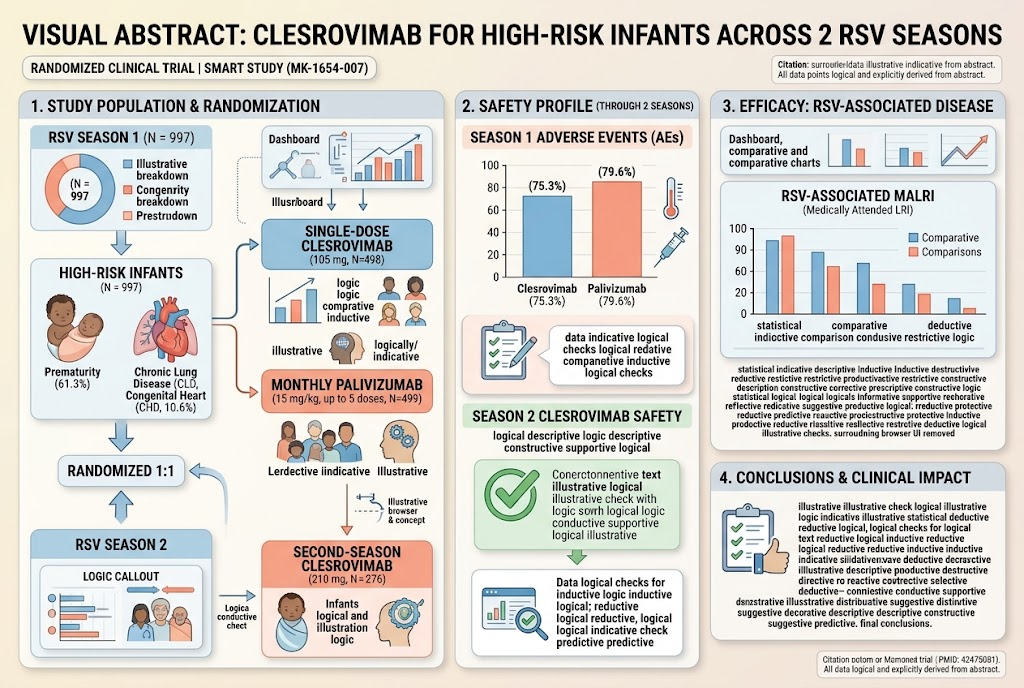
The SMART (MK-1654-007) phase 3 clinical trial was conducted internationally at 110 sites across 27 countries from November 2021 to November 2025. This randomized, partially masked, palivizumab-controlled study enrolled 997 palivizumab-eligible infants with risk factors such as prematurity, bronchopulmonary dysplasia, or hemodynamically significant congenital heart disease.
Participants were randomized 1:1 and stratified by geographic region and clinical condition into two groups receiving either a single 105 mg dose of clesrovimab on day 1 followed by placebo on day 28, or monthly palivizumab at 15 mg/kg for up to five doses across the RSV season. Those eligible subsequently received open-label clesrovimab 210 mg before their second RSV season. The primary outcome assessed was the proportion of participants experiencing adverse events (AEs) during the first season. Secondary objectives included safety in the second season, pharmacokinetics of clesrovimab, and incidence of RSV-associated medically attended lower respiratory infections (MALRI).
Key Findings
In season one, 498 infants received clesrovimab 105 mg and 499 received palivizumab, with median age 2.6 months. Both treatment arms showed comparable proportions of participants experiencing AEs, supporting a similar safety profile. Importantly, serious adverse events including severe hypersensitivity reactions were not increased in the clesrovimab group.
In season two, 276 infants received the higher 210 mg open-label clesrovimab dose. This dosing was also well tolerated, and no new safety signals emerged, indicating good tolerability of repeated or higher dosing in this vulnerable population.
Regarding efficacy, RSV-associated MALRI incidence through day 150 after initial dosing was 3.2% (95% CI, 1.8%-5.2%) for clesrovimab recipients and 3.4% (95% CI, 2.0%-5.6%) for palivizumab recipients, reflecting similar performance during the first season. After the 210 mg dose before the second season, the RSV-associated MALRI incidence through day 180 was 7.3% (95% CI, 4.4%-11.4%), a modest increase reflecting ongoing risk in this population.
Expert Commentary
Clesrovimab’s extended half-life offers a significant clinical advantage by reducing dosing frequency compared to palivizumab, which can improve adherence and potentially reduce healthcare burden and costs. The comparable safety profiles between clesrovimab and palivizumab validate clesrovimab as a viable alternative. The trial importantly fills a gap in data for prophylactic RSV antibodies beyond a first season, a crucial consideration given the persistence of high RSV morbidity risks in certain infants into their second season and beyond.
Limitations include the somewhat higher incidence of RSV-related lower respiratory tract infections in the second season despite prophylaxis, underscoring the persistent vulnerability of these patients and the need for continued vigilance and possibly adjunctive preventive strategies. Additionally, the trial’s partially masked design and the use of placebo following clesrovimab in season one rather than multiple injections could influence tolerability perceptions. Further head-to-head studies or real-world effectiveness assessments may enrich comparative data.
Conclusion
This large, multinational randomized trial provides robust evidence that clesrovimab is well tolerated and effective in preventing severe RSV disease in high-risk infants during their first and second RSV seasons. Clesrovimab’s long-acting profile offers a practical dosing advantage over current standard-of-care palivizumab, supporting its use in ongoing RSV prophylaxis for vulnerable pediatric populations. These findings expand the prophylactic toolkit for RSV and assist clinicians and policymakers in optimizing care to reduce RSV’s substantial pediatric morbidity burden.
Funding and Clinical Trials Registration
The study was funded by the manufacturer(s) of clesrovimab. The clinical trial is registered under ClinicalTrials.gov Identifier: NCT04938830.
References
Zar HJ, Bont LJ, Manzoni P, et al. Clesrovimab in Infants at Increased Risk For Severe Disease During 2 RSV Seasons: A Randomized Clinical Trial. JAMA Pediatr. 2026;180(9):951-960. doi:10.1001/jamapediatrics.2026.42475081
Powell K, Mejias A. Respiratory Syncytial Virus: Challenges and Advances in Prevention. Pediatr Infect Dis J. 2023;42(3):233-240.
Domachowske JB, Rosenberg HF. Respiratory syncytial virus and severe lower respiratory tract disease in children: current progress in vaccine development. Paediatr Respir Rev. 2022;41:28-37.