Bridging the Diagnostic and Treatment Divide in Laboratory-Confirmed Diabetes: Insights from a National Cohort Study
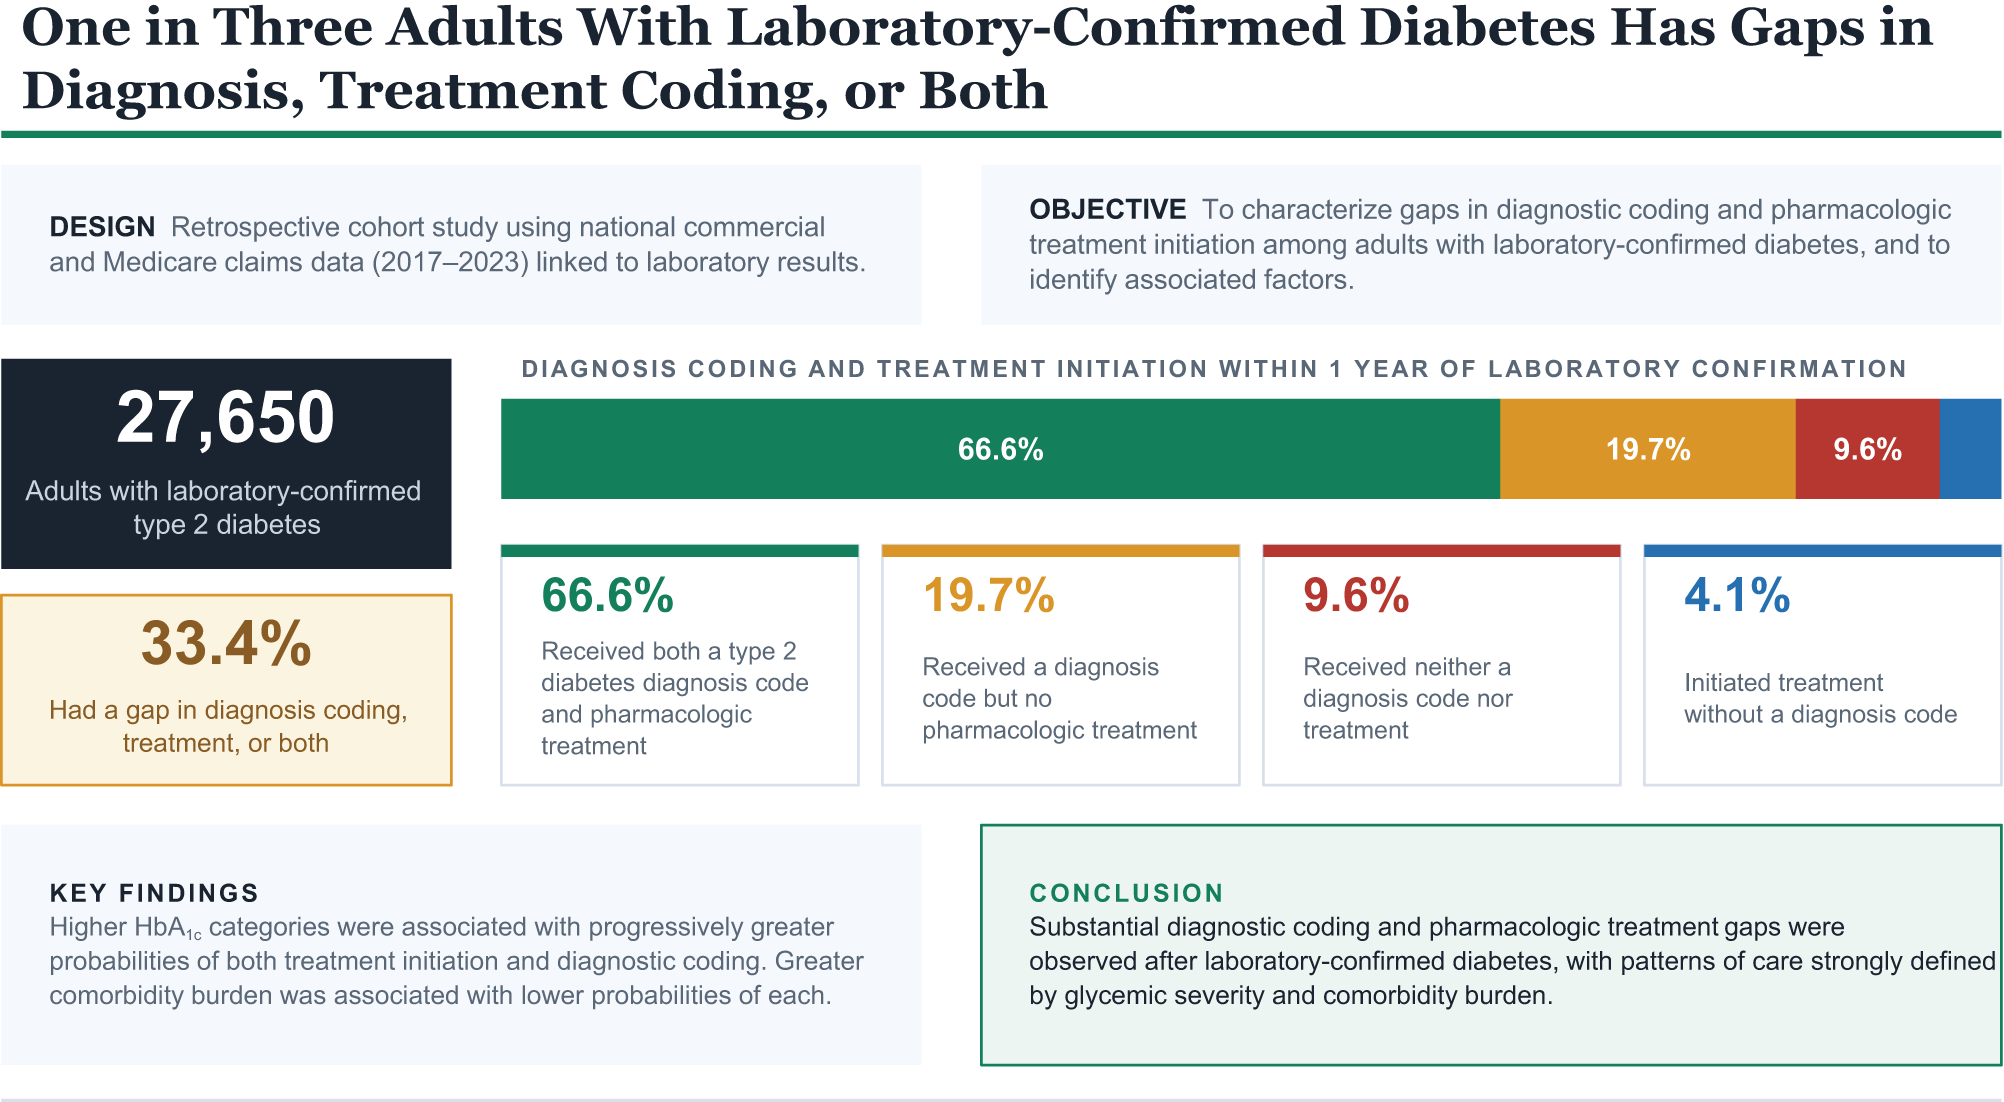
Highlight
• One-third of adults with laboratory-confirmed diabetes lacked either diagnostic coding, pharmacologic treatment, or both within one year of detection.
• Higher HbA1c levels correlated with greater likelihood of both diagnostic coding and treatment initiation.
• Patients with greater comorbidity burden were less likely to receive formal diabetes diagnosis coding or pharmacologic therapy.
• This national study underscores missed clinical opportunities in documenting and treating diabetes despite laboratory evidence.
Background
Diabetes mellitus, particularly type 2 diabetes, remains a major global public health concern due to its high prevalence and the associated risk of cardiovascular disease, nephropathy, neuropathy, and retinopathy. Early diagnosis and timely initiation of appropriate treatment are critical to mitigate long-term complications. However, despite routine laboratory testing such as glycated hemoglobin (HbA1c), delays or gaps in formal diagnosis coding and pharmacologic treatment are often observed. These lapses may result in suboptimal patient management and missed chances for intervention. Understanding patterns of diagnostic coding and treatment initiation against laboratory-confirmed diabetes diagnoses can inform strategies to close these care gaps.
Study Design
This retrospective cohort study utilized national commercial and Medicare claims data from 2017 to 2023, linked with laboratory results identifying adults aged ≥18 years with laboratory-confirmed diabetes based on HbA1c levels ≥6.5%, and with no prior claims-coded history of diabetes or prediabetes. The study population was followed for one year to assess the outcomes of documented type 2 diabetes diagnosis coding and initiation of pharmacologic treatment (e.g., metformin or other antidiabetics). The influence of diagnostic HbA1c strata and overall comorbidity burden on these outcomes was examined.
Key Findings
The study cohort consisted of 27,650 adults with newly laboratory-confirmed diabetes. Within one year post-laboratory confirmation, 66.6% received both diabetes diagnostic coding on claims and pharmacologic treatment initiation, indicating concordant recognition and management. However, substantial care gaps emerged:
- 19.7% received diagnostic coding only without initiating pharmacologic treatment.
- 4.1% initiated pharmacologic treatment despite lacking formal diagnostic coding.
- 9.6% neither received a diabetes diagnosis code nor pharmacologic therapy.
Higher initial HbA1c levels demonstrated a graded association with greater probability of receiving both diagnosis coding and treatment. Compared with baseline HbA1c of 6.5-6.9%, those with higher HbA1c values were increasingly likely to have documented diagnosis and treatment. This suggests clinicians prioritize formal diagnosis and medication for patients with more severe hyperglycemia.
Conversely, a higher comorbidity burden—measured by established indices reflecting the presence of other chronic conditions—was linked to lower probabilities of both diabetes diagnosis coding and pharmacologic treatment initiation. This finding implies that the complexity of concurrent illnesses may detract focus from diabetes management or deprioritize pharmacologic intervention.
Expert Commentary
These findings illuminate critical care gaps in translating laboratory evidence of diabetes into clinical action. The divergence between laboratory confirmation and administrative coding highlights potential weaknesses in disease recognition, documentation practices, or patient follow-up processes. Patients without reported diagnosis or treatment may experience delayed risk factor modification, leading to preventable complications.
The association of higher comorbidity burden with reduced diagnostic coding and treatment suggests competing clinical priorities or clinical inertia when managing multimorbid patients. It might also reflect complexities in clinical decision-making where polypharmacy risks or patient preferences influence care choices.
Recent guidelines emphasize individualized diabetes management, especially in patients with extensive comorbidities, which may partly explain treatment hesitancy. Nonetheless, formal diagnosis coding remains essential for surveillance, quality improvement, and appropriate resource allocation.
Limitations include reliance on claims data, which may miss coding done outside of billing processes, and potential variations in laboratory assay reporting. The observational design precludes causal inferences but provides real-world practice insights.
Conclusion
This national cohort study reveals that approximately one-third of adults with laboratory-confirmed diabetes are not documented or treated in healthcare claims within one year, emphasizing important diagnostic and therapeutic gaps. Glycemic severity positively influences care engagement, whereas high comorbidity burden is a barrier. Efforts to improve coding reliability, provider education, and integrated care approaches for multimorbid patients are warranted to bridge these gaps and optimize diabetes outcomes.
Funding and Clinical Trials Registry
The study by Stimpson et al. did not specify funding sources or clinical trial registration within the published abstract. Further details may be available in the full text.
References
1. Stimpson JP, Tang Y, Pena Bojorges R, Liao JM. Gaps in Diagnosis and Treatment of Patients With Laboratory-Confirmed Diabetes: A National Cohort Study. Diabetes Care. 2026 Oct 5; PMID: 42832327.
2. American Diabetes Association. Standards of Medical Care in Diabetes—2024. Diabetes Care. 2024 Jan;47(Suppl 1):S1–S283.
3. Rawshani A, Rawshani A, Franzén S, et al. Mortality and Cardiovascular Disease in Type 1 and Type 2 Diabetes. N Engl J Med. 2017;376(15):1407-1418.
4. Lipska KJ, Ross JS, Wang Y, et al. Potential overtreatment of diabetes mellitus in older adults with tight glycemic control. JAMA Intern Med. 2015;175(3):356-362.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.