Validating the Patient Dignity Inventory to Enhance Recovery in Acute Respiratory Failure Survivors
Highlight
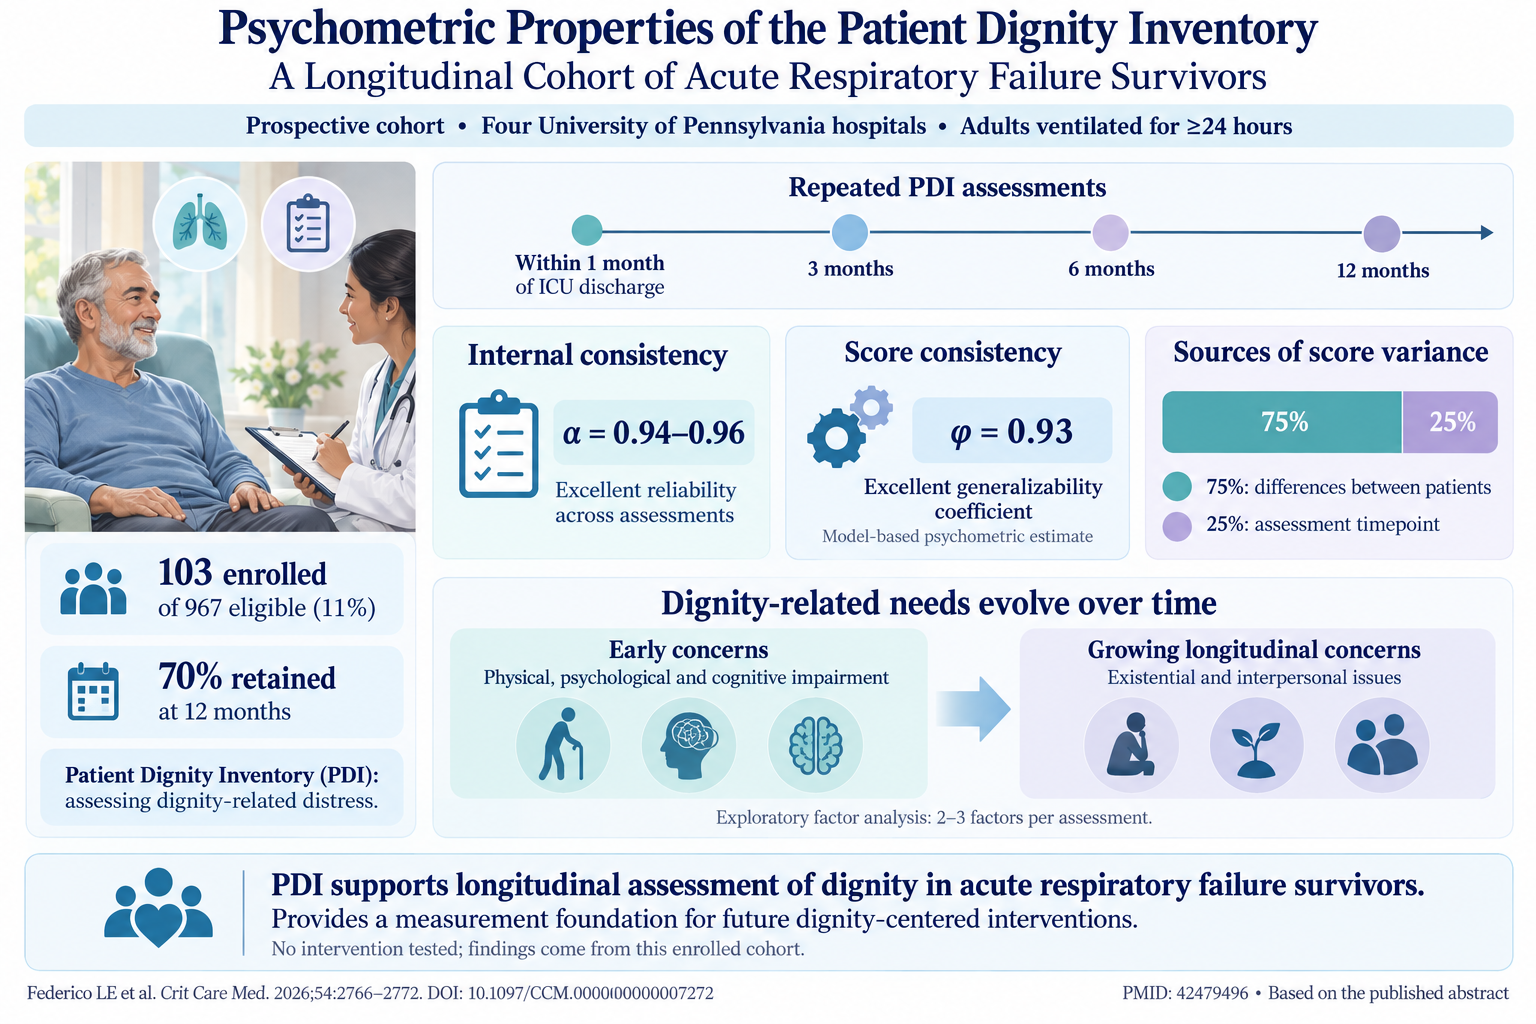
More than half of acute respiratory failure (ARF) survivors develop postintensive care syndrome, yet dignity-centered interventions remain underexplored in this population. The Patient Dignity Inventory (PDI) shows excellent internal consistency and generalizability for assessing dignity-related distress longitudinally post-ICU discharge. Distress dimensions shift from physical/psychologic impairments early to existential and interpersonal concerns over time. Establishing a minimal clinically important difference (MCID) facilitates future clinical trials of dignity-focused interventions.
Study Background
Acute respiratory failure (ARF), often requiring mechanical ventilation in intensive care units (ICUs), places survivors at high risk for developing postintensive care syndrome (PICS). PICS encompasses physical, cognitive, and psychosocial impairments that may persist long after ICU discharge, compromising quality of life. Despite growing recognition of PICS, interventions targeting existential and dignity-related distress remain sparse, especially among ARF survivors.
Dignity-centered care approaches, such as those validated in palliative and chronic disease settings, improve psychosocial and existential outcomes but have not been longitudinally validated in ARF survivors. The Patient Dignity Inventory (PDI) is a psychometrically robust instrument initially developed in end-of-life care to measure dignity-related distress across multidimensional domains. Validating the PDI for ARF survivors could provide a vital tool to guide personalized interventions addressing evolving needs during recovery.
Study Design
This prospective cohort study recruited mechanically ventilated adult patients (≥24 hours) from four University of Pennsylvania hospital ICUs between June 2022 and April 2023. Eligible patients survived ARF requiring ICU care and mechanical ventilation. The study collected data at baseline (within 1 month post-ICU discharge) and longitudinally at 3, 6, and 12 months thereafter, with no intervention administered during the study.
Primary outcomes included the assessment of PDI psychometric properties over time: internal consistency (Cronbach’s alpha), factor structure (exploratory factor analysis), generalizability (variance component analysis with multilevel mixed-effects modeling and phi coefficient), and determination of the minimal clinically important difference (MCID) using anchor-based and distribution-based methods. The EuroQol-5 Dimension (EQ-5D) index served as the anchor metric for MCID estimation.
Key Findings
Out of 967 eligible patients, 103 (11%) enrolled at baseline, with 70% retention at 12 months confirming the feasibility of longitudinal assessment. The PDI demonstrated excellent internal consistency throughout all timepoints, with Cronbach’s alpha ranging from 0.94 to 0.96, indicating high reliability of the instrument in measuring dignity-related distress consistently across the recovery trajectory.
Factor analysis revealed a dynamic structure of dignity-related distress domains. Early post-ICU assessments, typically within 1 month, identified 2 to 3 predominant factors centered on physical, psychological, and cognitive impairments—reflecting common PICS manifestations. As time progressed, existential and interpersonal concerns, such as loss of meaning and social isolation, became increasingly prominent, highlighting the shifting psychosocial landscape among ARF survivors following ICU discharge.
Variance component analysis quantified that 75% of the variance in PDI scores was attributable to inter-patient differences, with 25% due to temporal changes across assessments. The resulting phi coefficient of 0.93 indicated excellent consistency and generalizability of the PDI scores longitudinally.
The MCID was derived by averaging anchor-based and distribution-based estimates, integrating EQ-5D MCID values and statistical distribution parameters such as the standard error of the mean and score range percentages. Establishing an MCID around this validated threshold supports meaningful clinical interpretation of changes in dignity-related distress over time, facilitating outcome evaluations in future interventional trials.
Expert Commentary
This study fills an important gap by validating a multidimensional dignity assessment tool tailored to ARF survivors, advancing critical care survivorship research beyond traditional physical and cognitive metrics. By capturing evolving existential and interpersonal dimensions, the PDI enables clinicians to identify nuanced psychosocial needs and tailor interventions accordingly.
Despite robust psychometric validation, the study is limited by modest enrollment and attrition inherent to longitudinal ICU survivor cohorts, which may affect representativeness and generalizability across diverse populations. Future research should explore integrating the PDI into routine post-ICU follow-up and evaluate dignity-centered interventions to improve holistic recovery and quality of life.
These findings align with prior evidence supporting dignity therapy and related psychosocial interventions in palliative contexts. Translating these approaches to ARF survivors offers an innovative avenue to address complex survivorship issues including depression, anxiety, and social disconnection.
Conclusion
The Patient Dignity Inventory is a reliable, valid, and generalizable instrument for longitudinal assessment of dignity-related distress in acute respiratory failure survivors. Its application enables the identification of shifting psychosocial and existential needs across recovery, providing an essential foundation for designing dignity-centered interventions aimed at improving long-term outcomes. Incorporating the PDI within clinical and research frameworks promises enhanced care quality and survivorship support tailored to this vulnerable population.
Funding and Registration
The study was conducted by investigators at the University of Pennsylvania. No interventions were applied during the study period, and funding sources were not explicitly reported in the publication. Clinical trial registration details were not provided.
References
- Federico LE, Kwiatkowski C, Dine CJ, et al. Psychometric Properties of the Patient Dignity Inventory in a Longitudinal Cohort of Acute Respiratory Failure Survivors. Crit Care Med. 2026 Oct;54(10):2766-2772. PMID: 42479496.
- Needham DM, Davidson J, Cohen H, et al. Improving long-term outcomes after discharge from intensive care unit: Report from a stakeholders’ conference. Crit Care Med. 2012;40(2):502-509.
- Chochinov HM. Dignity and the essence of medicine: the A, B, C, and D of dignity conserving care. BMJ. 2007;335(7612):184-187.
- Jackson JC, Hart RP, Gordon SM, Hopkins RO, Arena VC, Ely EW. Six-month neuropsychological outcome of medical intensive care unit patients. Crit Care Med. 2003;31(4):1226-1234.
- Rabiee A, Nikayin S, Hashem MD, et al. Depressive symptoms after critical illness: a systematic review and meta-analysis. Crit Care Med. 2016;44(9):1744-1753.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.