Team Behavior and Patient Outcome Changes Following Human Factors Training in Pediatric Airway Endoscopy: A Review of Evidence and Clinical Implications
Highlights
- Multimodal human factors interventions significantly improve adherence to structured communication and nontechnical skills in pediatric airway surgeries.
- Behavioral improvements include more consistent checklist utilization, enhanced team interactions, and reduction of task interruptions during critical procedural phases.
- The integration of aviation-inspired crew resource management and simulation training bolsters operating room teamwork and situational awareness.
- While immediate clinical patient outcomes remained unchanged, the observed improvements indicate a positive culture shift and suggest long-term safety benefits.
Background
Pediatric airway endoscopy, including laryngotracheal procedures, represents a high-stakes surgical environment due to the complexity of airway management and the involvement of multidisciplinary teams. Despite advances in surgical techniques, adverse events and patient harm often derive from communication failures and deficits in nontechnical skills (NTS) such as teamwork, situational awareness, and decision-making. Unlike adult surgical disciplines, pediatric surgical training rarely incorporates formal human factors education, creating an unmet need for interventions enhancing operating room (OR) culture and team behavior.
Evidence from other high-risk industries like aviation demonstrates that structured human factors programs reduce errors and improve outcomes. Borrowing from such models, multidisciplinary perioperative teams have begun adopting structured checklists, role identification, and simulation-based training to mitigate errors related to teamwork and communication in surgery.
Key Content
Evolution of Human Factors Training in Surgery
Early integration of human factors into surgical practice began in the late 1990s, driven by seminal works linking team communication to surgical safety incidents (Lingard et al., 2004). The WHO Surgical Safety Checklist (2008) marked a pivotal intervention standardizing team communication globally. Subsequent studies emphasized that checklist adherence alone was insufficient without accompanying cultural and behavioral shifts achieved through training in nontechnical skills (Hull et al., 2017).
Human Factors in Pediatric Airway Surgery
Pediatric airway endoscopy demands precise coordination among surgeons, anesthesiologists, and nursing staff. Deficiencies in communication or interruptions during critical phases can precipitate adverse events, including hypoxia and airway trauma. Studies (such as Cadre et al. 2026) have employed the Non-Technical Skills for Surgeons (NOTSS) framework to quantify team behavior improvements post-intervention.
Components of Multimodal Human Factors Interventions
Effective programs typically combine several elements:
- Structured Preoperative Checklists: Ensure shared mental models and readiness, improving both team situational awareness and task sequencing.
- Personalized Identification Tools: Use of labeled caps or badges clarifies roles and fosters accountability.
- Simulation-Based Training: Scenario-based rehearsals model crisis resource management adapted from aviation crew resource management (CRM), enhancing communication strategies and team decision-making under pressure.
Several randomized controlled trials and quality improvement studies corroborate that such bundles decrease task interruptions, optimize noise levels, and elevate observed nontechnical skills scores, measured through standardized tools like NOTSS or Oxford NOTECHS II.
Evidence from the Cadre et al. (2026) Study
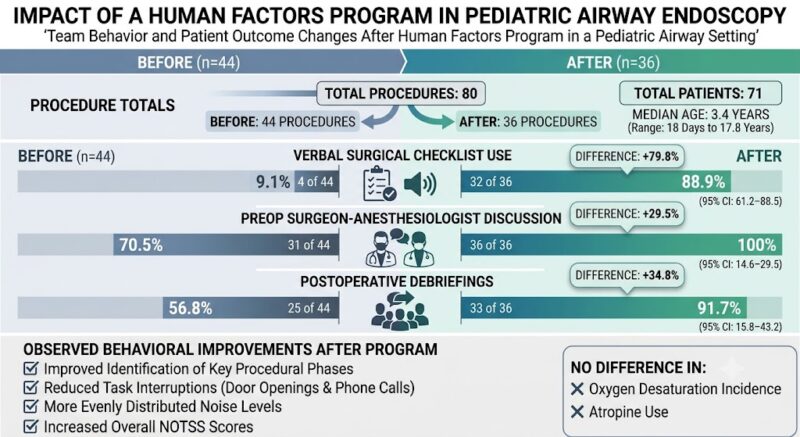
In a prospective pre-post quality improvement study at a tertiary pediatric center, 80 laryngotracheal endoscopic procedures were evaluated. Following implementation of a comprehensive human factors program:
- Checklist verbalization rose dramatically from 9.1% to 88.9%, ensuring consistent communication.
- Preoperative discussions between surgeons and anesthesiologists improved from 70.5% to 100%, enhancing shared situational awareness.
- Task interruptions, particularly distractions such as door openings and phone calls during critical phases, were markedly reduced.
- Noise levels, an often overlooked environmental factor, became more evenly distributed, likely lowering stress and promoting attention.
- NOTSS scores increased, reflecting better teamwork, decision-making, and leadership in the OR.
Despite these behavioral and environmental improvements, no significant changes were observed in immediate clinical outcomes like oxygen desaturation or atropine use, indicating the program’s impact was primarily on process and culture.
Translational Implications and Broader Evidence
Multiple meta-analyses of human factors interventions in surgery (e.g., De Vries et al., 2010; Haynes et al., 2011) have shown that comprehensive team training reduces perioperative complications and mortality, although pediatric airway surgical data has historically been sparse. The findings by Cadre et al. provide important pediatric-specific evidence supporting institutional investment in human factors education.
Importantly, behavioral changes represent a Kirkpatrick level 3 outcome—actual modification of participants’ behavior—predicting sustained improvements in patient safety. Organizational culture shifts fostered by such programs contribute to long-term reductions in sentinel events and promote resilience in high-pressure clinical settings.
Expert Commentary
The Cadre et al. study exemplifies the pragmatic application of aviation-derived CRM principles within a pediatric surgical domain, illustrating how a multimodal human factors program can instill effective communication habits and reduce sensory distractions.
However, the lack of immediate clinical outcome differences tempers claims of efficacy, underscoring the challenges in linking behavioral interventions with measurable patient outcomes in relatively low-frequency adverse event environments. Methodological limitations include single-center design and relatively small cohort size, limiting generalizability.
Current clinical guidelines are beginning to acknowledge the value of human factors training, recommending incorporation into surgical education curricula. Future research should pursue multicenter randomized designs with longer follow-ups to capture effects on morbidity and mortality. Additionally, expanding training modules to include psychological safety and interprofessional dynamics may further consolidate team performance improvements.
Conclusion
Structured human factors training programs are demonstrably effective at enhancing operating room communication, coordination, and nontechnical surgical skills during pediatric airway procedures. Behavioral and environmental improvements represent meaningful progress towards safer surgical care environments, despite immediate clinical outcome stability.
The evidence supports the integration of human factors education into pediatric surgical training and continued quality improvement initiatives. Sustained cultural change, powered by multidisciplinary commitment and periodic simulation reinforcement, promises to mitigate preventable errors and elevate pediatric airway surgery safety.
References
- Cadre B, Luscan R, Chen X, Garcelon N, Simon F, Thierry B. Team Behavior and Patient Outcome Changes After Human Factors Program in a Pediatric Airway Setting. JAMA Otolaryngol Head Neck Surg. 2026 Aug 6;PMID:42560705.
- Lingard L, Espin S, Whyte S, et al. Communication failures in the operating room: an observational classification of recurrent types and effects. Qual Saf Health Care. 2004 Feb;13(2): 330-334. doi:10.1136/qshc.2003.009425.
- Haynes AB, Weiser TG, Berry WR, et al. A Surgical Safety Checklist to Reduce Morbidity and Mortality in a Global Population. N Engl J Med. 2009;360(5):491-499. doi:10.1056/NEJMsa0810119.
- De Vries EN, Prins HA, Crolla RM, et al. Effect of a comprehensive surgical safety system on patient outcomes. N Engl J Med. 2010 Jan 7;362(20):1928-37. doi:10.1056/NEJMsa0911535.
- Hull L, Arora S, Kassab E, Kneebone R, Sevdalis N. Observational teamwork assessment for surgery: content validation and tool refinement. J Am Coll Surg. 2011 May;212(5):234-243. doi:10.1016/j.jamcollsurg.2010.11.001.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.