Highlight
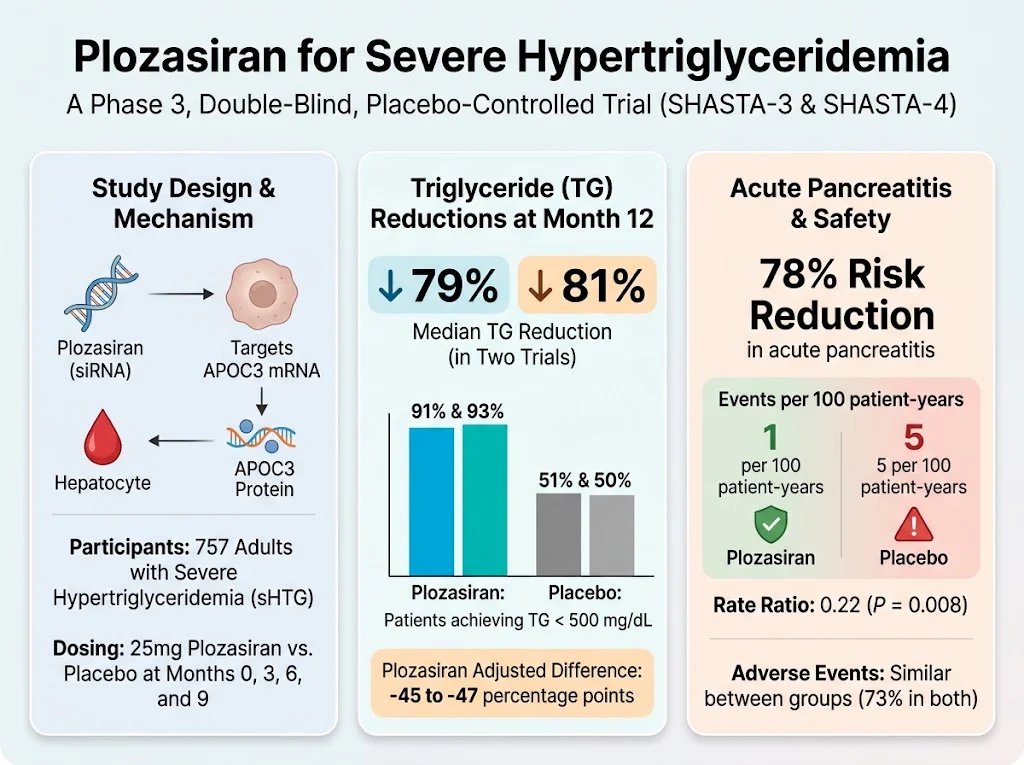
Plozasiran, an siRNA therapy targeting APOC3 mRNA, reduces fasting triglyceride levels by approximately 80% in patients with severe hypertriglyceridemia after 12 months.
Significant reduction in acute pancreatitis incidence was observed with plozasiran, with a rate ratio of 0.22 versus placebo.
The treatment demonstrated safety comparable to placebo, with similar adverse event rates across groups.
Majority of patients achieved triglyceride levels below 500 mg/dL, a clinically relevant threshold to reduce pancreatitis risk.
Study Background
Severe hypertriglyceridemia, defined by triglyceride levels substantially exceeding 500 mg/dL, is a strong and independent risk factor for acute pancreatitis, a potentially life-threatening inflammatory condition of the pancreas. Conventional lipid-lowering therapies often fall short in adequately reducing triglyceride levels in this population. Apolipoprotein C-III (APOC3) is a key regulator inhibiting the catabolism of triglyceride-rich lipoproteins, thus representing a promising therapeutic target. Plozasiran is an innovative small interfering RNA (siRNA) that selectively inhibits APOC3 messenger RNA, leading to decreased synthesis of APOC3 protein and subsequent reduction in plasma triglycerides. This molecular approach aims to improve lipid control and mitigate pancreatitis risk in patients with severe hypertriglyceridemia, addressing a significant unmet medical need.
Study Design
The efficacy and safety of plozasiran were evaluated in two parallel, double-blind, randomized, placebo-controlled phase 3 trials—SHASTA-3 (NCT06347003) and SHASTA-4 (NCT06347016). A total of 757 adults diagnosed with severe hypertriglyceridemia were enrolled and randomized in a 2:1 ratio to receive either plozasiran (25 mg) or placebo. Treatment was administered subcutaneously at baseline and at months 3, 6, and 9, with follow-up at month 12. The trials shared identical protocols, endpoints, and statistical analysis plans.
The primary endpoint was the percent change in fasting plasma triglyceride levels from baseline to 12 months. Key secondary endpoints included percent change at month 10, proportions of patients achieving triglyceride levels below 500 mg/dL and 150 mg/dL, triglyceride response in the subgroup with baseline levels ≥880 mg/dL, and changes in remnant cholesterol and non-HDL cholesterol. A pooled analysis of both trials also explored the incidence and timing of adjudicated acute pancreatitis events.
Key Findings
At 12 months, patients treated with plozasiran showed remarkable median reductions in fasting triglycerides of 79% and 81% in SHASTA-3 and SHASTA-4, respectively. Compared with placebo, the adjusted percent difference reached -45 percentage points (95% confidence interval [CI], -51 to -38) and -47 percentage points (95% CI, -54 to -39). The clinical impact was underscored by the high rates of patients achieving triglyceride levels under 500 mg/dL, reaching 91% in SHASTA-3 and 93% in SHASTA-4 versus approximately 50% in placebo groups (P<0.001). The more stringent target of under 150 mg/dL was also achieved by a greater fraction on plozasiran, reflecting robust control.
Importantly, the pooled analysis demonstrated that plozasiran treatment was associated with a significant reduction in acute pancreatitis rates—1 event per 100 patient-years compared to 5 events per 100 patient-years in placebo arms—yielding a rate ratio of 0.22 (P=0.008). This translates to a nearly 80% relative risk reduction, an outcome of considerable clinical relevance.
Markers of remnant cholesterol and non-HDL cholesterol were also favorably reduced, aligning with the lipid-lowering mechanism targeting APOC3.
Regarding safety, adverse events occurred similarly in both plozasiran and placebo groups (73%), indicating a comparable tolerability profile. No major safety signals emerged to compromise clinical utilization.
Expert Commentary
These results position plozasiran as a promising therapeutic agent in the management of severe hypertriglyceridemia, a condition traditionally difficult to treat and associated with considerable risk of pancreatitis and cardiovascular complications. By leveraging RNA interference technology, plozasiran demonstrates the capacity to achieve profound and sustained triglyceride reductions through a novel mechanism targeting APOC3, validating this protein as a critical modulator of triglyceride metabolism.
While these trials offer robust evidence from a large patient cohort with rigorous adjudication, longer-term data and post-marketing surveillance will be critical to ensure sustained efficacy and monitor rare adverse events. The inclusion of diverse patient subgroups and real-world studies will further clarify generalizability. Additionally, mechanistic insights into the interplay between APOC3 inhibition and pancreatic inflammation warrant further exploration.
Conclusion
Plozasiran provides a significant advancement for patients with severe hypertriglyceridemia by dramatically lowering triglyceride levels and reducing the risk of acute pancreatitis. The siRNA therapeutic paradigm demonstrated here expands the arsenal of lipid-lowering strategies with a favorable safety profile and promising clinical benefit. Incorporating plozasiran into treatment algorithms has the potential to improve outcomes in this high-risk population and inform future RNAi-based therapies for metabolic diseases.
Funding and Clinical Trials Information
This work was funded by Arrowhead Pharmaceuticals. The SHASTA-3 and SHASTA-4 trials are registered under ClinicalTrials.gov identifiers NCT06347003 and NCT06347016, respectively.
References
1. Watts GF, Ballantyne CM, Blanco Echevarria A, et al. Plozasiran for Severe Hypertriglyceridemia and Risk of Pancreatitis. N Engl J Med. 2026 Nov 5;395(18):1805-1817. doi:10.1056/NEJMoa2621109
2. Gaudet D, Alexander VJ, Baker BF, et al. Antisense Inhibition of Apolipoprotein C-III in Patients with Hypertriglyceridemia. N Engl J Med. 2015;373(5):438-447.
3. Hegele RA, Ginsberg HN, Chapman MJ, et al. The polygenic nature of hypertriglyceridemia: implications for definition, diagnosis, and management. Lancet Diabetes Endocrinol. 2014 June;2(5): 350–361.