Optimizing Fertility and Pregnancy Outcomes in Women with Congenital Adrenal Hyperplasia
Highlight
Congenital adrenal hyperplasia (CAH) due to 21-hydroxylase deficiency significantly reduces fertility in women despite preserved potential across phenotypes. Successful pregnancy hinges on normalization of preconception follicular phase progesterone levels, requiring precise glucocorticoid dosing and timing. Even specialized centers report prolonged time to conception, highlighting ongoing challenges.
Study Background
Congenital adrenal hyperplasia (CAH) is a group of autosomal recessive disorders characterized by enzymatic defects in cortisol biosynthesis, of which 21-hydroxylase deficiency (21OHD) is the most common variant. In females, CAH manifests with a spectrum from classic salt-wasting or simple-virilizing forms to non-classic phenotypes. Although female patients across all phenotypes generally maintain fertility potential, clinical experience shows markedly reduced fertility compared to the general population.
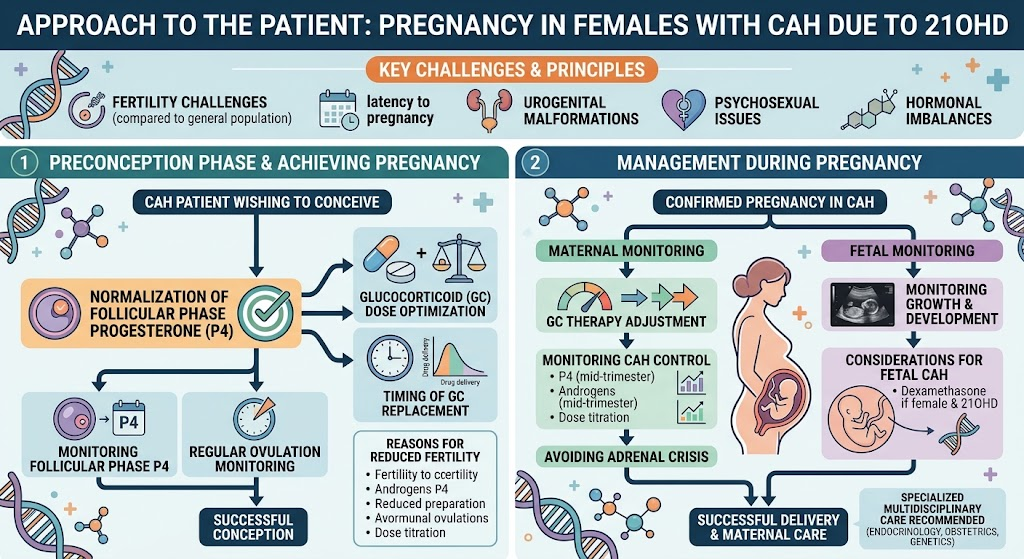
Challenges to fertility in CAH are multifactorial: anatomical urogenital malformations related to prenatal androgen exposure may complicate sexual function; psychosexual issues such as anxiety and reduced libido further impair reproductive outcomes; and hormonal imbalances, most notably elevated progesterone and androgens stemming from adrenal hyperactivity, disrupt the normal ovulatory cycle and embryo implantation.
Clinical practice today increasingly recognizes that while many CAH patients are able to conceive, latency to pregnancy is often significantly prolonged. Specialized endocrine and reproductive centers report that normalization of hormonal milieu before conception is critical to improve pregnancy success rates and maternal-fetal health.
Study Design
The article by Reisch et al. synthesizes clinical observations and expert consensus regarding the management of pregnancy in women with CAH caused by 21-hydroxylase deficiency. Although this is not a primary research trial, the authors analyze multiple cohort experiences from specialized centers, focusing on preconception preparation and pregnancy monitoring.
The authors emphasize critical intervention points: preconception hormone assessment, glucocorticoid (GC) therapy adjustments targeting follicular phase progesterone normalization, and ongoing endocrine follow-up during pregnancy. They discuss timing and dosage of GC replacement as key variables influencing ovulatory function and conception latency. The narrative also addresses clinical endpoints such as time to pregnancy, miscarriage rates, and maternal and neonatal outcomes.
Key Findings
Fertility is impaired across CAH phenotypes despite a broad spectrum of clinical severity, with multiple contributors:
- Hormonal Imbalance: Elevated adrenal progesterone during the follicular phase acts as a natural contraceptive by preventing normal follicular development and corpus luteum function, crucial in ovulation and implantation.
- Anatomical Changes: Urogenital malformations, including persistent urogenital sinus and genital ambiguity, despite surgical repair, may hamper sexual function and conception.
- Psychosexual Impact: Psychological stress, sexual dysfunction, and body image concerns may reduce fertility through behavioral pathways.
Normalization of progesterone levels in the follicular phase before conception emerged as the cornerstone of successful pregnancy. Achieving this requires thoughtful glucocorticoid therapy — not only adjusting the dose but also timing the administration to optimize diurnal cortisol patterns and minimize adrenal androgen and progesterone excess.
The authors report that even under expert care in specialized centers, time to conceive is substantially longer than general population averages. This latency reflects ongoing challenges in balancing adequate hormone suppression, avoiding overtreatment, and managing individual patient variability.
Monitoring during pregnancy should include continued glucocorticoid adjustments based on trimester-specific physiological changes and potential fetal exposure risks. Screening for fetal virilization remains essential in classic CAH cases.
Expert Commentary
Recent expert guidelines advocate individualized care for reproductive-aged women with CAH emphasizing hormonal control preconception and close interdisciplinary collaboration among endocrinologists, gynecologists, and mental health professionals.
Mechanistically, the adrenal overproduction of progesterone and androgens creates a challenging endocrine environment for ovulation and implantation, consistent with observations in other hyperandrogenic states like polycystic ovary syndrome (PCOS). While glucocorticoid treatment suppresses adrenal steroidogenesis, dosing requires precise titration to avoid overtreatment consequences such as Cushingoid features or impaired maternal and fetal health.
Limitations in the current evidence include small cohort sizes, heterogeneity of CAH phenotypes, and limited longitudinal pregnancy outcome data. Further controlled studies are warranted to optimize timing and protocols for glucocorticoid replacement therapy tailored to reproductive goals.
Conclusion
Women with CAH due to 21-hydroxylase deficiency face significant fertility challenges, driven predominantly by hormonal dysregulation, anatomic factors, and psychosocial elements. Successful pregnancy is contingent on normalizing follicular phase progesterone levels prior to conception, achievable through individualized glucocorticoid therapy with attention to dosing and timing.
Comprehensive care involves early and ongoing collaboration among endocrinology, reproductive medicine, and psychology services to maximize pregnancy outcomes. Despite advances, fertility latency remains prolonged and warrants further research to refine treatment strategies and improve maternal-fetal health in this unique patient population.
Funding and Clinical Trials
The article does not specify funding sources or clinical trial registrations. Further dedicated prospective studies may benefit from standardized protocols and registry enrollment to advance evidence-based management of pregnancy in CAH.
References
- Speiser PW, White PC. Congenital adrenal hyperplasia. N Engl J Med. 2003;349(8):776-788. doi:10.1056/NEJMra021561
- Merke DP, Bornstein SR. Congenital adrenal hyperplasia. Lancet. 2005;365(9477):2125-2136. doi:10.1016/S0140-6736(05)66781-4
- Reisch N, et al. Approach to the Patient: The Pregnant Woman with Congenital Adrenal Hyperplasia. J Clin Endocrinol Metab. 2026; PMID:42615102.
- Falhammar H, et al. Fertility, reproductive health and outcomes in females with congenital adrenal hyperplasia. Endocrine Reviews. 2018;39(4): 614–655.
- Debono M, et al. Optimizing glucocorticoid therapy in congenital adrenal hyperplasia: current considerations and future challenges. Endocr Rev. 2021;42(1):47-71.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.