Mental Health and Substance Use Disorder Expenditures in the US: Profiling Costs and Implications for Policy and Care Optimization
Highlights
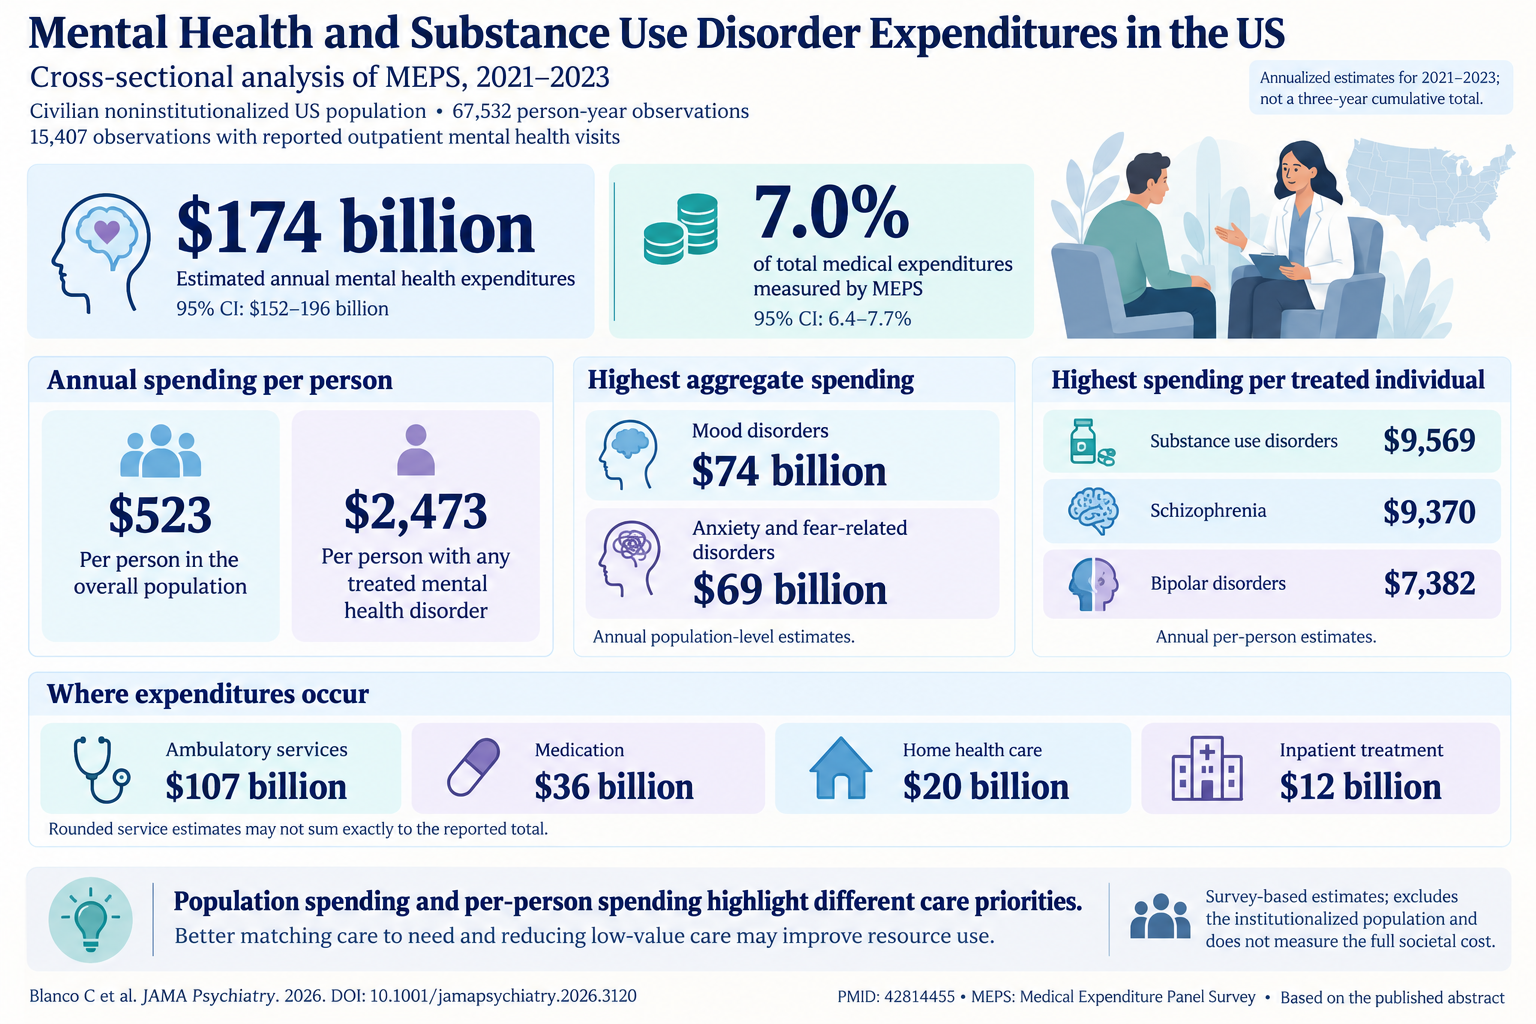
- Mental health and substance use disorder (SUD) expenditures in the US comprise around 7% of total medical spending, with wide individual-level variation.
- Substance use disorders, schizophrenia, and bipolar disorders generate the highest per-person expenditures, reflecting intensive treatment needs.
- Ambulatory services constitute the largest share of mental health spending, followed by medication, home health, and inpatient care.
- Current expenditures are disproportionately low relative to the societal burden and highlight pressing needs for more effective, value-based care and equitable resource allocation.
Background
Mental health disorders and substance use disorders (SUDs) contribute substantially to morbidity and mortality in the US, affecting millions annually. Despite the high public health burden, mental health care expenditures remain inadequately characterized in terms of magnitude and distribution across sociodemographic groups, disorder types, and service utilization. Understanding the expenditure landscape is critical for policymakers to align resource allocation with public health priorities, optimize care delivery, and address persistent treatment gaps amidst expanding mental health legislation and evolving insurance paradigms.
Key Content
Cross-sectional National Expenditure Estimates (2021-2023 MEPS Data)
The landmark 2026 study by Blanco et al. employed the Medical Expenditure Panel Survey (MEPS) data from 2021 through 2023, encompassing 67,532 person-year observations weighted to the US civilian noninstitutionalized population. Approximately 15,407 individuals had at least one outpatient mental health visit across these years. The estimated aggregate total healthcare spending was about $2.5 trillion annually, with mental health-related expenditures accounting for $174 billion (7.0% of all medical costs).
Mean per capita spending was $523 for all participants and $2,473 among treated individuals with mental health disorders, indicating substantial concentration of expenditures among patients receiving care. Mood disorders and anxiety/fear-related disorders contributed the largest aggregate costs—$74 billion and $69 billion respectively—consistent with their population prevalence.
Notably, per-person expenditures were highest among those treated for substance use disorders ($9,569), schizophrenia ($9,370), and bipolar disorder ($7,382), underscoring higher intensity or complexity of care in these groups. Service category analysis revealed ambulatory services consumed the majority ($107 billion), followed by medications ($36 billion), home health services ($20 billion), and inpatient care ($12 billion).
Sociodemographic and Insurance Variation
Although Blanco et al.’s main publication primarily focused on aggregate and per-person expenditures, prior literature contextualizes trends showing disparities by age, sex, socioeconomic status, and insurance type, often intertwined with differential access, stigma, and cost-sharing barriers. For example, veterans, a population characterized by higher prevalence of substance use and mental health disorders, experience persistent unhealthy drinking patterns with associated economic burdens, as delineated in national surveys (e.g., BRFSS 2016-2024).
Comorbidities and Expenditure Multipliers
Coexisting physical and mental health conditions drive incremental healthcare costs. The Australian Genetics of Depression Study demonstrated that adults with depression often possess multiple comorbidities (mean ~4.6), substantially elevating healthcare utilization and costs. Similar patterns are reported in US HIV cohorts, with mental health and substance use disorders elevating total costs significantly post-diagnosis.
Innovations in Cost-Effective Mental Health Interventions
Emerging evidence supports integrated and scalable interventions to reduce costs while improving outcomes. The PROVIDE-C randomized controlled trial showed that integrated mental health video consultations yielded improved depression and anxiety outcomes with promising cost-utility over standard care. Community-based programs combining exercise with volunteering demonstrated meaningful mental health improvements at lower societal costs. Pharmacist-led clinics, such as in epilepsy care, also illustrate potential expenditure reductions through task-shifting and integrated mental health screening.
Service Preferences and Barriers Affecting Utilization and Cost Patterns
Discrete choice experiments among stroke survivors and machine learning models for unmet mental health needs reveal the importance of service attributes (e.g., cost, session length, provider type), and patient-level barriers including stigma, cost, and navigational challenges. Understanding these factors facilitates designing interventions that align better with patient preferences, increasing adherence and potentially lowering downstream costs.
Expert Commentary
The studies collectively underscore that mental health and SUD expenditure patterns reflect two critical realities: substantial variation in cost intensity by disorder and treatment complexity, and an overall underinvestment relative to the population burden. The per-person expenditure for SUDs and severe mental illnesses (schizophrenia, bipolar disorder) signifies the need for intensive, often multidisciplinary care, justifying targeted funding.
However, the fact that mental health spending constitutes only 7% of total medical expenditures suggests persistent funding gaps, possible under-treatment, and unmet needs. This is corroborated by machine learning analyses demonstrating large untreated populations with unmet mental health needs due to costs and barriers.
Innovations in telehealth, technology-enabled care, and community-based interventions offer promising avenues to expand access, reduce low-value care, and optimize resource use. Yet, widespread implementation faces challenges including reimbursement policies, workforce capacity, and ensuring equity in access.
The heterogeneity in patient preferences revealed in discrete choice research emphasizes that “one-size-fits-all” approaches risk inefficiency and poor adherence. Tailoring services to demographics and disorder-specific needs is pivotal.
An informed policy approach must therefore balance increasing investment with strategic deployment of integrated care models, leveraging technology and diversifying provider roles to better address complex needs.
Conclusion
Recent comprehensive analyses have elucidated the scale and distribution of mental health and substance use disorder expenditures in the US, highlighting variability by disorder and service type, with a substantial gap between societal burden and current spending levels. Advancements in scalable, integrated, and cost-effective care models demonstrate potential for improving outcomes and optimizing expenditures.
Future priorities include further refining expenditure modeling, expanding accessible digital mental health platforms, addressing socio-economic barriers, and incorporating patient preferences into care design. Continued research to evaluate effectiveness and economic impact of emerging interventions will be essential to inform policies that meaningfully improve mental health care financing and delivery.
References
- Blanco C, McClellan C, Zuvekas SH, Olfson M. Mental Health and Substance Use Disorder Expenditures in the US. JAMA Psychiatry. 2026 Sep 30. PMID: 42814455. https://pubmed.ncbi.nlm.nih.gov/42814455/
- McClellan C, et al. Trends in and correlates of unhealthy alcohol consumption among US Veterans, 2016-2024. Addict Behav Rep. 2026 Jun;24:100717. PMID:42325422.
- Austrade AGDS Consortium. Burden of health comorbidities and healthcare costs in depression: Australian Genetics of Depression Study. J Affect Disord. 2026 Dec;414:122397. PMID:42612923.
- Schröder J, et al. Cost-effectiveness and cost-utility of integrated mental health video consultations (PROVIDE-C RCT). J Affect Disord. 2026 Nov 15;413:122280. PMID:42462930.
- Nowak L, et al. Machine learning for predicting unmet mental health treatment need among untreated adults. Psychiatry Res. 2026 Dec;366:117463. PMID:42759182.
- Schuch FB, et al. Getting fit by doing good: Exercise, volunteering, and mental health at scale. Soc Sci Med. 2026 Nov;408:119707. PMID:42753431.
- Kunitz S, et al. Pharmacist practitioner-led follow-up in VA epilepsy clinics and mental health screening. Epilepsy Behav Rep. 2026 Sep 21;36:100900. PMID:42835542.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.