Low-Dose Interleukin-2 in Newly Diagnosed Type 1 Diabetes: Insights from the DIABIL-2 Phase 2b Trial
Highlight
- Low-dose interleukin-2 (IL-2) selectively expands regulatory T cells (Tregs) in patients with newly diagnosed type 1 diabetes (T1D).
- The DIABIL-2 trial, a multicenter, double-blind, placebo-controlled phase 2b study, evaluated IL-2 for preservation of pancreatic β-cell function.
- Despite robust Treg expansion, low-dose IL-2 did not preserve endogenous β-cell function at 12 months compared to placebo.
- Low-dose IL-2 was well tolerated, suggesting potential for combination or earlier intervention approaches in T1D immunotherapy.
Study Background
Type 1 diabetes is an autoimmune disorder characterized by T-cell–mediated destruction of insulin-producing pancreatic β-cells. This leads to lifelong dependence on exogenous insulin and significant risks of acute and chronic complications. The underlying immune dysregulation includes inadequate function or number of regulatory T cells (Tregs), which normally maintain immune tolerance and prevent autoimmunity. Previous studies have demonstrated that low-dose interleukin-2 (IL-2) can selectively expand Tregs without broadly activating effector immune cells, presenting a potential immunomodulatory strategy for T1D. Prior phase 1 and 2a studies indicated biological activity with low-dose IL-2, but clinical efficacy in preserving residual β-cell function remained unclear.
Study Design
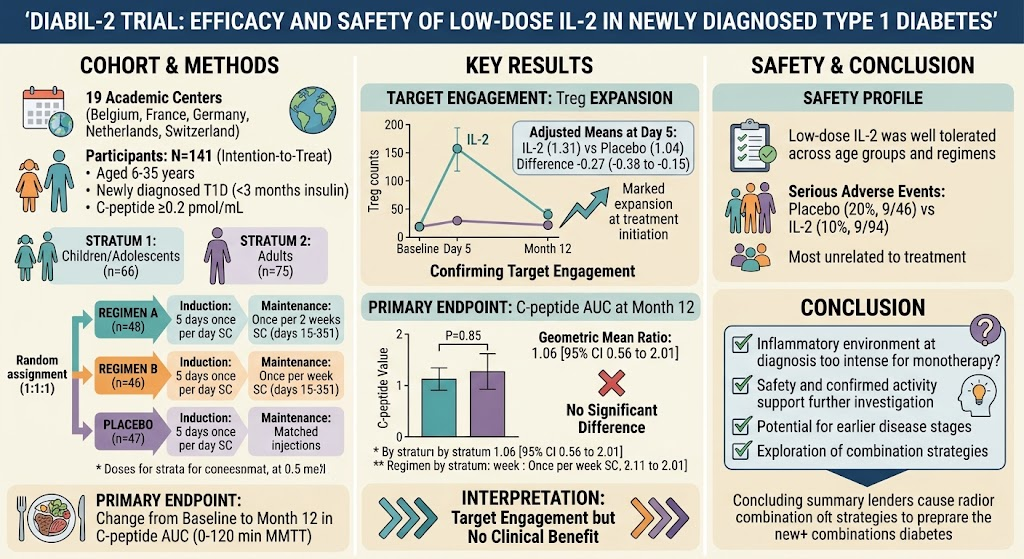
The DIABIL-2 trial was a double-blind, randomized, placebo-controlled, phase 2b study conducted at 19 academic hospitals across five European countries (Belgium, France, Germany, Switzerland, Netherlands). Eligible participants were aged 6 to 35 years, diagnosed with type 1 diabetes within the last 3 months, and had measurable residual β-cell function evidenced by a peak C-peptide level ≥0.2 pmol/mL during a mixed meal tolerance test (MMTT).
Participants were stratified by pubertal status (Tanner score ≤4 vs. ≥5) and randomized 1:1:1 to two IL-2 treatment regimens or placebo. Both regimens started with an induction of daily subcutaneous injections over 5 days (days 1-5). Maintenance dosing was either every 2 weeks (regimen A) or weekly (regimen B) from day 15 through 351. Adults received 1 million IU per injection whereas children/adolescents received 0.5 million IU/m2. Placebo groups were matched by regimen with a 2:1 allocation of IL-2 to placebo within each regimen.
The primary endpoint was the change from baseline to 12 months in stimulated C-peptide area under the curve (AUC) during a 120-minute MMTT, analyzed by intention-to-treat.
Key Findings
Among 141 enrolled participants (54 females, 87 males), 89% completed the study. The primary endpoint analysis showed no statistically significant preservation of β-cell function with low-dose IL-2 compared to placebo in the overall population (geometric mean ratio 1.06, 95% CI 0.56 to 2.01; p=0.85). Stratified analyses by regimen or pubertal status yielded similar null results.
Biologically, IL-2 treatment induced a significant increase in circulating Tregs, peaking at day 5 after induction injections, with a mean fold change of 1.31 compared to 1.04 in placebo (difference −0.27; 95% CI −0.38 to −0.15). This confirms target engagement and selective Treg expansion.
Safety data showed that low-dose IL-2 was well tolerated across age groups and dosing regimens. Serious adverse events (SAEs) occurred in 20% of placebo participants and 10% of IL-2 treated participants; only one SAE in each group was potentially related to treatment.
Expert Commentary
The robust Treg expansion confirms that low-dose IL-2 effectively modulates the immune system in early T1D, but the failure to demonstrate β-cell preservation underscores the complexity of the autoimmune process at diagnosis. The intense inflammatory milieu present early in disease may require combination immunotherapies or earlier intervention to achieve clinically meaningful efficacy.
The DIABIL-2 findings align with a growing understanding that monotherapy with immunomodulators may be insufficient to halt β-cell loss once established autoimmunity is active. This trial highlights the safety of low-dose IL-2 and its biological capacity to expand Tregs, thereby providing a rationale for future research evaluating IL-2 in preventive settings (e.g., before clinical onset) or combined with agents targeting other immune pathways.
Limitations include the heterogeneity in patient age and disease stage, and the 12-month follow-up may not fully capture long-term preservation potential. Further studies with larger samples and extended follow-up are warranted.
Conclusion
The DIABIL-2 phase 2b trial demonstrated that while low-dose IL-2 safely induces selective Treg expansion in patients with newly diagnosed type 1 diabetes, it does not preserve residual pancreatic β-cell function at one year. These results suggest that low-dose IL-2 monotherapy is insufficient for modifying clinical disease progression in recent-onset T1D. Nevertheless, the favorable safety profile and confirmed immunological activity support further exploration of IL-2-based therapies at earlier disease stages or as combination regimens aiming to restore immune tolerance and preserve endogenous insulin secretion.
Funding and Registration
This study was funded by Assistance Publique-Hôpitaux de Paris (European Research Network), ILTOO Pharma, and the Investissements d’Avenir programme. The trial is registered at ClinicalTrials.gov under NCT02411253 (completed).
References
1. Rosenzwajg M, Hartemann A, Halbron M, et al. Efficacy and safety of low-dose IL-2 in people with newly diagnosed type 1 diabetes (DIABIL-2): a double-blind, multicentre, randomised, placebo-controlled, phase 2b trial. Lancet Diabetes Endocrinol. 2026 Oct 1.
2. Long SA, Buckner JH. CD4+FOXP3+ T regulatory cells in human autoimmunity: more than a numbers game. J Immunol. 2011.
3. von Herrath M, et al. Immunological intervention in type 1 diabetes: from bench to bedside. Nat Rev Immunol. 2021.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.