Highlight
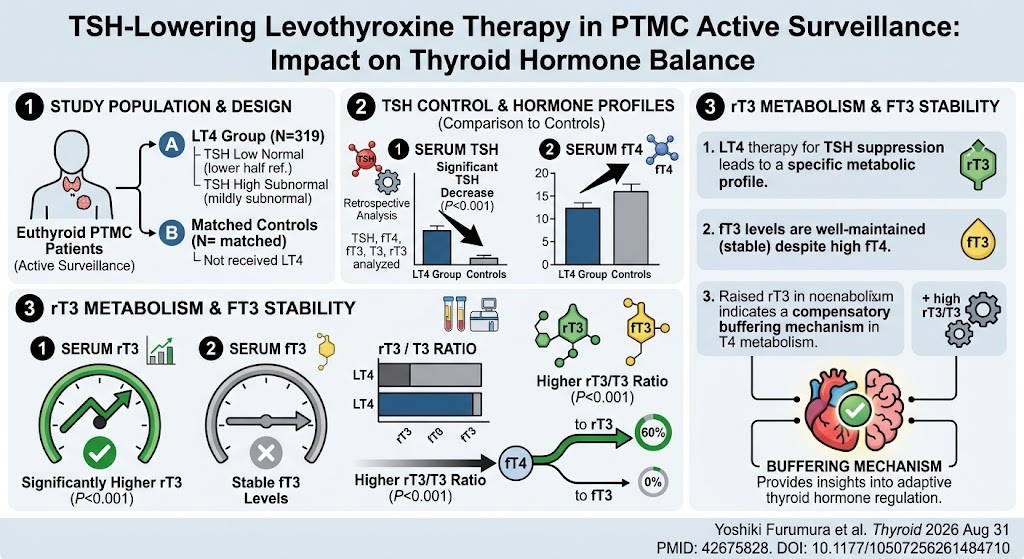
- Levothyroxine therapy aimed at lowering TSH within low normal or mildly suppressed ranges elevates serum free T4 and reverse T3 levels in euthyroid patients with papillary thyroid microcarcinoma (PTMC) undergoing active surveillance.
- Despite higher free T4, free T3 levels remain stable, resulting in a reduced fT3/fT4 ratio, indicating altered peripheral thyroid hormone metabolism.
- Elevated reverse T3 correlates positively with free T4, supporting the presence of a compensatory buffering mechanism in thyroid hormone regulation under mild TSH suppression.
Study Background
Papillary thyroid microcarcinoma (PTMC) is a subset of differentiated thyroid cancer characterized by tumors ≤1 cm in size that often exhibit indolent behavior. Active surveillance (AS) has emerged as a management strategy to monitor low-risk PTMC rather than immediate surgery, aiming to minimize overtreatment and related morbidity. Given the role of thyroid-stimulating hormone (TSH) in tumor biology, TSH suppression with levothyroxine (LT4) is frequently employed to reduce disease progression risk. However, in euthyroid patients, mild TSH-lowering therapy’s effects on thyroid hormone metabolism dynamics—particularly regarding T4 conversion to active and inactive forms—are not fully elucidated. Initial observations indicated a rise in free thyroxine (fT4) without concomitant elevation in free triiodothyronine (fT3), raising questions about peripheral deiodinase activities and thyroid hormone homeostasis under LT4 therapy during AS.
Study Design
This retrospective analysis involved euthyroid patients diagnosed with PTMC undergoing AS who received levothyroxine therapy intended to mildly lower TSH. Patients were stratified into groups based on their TSH levels at final follow-up: a low normal group (TSH in the lower half of the reference range) and a high subnormal group (TSH mildly below the reference range). Age- and sex-matched euthyroid PTMC patients under AS without LT4 therapy served as controls. Serum TSH, free T4, free T3, total T3, and reverse T3 (rT3) concentrations were assayed, with immunoassays employed for TSH, fT4, and fT3, and liquid chromatography-tandem mass spectrometry utilized for T3 and rT3 measurements. The study examined intergroup hormone levels and correlations to elucidate the impact of mild TSH suppression on thyroid hormone metabolism.
Key Findings
Both the low normal and high subnormal TSH groups demonstrated significantly elevated serum free T4 levels compared to matched controls (p < 0.001), reflecting the pharmacologic effect of LT4 therapy. Contrary to expectations, free T3 concentrations remained statistically unchanged, resulting in a significantly decreased fT3/fT4 ratio (p < 0.001). Notably, the concentrations of reverse T3 and the rT3/T3 ratio were significantly higher in both LT4 groups compared to controls (p < 0.001). Correlation analysis combining the LT4-treated groups revealed a strong positive association between free T4 and reverse T3 levels (r = 0.51, p < 0.001), while no significant correlations emerged between reverse T3 and TSH, free T3, or total T3.
These findings suggest that mild TSH suppression via LT4 in euthyroid PTMC patients shifts peripheral thyroid hormone metabolism towards increased conversion of T4 to the inactive rT3 rather than active T3. This metabolic adaptation maintains stable circulating active thyroid hormone (fT3) despite elevated substrate (fT4) availability, potentially preventing excessive thyroid hormone action and preserving euthyroidism.
Expert Commentary
This study offers insightful mechanistic clarity on thyroid hormone metabolism under mild TSH-lowering LT4 therapy in a unique patient population. The observed increase in reverse T3—a metabolite generated predominantly by type 3 deiodinase inactivating T4 and T3—supports a buffering or protective mechanism against thyroid hormone excess. Maintaining stable free T3 despite raised free T4 is physiologically consistent with the body’s need to avoid thyrotoxic states. Clinically, this phenomenon underscores the complexity of managing thyroid hormone levels and TSH suppression in PTMC patients under AS, emphasizing that monitoring only TSH and free T4 may not reflect the complete picture of hormone action.
Limitations include the retrospective design and potential confounding factors such as variable LT4 dosages and individual deiodinase activity variability. The applicability of these findings to other thyroid cancer subtypes or surgical cohorts requires further exploration. Future prospective studies with longitudinal hormone profiling and clinical outcome correlations could elucidate whether elevated rT3 influences tumor behavior or metabolic status.
Conclusion
In euthyroid patients with papillary thyroid microcarcinoma undergoing active surveillance, mild TSH suppression with levothyroxine therapy is associated with elevated serum free T4 and reverse T3 levels while maintaining stable free T3 concentrations. This shift suggests a compensatory metabolic adaptation in peripheral thyroid hormone metabolism, likely mediated by increased conversion of T4 to inactive reverse T3, which may buffer against thyroid hormone excess in this delicate therapeutic context. These findings have implications for optimizing TSH suppression strategies and monitoring in PTMC management and highlight the importance of comprehensive thyroid hormone assessment beyond TSH and free T4 alone.
Funding and Clinical Trials
The original publication did not specify funding sources or clinical trial registration details relevant to this retrospective analysis.
References
1. Furumura Y, Miyauchi A, Ito M, et al. TSH-Lowering Levothyroxine Therapy Is Associated with Higher rT3 and Stable fT3 Levels in Euthyroid Patients with Papillary Thyroid Microcarcinoma During Active Surveillance. Thyroid. 2026 Aug 31; [Epub ahead of print]. doi:10.1089/thy.2026.0148.
2. McAninch EA, Bianco AC. Thyroid hormone signaling in the nucleus. Nat Rev Endocrinol. 2014;10(2):111-121.
3. Jonklaas J, Bianco AC, Bauer AJ, et al. Guidelines for the use of thyroid hormone therapy in adults: an Endocrine Society clinical practice guideline. J Clin Endocrinol Metab. 2014;99(2):356-364.
4. Ito Y, Miyauchi A. Active Surveillance as a Management Strategy for Papillary Microcarcinoma of the Thyroid. World J Surg. 2017;41(1):6-15.