Intranasal vs. Subcutaneous Ketamine for Acute Traumatic Pain in the ED: Comparable Efficacy and Safety
Highlight
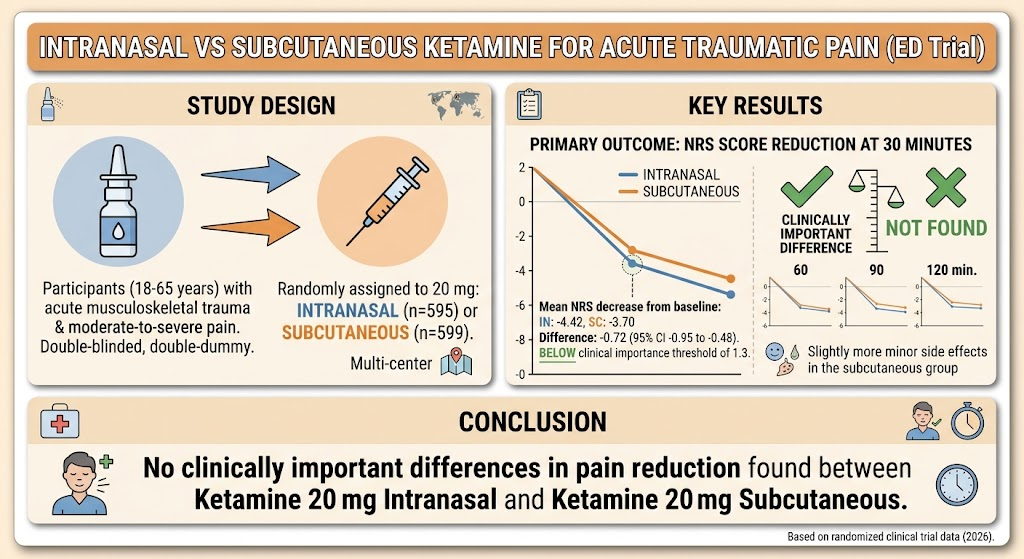
This randomized, double-blinded, double-dummy clinical trial compared the analgesic efficacy and safety profile of intranasal versus subcutaneous ketamine 20 mg in adults presenting with acute musculoskeletal trauma in the emergency department. Both routes achieved significant pain reduction at 30 minutes and beyond, with intranasal ketamine demonstrating a marginally greater mean reduction in numerical rating scale (NRS) pain scores, though differences were below the threshold for clinical importance. Secondary outcomes and adverse events profiles were largely similar, except for a higher incidence of minor adverse events in the subcutaneous group.
Study Background
Acute musculoskeletal trauma frequently presents to emergency departments (ED) and often results in moderate to severe pain requiring prompt and effective analgesia. While opioids remain a cornerstone of pain management, concerns regarding side effects, dependency, and the opioid crisis have intensified the search for alternative analgesics. Ketamine, a N-methyl-D-aspartate (NMDA) receptor antagonist, is increasingly utilized in subanesthetic doses for analgesia due to its favorable respiratory and hemodynamic profiles. Subcutaneous ketamine administration is effective but may be limited by invasive injection and associated pain or risk of infection. Intranasal ketamine offers a noninvasive alternative with rapid onset and ease of administration. However, comparative effectiveness and safety data in acute traumatic pain scenarios remain limited, warranting robust investigation.
Study Design
This investigation was a randomized, double-blinded, double-dummy, prospective clinical trial enrolling adult patients aged 18 to 65 years presenting to the ED with acute musculoskeletal trauma and moderate to severe pain. Participants were randomized to receive either 20 mg ketamine subcutaneously or 20 mg ketamine intranasally. The double-dummy design ensured all patients received both an injection and nasal spray, with one being active drug and the other placebo to maintain blinding. The primary endpoint was the change in the numerical rating scale (NRS) pain score at 30 minutes post-administration. Secondary endpoints included pain scores at 5, 10, 15, 60, 90, and 120 minutes, the proportion of patients achieving NRS <3 at protocol end, adverse event incidence, and the requirement for additional analgesic medication.
Key Findings and Results
A total of 1,194 patients were enrolled, with 599 assigned to subcutaneous ketamine and 595 to intranasal ketamine groups. Baseline pain scores were comparable between groups.
At 30 minutes, mean NRS pain score reductions from baseline were:
- Subcutaneous group: -3.70 (SD 1.88)
- Intranasal group: -4.42 (SD 2.15)
The between-group mean difference was -0.72 (95% CI: -0.95 to -0.48; p<0.001), indicating a statistically significant but clinically modest benefit favoring intranasal ketamine. Importantly, this difference was below the minimally clinically important difference (MCID) of 1.3 NRS points, suggesting comparable clinical efficacy.
Similar trends were observed across other time points, consistently showing slightly greater pain reduction with intranasal administration but without crossing the threshold for clinical relevance. The proportion of patients achieving effective analgesia (NRS <3) at study conclusion did not differ significantly between groups.
Regarding safety, the subcutaneous group experienced a higher frequency of minor adverse events, such as transient injection site discomfort, mild dizziness, and nausea, compared to the intranasal group. No serious adverse events or hemodynamic instability were reported. The need for rescue analgesics was similar between the two groups.
Expert Commentary
This well-powered, methodologically rigorous trial adds valuable comparative data on ketamine’s routes of administration for acute pain in ED settings. The double-dummy design enhances confidence in blinding and reduces bias. While intranasal ketamine showed statistically significant superiority in pain reduction, the difference did not reach the MCID, suggesting that both routes are clinically interchangeable.
Intranasal ketamine offers logistical advantages including ease of administration, avoidance of needle-associated discomfort or complications, and potential for use in resource-limited or prehospital settings. The slightly more favorable adverse event profile further supports its utility. However, patient-specific factors such as nasal mucosa conditions, volume limitations, or anatomical challenges may limit intranasal delivery at times.
The study primarily focused on otherwise healthy adults with isolated musculoskeletal trauma. Generalizability to geriatric patients, those with polytrauma, or other comorbidities remains to be explored. Additionally, dose optimization beyond fixed 20 mg administration and cost-effectiveness analyses are warranted in future investigations.
Conclusion
In adult emergency department patients with acute musculoskeletal trauma, 20 mg ketamine administered either intranasally or subcutaneously provides effective and rapid analgesia, with no clinically meaningful difference in pain reduction at 30 minutes or up to 2 hours observed during this trial. Intranasal ketamine showed fewer minor adverse events and represents a convenient, noninvasive alternative suitable for ED and potentially prehospital use. These findings support incorporating intranasal ketamine as a frontline analgesic option in suitable clinical scenarios.
Funding and ClinicalTrials.gov
The study was published in the Annals of Emergency Medicine in October 2025. Specific funding sources or clinical trial registration details were not disclosed in the provided abstract.
References
1. Dhaoui R, Kouraichi C, Toumia M, Haj Ali KB, Sekma A, Jaballah R, Yaakoubi H, Boukadida L, Beltaief K, Mezgar Z, Khrouf M, Sghaier A, Jerbi N, Zemni I, Bouida W, Grissa MH, Saad J, Boubaker H, Boukef R, Msolli MA, Nouira S. Intranasal Versus Subcutaneous Ketamine for the Treatment of Acute Traumatic Pain in the Emergency Department: A Randomized Clinical Trial. Ann Emerg Med. 2026 Sep;88(3):314-320. doi: 10.1016/j.annemergmed.2025.09.019. Epub 2025 Oct 18. PMID: 41108307.
2. Schwenk ES, Viscusi ER, Buvanendran A, et al. Consensus Guidelines on the Use of Intravenous Ketamine Infusions for Acute Pain Management from the American Society of Regional Anesthesia and Pain Medicine, the American Academy of Pain Medicine, and American Society of Anesthesiologists. Reg Anesth Pain Med. 2018;43(5):456-466.
3. Yeaman F, Guerin C, Somogyi AA. Ketamine in acute pain management: An overview for the emergency physician. Emerg Med Australas. 2021;33(1):5-14.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.