Impact of Primary Melanoma Stage on Survival Outcomes in Advanced Disease: Insights from the Spanish Melanoma Registry GEM1801
Highlight
- Systemic relapse after stage I melanoma, while uncommon, accounts for nearly one-third of metastatic melanoma cases.
- Patients with metastatic relapse from prior stage I melanoma have higher tumor burden, including more metastatic sites and brain involvement.
- Median overall survival (OS) is significantly shorter in patients with prior stage I melanoma compared to those relapsing from stages IIA, IIB/C or III.
Study Background
Melanoma is a malignancy arising from melanocytes and is known for its heterogeneous clinical behavior. Early-stage melanoma (stage I) generally carries a favorable prognosis, with systemic relapse being relatively rare. However, patients who do experience metastatic progression after early-stage disease contribute substantially to the metastatic melanoma burden. Understanding prognostic factors influencing survival in advanced melanoma is critical for guiding surveillance, counseling, and therapeutic strategies.
The prognostic significance of the primary melanoma stage at initial diagnosis in the context of advanced metastatic disease remains poorly characterized. Historically, later-stage melanoma (e.g., stage III) is associated with higher risk of relapse and aggressive disease. The current study from the Spanish Melanoma Registry GEM1801 addresses this knowledge gap by evaluating survival outcomes and tumor characteristics in metastatic melanoma patients stratified by their primary tumor stage.
Study Design
This retrospective cohort study analyzed data collected from the Spanish Melanoma Registry (2018-2024), comprising 365 patients with metastatic melanoma who received first-line systemic treatment. Patients were stratified according to their primary melanoma stage at diagnosis: stage I (n=58), IIA (n=32), IIB/C (n=80), and stage III (n=195). The primary endpoint was overall survival (OS) after systemic relapse. Secondary endpoints included time to relapse, metastatic burden (number of metastatic sites), presence of brain metastases, and serum lactate dehydrogenase (LDH) levels as a biomarker of tumor burden and aggressiveness.
Key Findings
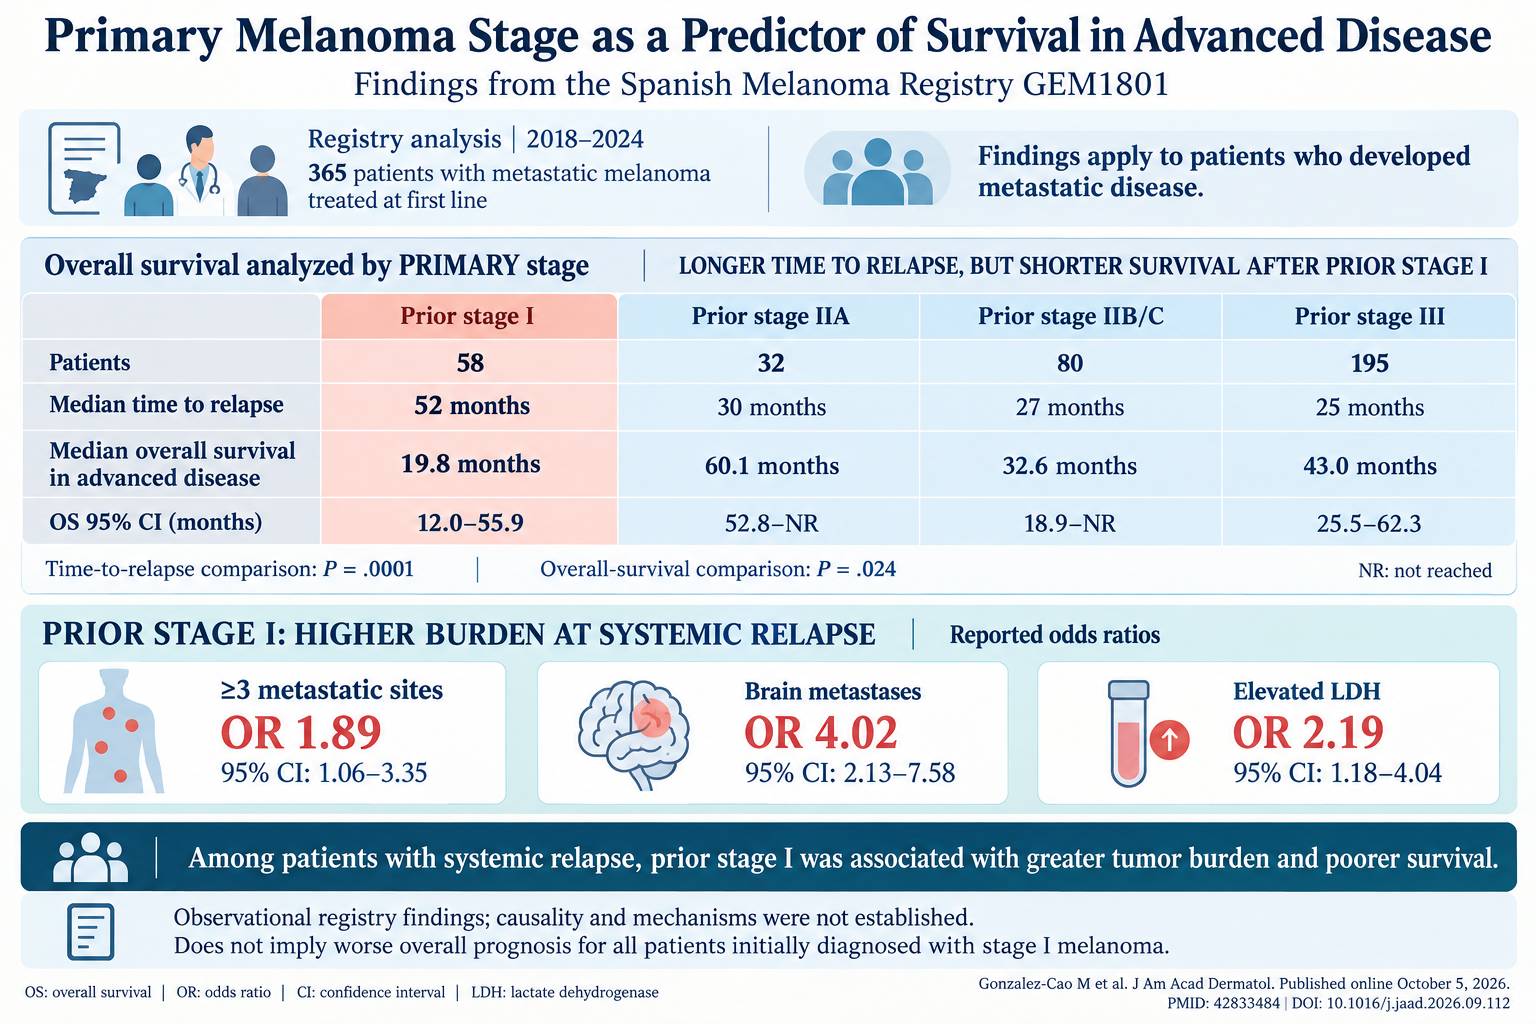
Time to Relapse: Median time to systemic relapse differed significantly by initial stage. Patients with stage I primary melanoma relapsed after a median of 52 months, considerably longer than patients with stages IIA (30 months), IIB/C (27 months), and III (25 months) (p=0.0001). This finding confirms the generally indolent nature of early-stage melanoma before systemic progression.
Tumor Burden at Relapse: Despite longer relapse-free intervals, patients with previous stage I disease presented with notably greater metastatic burden at relapse. They were more likely to have three or more metastatic sites (OR 1.89; 95% CI 1.06–3.35), brain metastases (OR 4.02; 95% CI 2.13–7.58), and elevated serum LDH levels (OR 2.19; 95% CI 1.18–4.04) compared to other stage groups. These factors are clinically recognized markers of advanced disease and poor prognosis.
Overall Survival: Median OS following systemic relapse was shortest for the prior stage I group at 19.8 months (95% CI, 12 to 55.9), compared to 60.1 months (95% CI, 52.8 to not reached) for stage IIA, 32.6 months (95% CI, 18.9 to not reached) for IIB/C, and 43 months (95% CI, 25.5 to 62.3) for stage III patients (p=0.024). These data highlight a paradox wherein early-stage primary melanoma patients, despite delayed relapse, experience more aggressive metastatic disease and worse survival outcomes than those with higher stage initial tumors.
Expert Commentary
The study’s findings challenge the conventional prognostic assumptions based solely on initial melanoma staging. The higher tumor burden and poorer survival after relapse from stage I melanoma may reflect biological differences in tumor evolution or delayed diagnosis of metastatic spread due to prolonged dormancy. The overrepresentation of brain metastases is particularly concerning given their association with rapid clinical deterioration.
Clinicians should be aware that patients presenting with systemic relapse after early-stage melanoma might require more aggressive evaluation and possibly earlier initiation of systemic therapies targeted at high-risk features, including central nervous system involvement and elevated LDH. Moreover, these results emphasize the need for ongoing surveillance strategies tailored to detect metastatic spread even in patients initially diagnosed with stage I disease.
Limitations include the observational nature of registry data and potential confounders such as variations in treatment regimens and adherence to surveillance protocols. Future prospective studies incorporating molecular profiling may elucidate mechanisms underpinning aggressive progression after early-stage melanoma.
Conclusion
This study from the Spanish Melanoma Registry GEM1801 establishes that systemic relapse after stage I melanoma is associated with a higher metastatic tumor burden, increased brain metastases, elevated LDH, and significantly reduced overall survival compared with relapse after stage II or III disease. These insights necessitate reconsideration of follow-up and management strategies in early-stage melanoma patients to improve outcomes after metastatic progression.
Funding and Clinical Trials
Funding sources and clinical trial registrations related to this study were not specified within the abstract. Further details may be obtained from the primary publication or the Spanish Melanoma Group.
References
Gonzalez-Cao M, Puig S, Manzano JL, et al. Primary Melanoma Stage as a Predictor of Survival in Advanced Disease: Findings from the Spanish Melanoma Registry GEM1801. J Am Acad Dermatol. 2026 Oct 05. PMID: 42833484.
Summary references:
1. Gershenwald JE, Scolyer RA, Hess KR, et al. Melanoma staging: Evidence-based changes in the American Joint Committee on Cancer eighth edition cancer staging manual. CA Cancer J Clin. 2017;67(6):472-492.
2. Eggermont AMM, Spatz A, Robert C. Cutaneous melanoma. Lancet. 2014;383(9919):816-827.
3. Long GV, Weber JS, Infante JR, et al. Role of LDH as a prognostic biomarker in melanoma patients treated with immunotherapy. Cancer Immunol Immunother. 2020;69(6):1125-1133.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.