Highlight
This large retrospective cohort study of over five million US births from 2015 to 2022 documents significant hospital-level variation in the use of antenatal corticosteroids for late preterm births. Despite evidence from the ALPS trial supporting steroid use to reduce neonatal respiratory complications, administration rates ranged widely from 0% to 92% across hospitals. Urban location and regional differences, particularly lower adoption in Southern hospitals, were independently associated with uptake, underscoring disparities in evidence-based practice implementation.
Study Background
Late preterm birth, defined as delivery between 34 and 36 completed weeks of gestation, constitutes a substantial proportion of preterm deliveries and is associated with increased risks of neonatal respiratory morbidity and other complications compared with term births. The Antenatal Late Preterm Steroids (ALPS) trial demonstrated that administering antenatal corticosteroids such as betamethasone before late preterm delivery can significantly decrease neonatal respiratory complications, including respiratory distress syndrome and transient tachypnea of the newborn. Following the ALPS trial publication, professional guidelines recommended antenatal corticosteroid use for appropriately selected late preterm births to improve neonatal outcomes.
Despite clear evidence, clinical adoption of late preterm steroids has reportedly been inconsistent. Understanding the extent and determinants of hospital-level variation in corticosteroid use is critical to identifying implementation barriers and promoting widespread evidence-based care to improve neonatal health outcomes.
Study Design
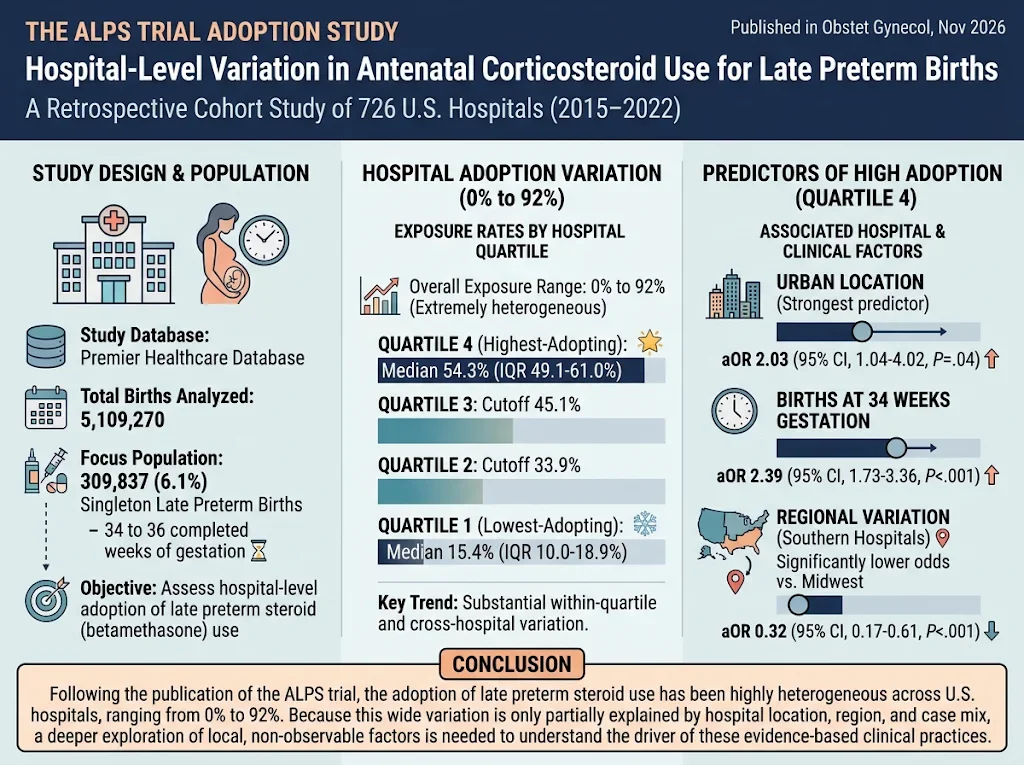
This retrospective cohort study leveraged data from the Premier Healthcare Database, encompassing 726 US hospitals and 5,109,270 births collected between 2015 and 2022. The study population included singleton late preterm births (34–36 weeks gestation) with known gestational ages. The primary variable of interest was the hospital-level adoption rate of antenatal corticosteroid administration, defined by the proportion of late preterm singleton births receiving betamethasone during the late preterm period.
Hospitals were ranked by adoption rates and categorized into quartiles based on their empirical distribution. Temporal trends in adoption rates were analyzed annually and visualized via time series and distribution plots. A multivariable logistic regression model evaluated hospital characteristics associated with high adoption rates, focusing on facility location (urban vs. rural), US Census region, and clinical case mix variables such as the proportion of births at 34 weeks gestation.
Key Findings
The cohort included 309,837 late preterm singleton births (6.1% of total births). Hospital-level corticosteroid administration rates exhibited wide variability, ranging from 0% to 92%. Quartile categorization of hospitals based on overall exposure rates yielded cutoffs at 22.4%, 33.9%, and 45.1%. Median exposure rates within quartiles exhibited a gradient from 15.4% (interquartile range [IQR] 10.0–18.9%) in the lowest adopters (quartile 1) to 54.3% (IQR 49.1–61.0%) in the highest adopters (quartile 4), with notable variability observed even within quartiles.
Multivariable logistic regression identified urban hospital location as a strong independent predictor of high corticosteroid adoption (adjusted odds ratio [aOR] 2.03; 95% confidence interval [CI], 1.04–4.02; P=.04). Regionally, hospitals in the Southern United States were significantly less likely to be high adopters relative to Midwestern hospitals (aOR 0.32; 95% CI, 0.17–0.61; P<.001). Among clinical variables, a higher proportion of late preterm births occurring at 34 weeks gestation was strongly associated with high adoption (aOR 2.39; 95% CI, 1.73–3.36; P<.001).
Temporal analysis suggested an overall increase in corticosteroid use for late preterm births over the studied years, consistent with guidelines evolution post-ALPS trial, but adoption remained heterogeneous across hospitals without uniform practice change.
Expert Commentary
The observed heterogeneity underscores the complex interplay between evidence dissemination, institutional protocols, provider beliefs, and regional healthcare infrastructure. Urban center hospitals may have greater access to subspecialty care, perinatal protocols, and quality improvement resources facilitating adoption of evidence-based interventions such as antenatal corticosteroids for late preterm births.
Conversely, lower adoption in the South may reflect regional disparities in healthcare delivery, resource availability, or differences in guideline uptake. The association of higher early late preterm births (34 weeks) with greater adoption likely relates to increased clinical perception of neonatal risk prompting steroid use at the earliest late preterm gestational ages.
These findings resonate with literature documenting variable implementation of perinatal interventions and emphasize the need for targeted strategies, including provider education, standardized protocols, and equitable resource allocation to improve care consistency.
Study limitations include its retrospective design and reliance on administrative data that may lack granular clinical factors affecting steroid use. The inability to capture provider-level decision-making and patient preferences also limits interpretability. Nevertheless, the large sample size and broad hospital representation enhance generalizability.
Conclusion
After the pivotal ALPS trial and subsequent guideline endorsements, adoption of antenatal corticosteroids for late preterm singleton births varied substantially across US hospitals. Urban hospital location and geographic region were significant predictors of adoption, highlighting disparities in implementation of evidence-based neonatal care. These findings unveil critical gaps and argue for further research into local barriers and facilitators to guideline adoption, aiming for equitable and universal delivery of proven interventions to reduce neonatal morbidity in late preterm infants.
Efforts to standardize care pathways, integrate clinical decision support systems, and foster provider and patient education are essential to bridge the practice gap. Ongoing monitoring of corticosteroid use and evaluation of neonatal outcomes linked to practice patterns can guide quality improvement initiatives ultimately improving perinatal healthcare quality nationwide.
Funding and Clinical Trial Registration
The study was conducted using the Premier Healthcare Database and did not receive external funding. The analysis adhered to ethical standards for secondary research. The ALPS trial, which forms the evidence base for corticosteroid use in late preterm birth, was registered (ClinicalTrials.gov Identifier: NCT01866925).
References
Clapp MA, Lee D, Li S, James KE, Lorch SA, Cohen JL, Wright JD, Gyamfi-Bannerman C, Kaimal AJ, Melamed A. Hospital-Level Variation in Antenatal Corticosteroid Use for Late Preterm Births. Obstet Gynecol. 2026 Nov 10. doi: 10.1097/AOG.0000000000006467. Epub ahead of print. PMID: 43008238.
American College of Obstetricians and Gynecologists. Practice Bulletin No. 172: Prematurity. Obstet Gynecol. 2016;128(4):e155-e164.
Committee on Obstetric Practice. Committee Opinion No. 713: Antenatal Corticosteroid Therapy for Fetal Maturation. Obstet Gynecol. 2017;130(2):e102-e109.
Escobar GJ, Zupancic JA, Armstrong MA, et al. A Model Predicting Respiratory Morbidity in Late Preterm Infants. Pediatrics. 2006;118(1):e104-e111. doi:10.1542/peds.2005-2031