Highlight
- Posterior rectus sheath flap (PoRSHA) offers a vascularized autologous tissue option for hiatal augmentation in complex paraesophageal hernia repairs.
- After procedural maturation, estimated radiologic recurrence rates were low (9.2% at 24-36 months) with stable results at midterm follow-up.
- Recurrences were small and did not necessitate reoperation, indicating promising durability compared to traditional reinforcement techniques.
- Donor-site morbidity was infrequent, supporting the safety of this autologous tissue approach.
Study Background
Complex paraesophageal hernia repair remains clinically challenging due to high risk of recurrence and morbidity. Traditional surgical strategies often involve primary crural repair or synthetic mesh reinforcement, but these approaches have limitations including mesh-related complications and inconsistent long-term durability. Structural weakness of the diaphragmatic crura, which form the hiatal ring, contribute significantly to hernia recurrence. There is thus an unmet clinical need for durable reinforcement strategies that balance efficacy and safety.
The posterior rectus sheath flap (PoRSHA) represents a vascularized autologous tissue reinforcement technique aimed at augmenting the hiatal closure. This technique leverages the patient’s own connective tissue with preserved blood supply to improve healing and durability without introducing synthetic materials that may provoke adverse reactions. Early Phase 2a IDEAL framework studies demonstrated feasibility and encouraging short-term outcomes with PoRSHA, driving further investigation into its procedural maturation and midterm durability.
Study Design
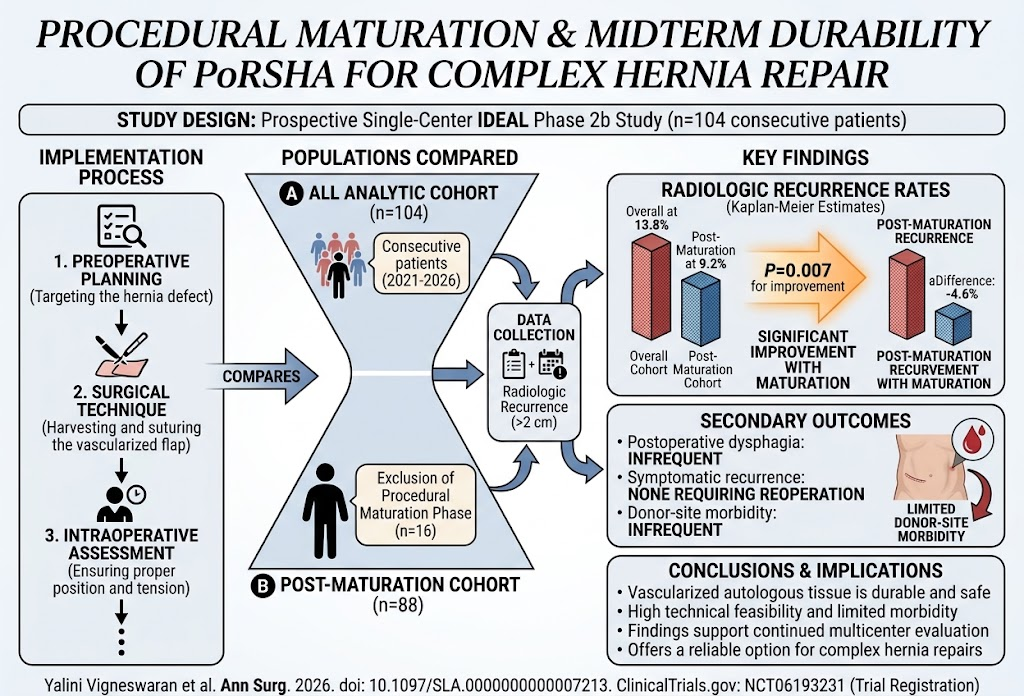
This investigation was a prospective single-center IDEAL Phase 2b study conducted over five years (2021–2026), including 104 consecutive patients undergoing PoRSHA for complex paraesophageal hernia repair. The analytic cohort consisted of 94 patients with either primary large type III/IV (n=71) or recurrent paraesophageal hernias (n=23).
Radiologic recurrence was defined as >2 cm hernia recurrence assessed by imaging and analyzed using Kaplan-Meier methodology to account for variable follow-up duration. Secondary endpoints included symptomatic recurrence requiring surgical reoperation, postoperative dysphagia, and donor-site morbidity related to the flap harvest.
Key Findings
The overall estimated radiologic recurrence rate was low at 1.4% at 12 months and increased modestly to 13.8% at 24 months with confidence interval (CI) spanning 5.7% to 31.3%. Notably, recurrence rates stabilized thereafter, with an 18.1% recurrence rate maintained through 48 months.
Importantly, when excluding the initial procedural maturation phase (patients n=16), the estimated recurrence rate improved significantly to 9.2% at 24 and 36 months (95% CI, 2.9%-27.4%) with no further recurrences during extended follow-up. This indicates a learning curve impact, where outcomes improve as surgical technique and perioperative management mature.
All identified recurrences were small in size and did not require reoperation, reflecting a clinical relevance where radiologic recurrence did not translate into symptomatic or reoperative failure.
Donor-site morbidity was infrequent, affirming the relative safety profile of harvesting the posterior rectus sheath flap. There were no major complications reported related to the autologous tissue harvest.
Expert Commentary
These findings substantiate the role of PoRSHA as a promising vascularized autologous tissue approach to reinforce the hiatal repair in complex paraesophageal hernias. The improved outcomes post-maturation phase highlight the crucial importance of surgical expertise and experience in optimizing procedural efficacy. The ability of PoRSHA to maintain durable repair without mesh-associated complications addresses a key limitation of synthetic reinforcement techniques.
However, the study is limited by its single-center design and lack of a direct randomized comparator arm with standard techniques. Also, midterm follow-up (up to 4 years) is encouraging but longer-term data are needed to establish sustained durability. Multicenter studies with randomized controlled designs would be critical to validate these findings and clarify patient selection criteria.
Mechanistically, the vascularized nature of the flap may promote enhanced healing and resistance to mechanical failure compared to nonvascularized or synthetic patches. This biological plausibility supports further clinical adoption and research.
Conclusion
Following a procedural learning curve, PoRSHA demonstrates favorable midterm durability, low recurrence rates, and limited donor-site morbidity in complex paraesophageal hernia repair. These encouraging outcomes provide justification for broader multicenter evaluation of vascularized autologous hiatal augmentation techniques. If validated in larger trials, PoRSHA could represent a paradigm shift toward safer and more durable repair strategies, improving long-term patient outcomes.
Funding and Clinical Trials
Details on specific funding sources were not disclosed in the provided abstract. The study was conducted under the IDEAL framework (Phase 2b), indicating a structured clinical investigation process for surgical innovation.
References
1. Vigneswaran Y, Campbell M, Lois AW, Gottlieb LJ, Hussain M. Procedural Maturation and Midterm Durability of the Posterior Rectus Sheath Flap for Hiatal Augmentation in Complex Paraesophageal Hernias. Ann Surg. 2026 Sep 4. PMID: 42693496.
2. Oelschlager BK, Pellegrini CA, Hunter JG. Surgical Treatment of Large Paraesophageal Hernia. JAMA Surg. 2021;156(11):1041-1042.
3. Frantzides CT, Carlson MA. High recurrence rate after laparoscopic repair of paraesophageal hernias using biologic mesh: a review of the literature. Surg Endosc. 2012 Jun;26(6):1404-14.