Highlight
- Combined intrahepatic and periduodenal lymphatic embolization markedly improves protein-losing enteropathy (PLE) remission rates and duration in congenital heart disease (CHD) patients compared to intrahepatic embolization alone.
- Multicompartment magnetic resonance lymphangiography enables detection of duodenal lymphatic leaks, facilitating targeted embolization strategies.
- Thoracic duct obstruction portends shorter remission durations and remains a critical factor in post-procedural outcomes.
- Although adverse events such as transient pancreatitis and hyperbilirubinemia are common, serious complications are similar between embolization approaches, supporting the safety of combined strategies in a high-risk population.
Background
Protein-losing enteropathy (PLE) is a severe and challenging complication in patients with congenital heart disease (CHD), particularly in those who have undergone palliative surgeries such as the Fontan procedure. Characterized by excessive loss of plasma proteins into the gastrointestinal tract, PLE leads to hypoalbuminemia, edema, immunodeficiency, and poor clinical prognosis. Historically, treatments have focused on symptomatic management rather than definitive, targeted interventions, resulting in limited success and high morbidity.
Emerging evidence indicates that abnormal lymphatic connections, including hepatic and extrahepatic lymphatic channels, contribute substantially to PLE pathogenesis. However, earlier embolization therapies aimed predominantly at intrahepatic (IH) lymphatic abnormalities yielded variable outcomes and lacked robust long-term efficacy data. The advent of advanced imaging, specifically multicompartment magnetic resonance lymphangiography (MRL), has enhanced the understanding of lymphatic architecture and leak sites, uncovering abnormalities such as periduodenal (PD) leaks.
Against this background, the study by Smith et al. addresses critical unmet needs by systematically evaluating whether a comprehensive embolization approach targeting both intrahepatic and periduodenal lymphatic pathways improves patient outcomes compared to intrahepatic embolization alone in CHD-related PLE.
Study Design
This retrospective, single-center cohort study included 71 patients with CHD and medically refractory PLE who underwent percutaneous lymphatic embolization. Patient evaluation included multicompartment MRL to delineate lymphatic abnormalities and localize lymphatic leaks. Patients were allocated to one of two embolization strategies based on imaging findings and clinical decision-making:
- Isolated intrahepatic (IH) embolization (n=17)
- Combined intrahepatic and periduodenal (IH + PD) embolization (n=54)
The primary endpoint was duration of remission, defined as sustained serum albumin ≥3.0 g/dL without intravenous albumin supplementation or additional PLE interventions. Secondary endpoints comprised initial response rate (albumin ≥3.0 g/dL within 30 days post-procedure without IV supplementation), effects of thoracic duct obstruction on remission, transplant-free survival, and safety outcomes.
Key Findings
Lymphatic Imaging and Leak Detection
Multicompartment MRL identified duodenal lymphatic leaks in all patients, emphasizing the pervasive involvement of periduodenal lymphatics in PLE pathophysiology. This finding underpinned the rationale for targeting both IH and PD compartments.
Clinical Response
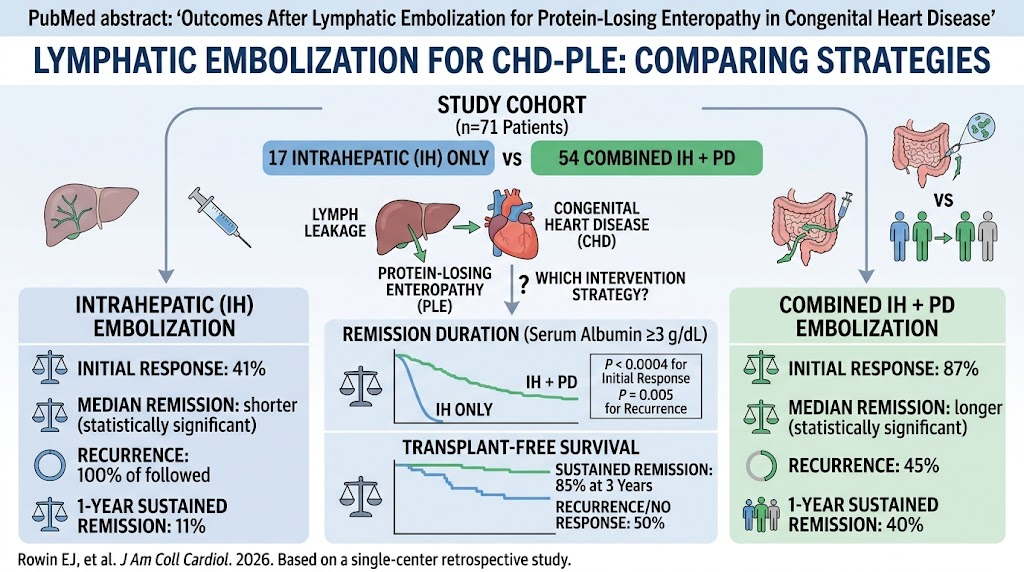
The IH + PD embolization group demonstrated a significantly higher initial response rate than the IH group (87% vs 41%; P < 0.0004). Post-procedural median serum albumin rose substantially from 2.3 g/dL to 4.2 g/dL in the IH + PD cohort (P < 0.0001), reflecting improved protein retention.
Duration and Sustainability of Remission
Recurrence of PLE was notably lower in the combined embolization group (45%) compared to the IH-only group (100%) over the follow-up period (P = 0.005). Sustained remission lasting at least one year was achieved in 40% of IH + PD patients versus only 11% of IH-only patients (P = 0.04). These data suggest durable benefit attributable to inclusion of periduodenal embolization.
Impact of Thoracic Duct Obstruction
Thoracic duct obstruction emerged as an adverse prognostic indicator, correlating with significantly shorter remission durations (P = 0.0005). This highlights the importance of assessing thoracic duct patency during pre-procedure evaluation and potentially tailoring interventions accordingly.
Transplant-Free Survival
Exploratory analysis revealed patients sustaining remission had markedly greater transplant-free survival rates at 3 years post-procedure compared to those with recurrence or no response (85% vs 50%; P = 0.003), underscoring the clinical relevance of inducing and maintaining remission.
Safety Profile
Adverse events were frequent but generally self-limited or manageable. Transient pancreatitis occurred in 75%, and 40% experienced hyperbilirubinemia post-procedure. Importantly, rates of serious and catastrophic events were comparable between IH and IH + PD groups, indicating that adding periduodenal embolization does not increase major procedural risk in this fragile population.
Expert Commentary
This study provides compelling evidence supporting a broader and more targeted therapeutic approach to lymphatic embolization in CHD-related PLE. The universal detection of periduodenal leaks via advanced MRL challenges the traditional paradigm focusing exclusively on intrahepatic lymphatics and suggests a pathogenic role for extrahepatic lymphatic channels.
From a mechanistic standpoint, embolizing both IH and PD compartments likely addresses multifocal lymphatic leakage sources, reducing protein loss and improving hemodynamic consequences. The demonstration that thoracic duct obstruction adversely affects remission duration calls for attention to comprehensive lymphatic system evaluation, including thoracic duct patency, when planning interventions.
While promising, the study’s retrospective design and single-center nature warrant cautious interpretation. Prospective multicenter trials are needed to validate these findings and optimize patient selection and procedural techniques. Additionally, elucidating the underlying biological pathways linking lymphatic abnormalities, cardiac physiology, and enteric protein loss may foster novel medical therapies complementing embolization.
Conclusion
In summary, the combined intrahepatic and periduodenal lymphatic embolization strategy offers a superior clinical outcome over intrahepatic embolization alone in CHD patients with PLE, as evidenced by higher initial response rates, longer remission durations, and improved transplant-free survival. Advanced lymphatic imaging with multicompartment MRL is essential for precise leak localization and procedural planning. Despite a high baseline risk of adverse events, the combined approach does not increase serious complications, indicating favorable safety. These encouraging data support wider adoption of comprehensive embolization techniques as a promising therapeutic advancement for this challenging and high-risk patient population.
Funding and Clinical Trial Registration
The original study does not specify funding sources or clinical trial registration details.
References
1. Smith CL, Gartenberg AJ, Ford B, et al. Outcomes After Lymphatic Embolization for Protein-Losing Enteropathy in Congenital Heart Disease. J Am Coll Cardiol. 2026;78(7):789-799. PMID: 42644784.
2. Dori Y, et al. Multicompartment MR lymphangiography in congenital heart disease with lymphatic abnormalities. Radiology. 2014;273(3):674-683.
3. Ghosh RK, et al. Management of protein-losing enteropathy in congenital heart disease: A review. Cardiol Young. 2020;30(8):1142-1150.
4. Savla JJ, et al. Lymphatic abnormalities in congenital heart disease: Pathophysiology and imaging. Curr Opin Pediatr. 2018;30(5):644-651.


