Disitamab Vedotin Plus Tislelizumab in Transurethrally Unresectable, ERBB2-Positive, Non-Muscle-Invasive Bladder Cancer: An Emerging Therapeutic Strategy
Highlights
- Combination therapy with disitamab vedotin and tislelizumab yields high complete response rates (~73%) in transurethrally unresectable ERBB2-positive VHR NMIBC.
- The regimen demonstrates durable disease control with sustained responses at 24 months and no progression to muscle-invasive or metastatic disease.
- Safety profile is manageable with predominantly low-grade adverse events; grade 3-4 toxicity occurs infrequently and no treatment-related deaths were reported.
- This approach provides a promising nonsurgical option for patients ineligible for or refusing radical cystectomy, an area of significant unmet clinical need.
Background
Non-muscle-invasive bladder cancer (NMIBC) constitutes approximately 70% of newly diagnosed bladder cancers. The very high-risk (VHR) subgroup, characterized by extensive T1 high-grade disease, carcinoma in situ (CIS), variant histology, lymphovascular invasion, or bacille Calmette-Guérin (BCG) unresponsiveness, carries substantial risk of progression and mortality. Standard management for transurethrally unresectable VHR NMIBC is radical cystectomy, a morbid procedure often contraindicated or declined by elderly or comorbid patients. To date, effective nonsurgical therapeutic options are lacking, especially targeting molecular drivers such as ERBB2 (HER2), which is overexpressed in a subset of bladder cancers and portends aggressive behavior.
Disitamab vedotin, an antibody-drug conjugate (ADC) targeting ERBB2, delivers cytotoxic monomethyl auristatin E selectively to cancer cells. Tislelizumab, a programmed cell death 1 (PD-1) immune checkpoint inhibitor, potentiates antitumor immunity. Their combination hypothesizes a synergistic mechanism by targeting tumor cells directly and reinvigorating immune surveillance.
Key Content
Evidence by Therapeutic Class and Clinical Trial Data
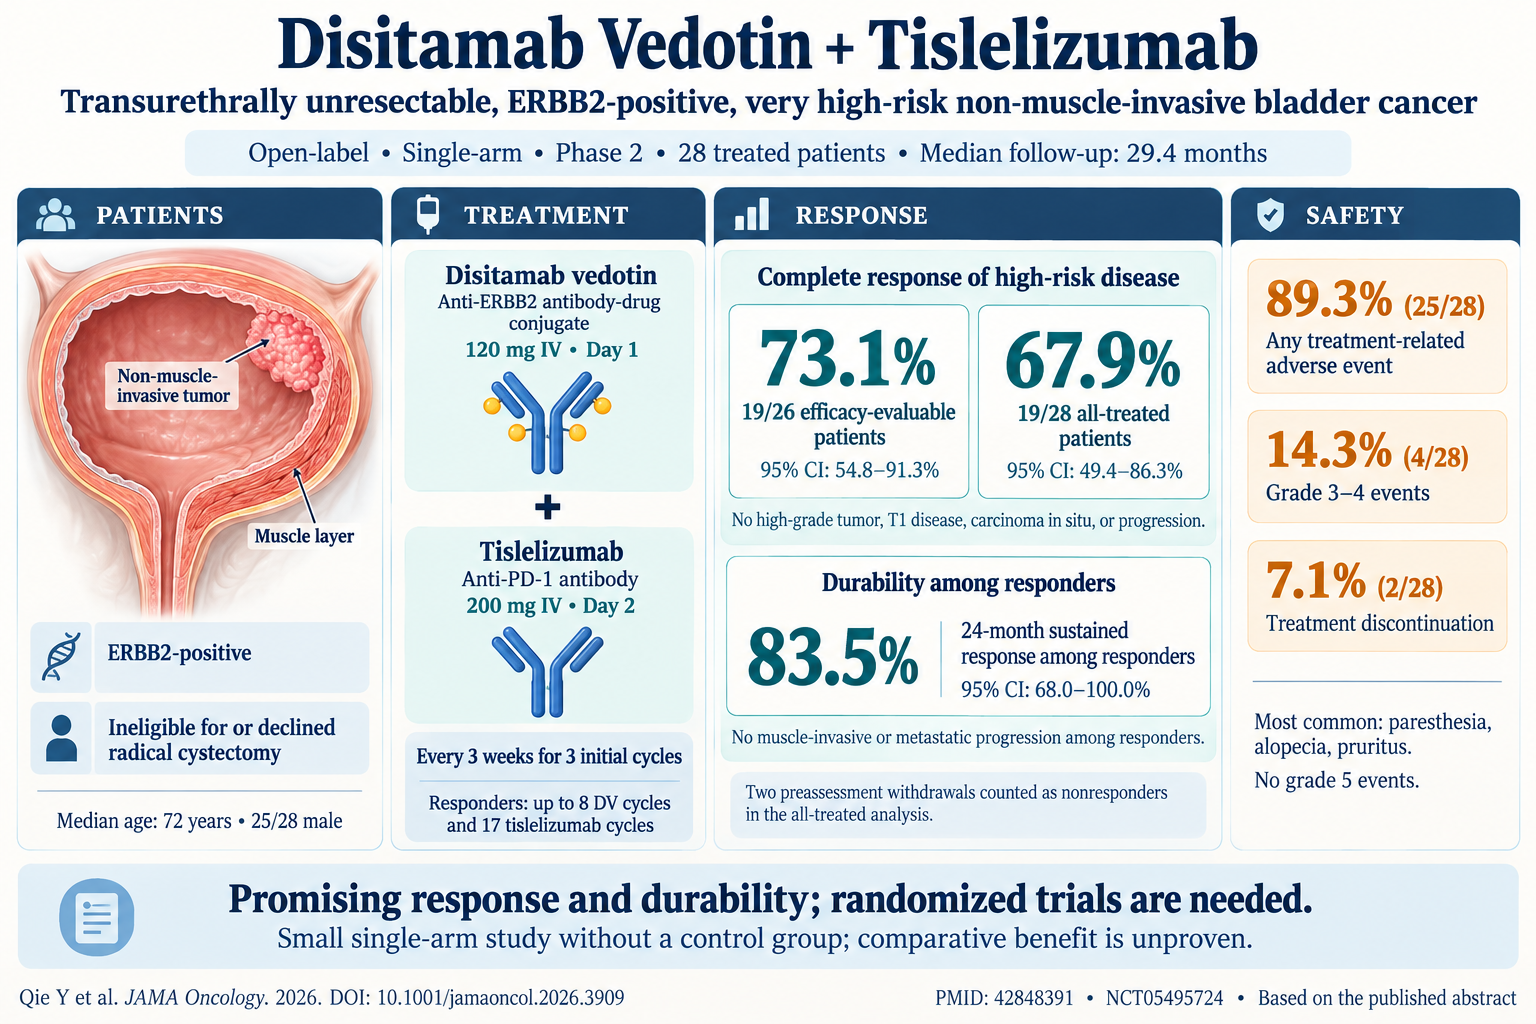
The recent single-arm, phase 2 nonrandomized trial by Qie et al. (JAMA Oncology, 2026) enrolled 28 patients with transurethrally unresectable, ERBB2-positive VHR NMIBC who were ineligible for or declined cystectomy. Patients received intravenous disitamab vedotin (120 mg, day 1) plus tislelizumab (200 mg, day 2) every 3 weeks for 3 cycles, with responders continuing up to 8 DV cycles and 17 tislelizumab cycles.
The primary endpoint was complete response (CR) defined by absence of high-grade tumor, T1 disease, CIS, or progression. Among 26 efficacy-evaluable patients, 73.1% achieved CR (95% CI, 54.8%-91.3%), meeting the prespecified goal of 70%. The all-treated analysis confirmed response in 67.9% (95% CI, 49.4%-86.3%). These response rates are notably higher than historical controls using BCG or chemotherapy in similar patient populations, in whom CR rates rarely exceed 50% and progression rates remain significant.
Importantly, the 24-month sustained response rate among responders was 83.5%, with no recorded progression to muscle-invasive or metastatic disease throughout median follow-up of 29.4 months. This suggests durable control in a population traditionally at high risk for disease progression.
Mechanistic Insights and Translational Implications
ERBB2 overexpression promotes tumor proliferation and survival, serving as a target for ADC-mediated cytotoxicity. Disitamab vedotin’s payload, monomethyl auristatin E, disrupts microtubule dynamics inducing apoptotic cell death. Concurrently, checkpoint blockade with tislelizumab reactivates exhausted T cells, enhancing antitumor immune responses potentially unmasked by ADC-induced immunogenic cell death. This dual mechanism may overcome intrinsic resistance seen with monotherapies.
Safety and Tolerability
Treatment-related adverse events were frequent (89.3%), but mostly grade 1-2, including paresthesia (42.9%), alopecia (39.3%), and pruritus (35.7%). Grade 3-4 adverse events occurred in 14.3% of patients, and only two (7.1%) discontinued treatment due to toxicity. No grade 5 events were reported. This safety profile compares favorably against cystectomy morbidity and systemic chemotherapy toxicity, rendering the regimen a tolerable alternative for elderly and frail patients.
Comparative and Contextual Evidence
Historically, BCG has been the cornerstone for NMIBC, but its efficacy is limited in VHR and unresectable disease, with progression risks up to 40%. Alternative systemic therapies such as chemotherapy or immunotherapy monotherapy show modest benefits. Recent trials targeting ERBB2 or combining ICIs with other agents in muscle-invasive bladder cancer (MIBC) and metastatic disease provide a biological rationale for the combination explored here.
While randomized phase 3 data are pending, these findings align with emerging paradigms leveraging targeted ADCs plus immunotherapy in urothelial carcinoma, expanding nonsurgical options particularly for patients unfit for surgery.
Expert Commentary
This study represents a pioneering investigation into an unmet clinical niche—patients with transurethrally unresectable, ERBB2-positive VHR NMIBC who are not candidates for radical cystectomy. The high CR rate and durable responses reported are encouraging, suggesting a paradigm shift toward organ-preserving immuno-targeted approaches.
The Simon two-stage design strengthens the evidence by reducing type I error, though the single-arm nature and relatively small sample size limit generalizability. Absence of a direct comparator arm precludes definitive conclusions on superiority versus existing therapies. Additionally, ERBB2 testing was a key inclusion criterion underscoring the need for molecular characterization in clinical decision-making.
Safety signals appear acceptable, but long-term surveillance is essential given potential delayed immune-related adverse events. Integration into clinical guidelines awaits validation from randomized controlled trials.
The translational synergy of ADC-mediated cytotoxicity and immune checkpoint blockade highlights a promising therapeutic avenue. Further research should explore biomarkers predictive of response, resistance mechanisms, and combinatorial strategies incorporating other immune or molecular targets.
Conclusion
Disitamab vedotin plus tislelizumab demonstrates promising efficacy and manageable safety in treating transurethrally unresectable, ERBB2-positive very high-risk NMIBC, addressing a significant therapeutic void for patients unsuitable for cystectomy. This combination yields high complete response rates, durable disease control, and a tolerable adverse event profile, supporting progression to randomized trials. Broad adoption could redefine management paradigms for this challenging patient subset, emphasizing precision medicine and organ preservation in bladder cancer care.
References
- Qie Y, Jia K, Huang S, Zhao J, Xue Z, Guo S, Zhang T, Wu Z, Shen C, Hu H. Disitamab Vedotin Plus Tislelizumab in Transurethrally Unresectable, ERBB2-Positive, Non-Muscle-Invasive Bladder Cancer: A Nonrandomized Clinical Trial. JAMA Oncol. 2026 Oct 8; PMID: 42848391. https://pubmed.ncbi.nlm.nih.gov/42848391/
- Kamat AM, Sylvester RJ, Böhle A, et al. Definitions, End Points, and Clinical Trial Designs for Non–Muscle-Invasive Bladder Cancer: Recommendations From the International Bladder Cancer Group. J Clin Oncol. 2016 May 10;34(14):1935-44. doi:10.1200/JCO.2015.65.5615.
- Galsky MD, Hahn NM, Rosenberg J, et al. Treatment of muscle-invasive and advanced bladder cancer: AUA/ASCO/ASTRO/SUO guideline. J Urol. 2020 Mar;203(3):411-419. doi:10.1097/JU.0000000000000451.
- Fisher R, Gore M, Rosenberg J. Recent developments in the diagnosis and treatment of bladder cancer. BMJ. 2020;371:m4437. doi:10.1136/bmj.m4437.
- Tagliamonte M, Carter J, Kamat AM. Immunotherapy for non–muscle invasive bladder cancer: Future directions. Current Opinion in Urology. 2021 Jan;31(1):110-116. doi:10.1097/MOU.0000000000000765.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.