Immunotherapy-Induced Endocrine Dysfunction in Gynecologic Oncology: Clinical Insights from a Retrospective Cohort Study
Highlight
- Immune-related endocrine toxicities (IETs), including hypothyroidism, hyperthyroidism, and insulin-dependent diabetes mellitus, affect approximately 38% of gynecologic oncology patients receiving immunotherapy.
- Most IETs are low-grade but tend to be chronic, requiring ongoing endocrine-directed therapy and frequent medication dose adjustments.
- Pre-existing endocrine disorders were common and may influence the risk and management complexity of IETs.
- Routine endocrine monitoring and tailored long-term management strategies are critical to optimizing patient outcomes while continuing immunotherapy.
Study Background
Immunotherapy has revolutionized the treatment landscape for various malignancies, including gynecologic cancers. Immune checkpoint inhibitors (ICIs), which unleash antitumor immunity by blocking inhibitory receptors such as PD-1, PD-L1, or CTLA-4, have improved survival outcomes. However, ICIs carry a risk of immune-related adverse events (irAEs) due to immune activation against normal tissues. Endocrine organs are particularly susceptible, leading to immune-related endocrine toxicities (IETs) like thyroid dysfunction and diabetes mellitus.
Gynecologic oncology patients represent a distinct population with unique immunotherapy indications and comorbidities. Understanding the frequency, clinical course, risk factors, and management needs of IETs in this group is essential for improving safety and efficacy. This study by Gonzalez et al. aims to characterize these parameters in a retrospective cohort at a single institution, thus addressing a critical gap in knowledge about endocrine irAEs in gynecologic cancers.
Study Design
This was an Institutional Review Board (IRB)-approved retrospective cohort study of all gynecologic oncology patients treated with immunotherapy between January 1, 2017, and January 1, 2023, at a single tertiary care center. The cohort included 333 patients who received various immunotherapy regimens. The investigators extracted comprehensive data from electronic medical records, including clinical characteristics, details of immunotherapy administration, onset and grading of endocrine toxicities, management strategies, time to onset and resolution, and oncologic outcomes.
The primary endpoints included the incidence of immune-related endocrine toxicities, their severity according to standard toxicity grading, the need for endocrine-directed therapies, and the impact on immunotherapy dosing. Secondary endpoints involved the time to toxicity onset and resolution, as well as the role of pre-existing endocrine disorders.
Key Findings
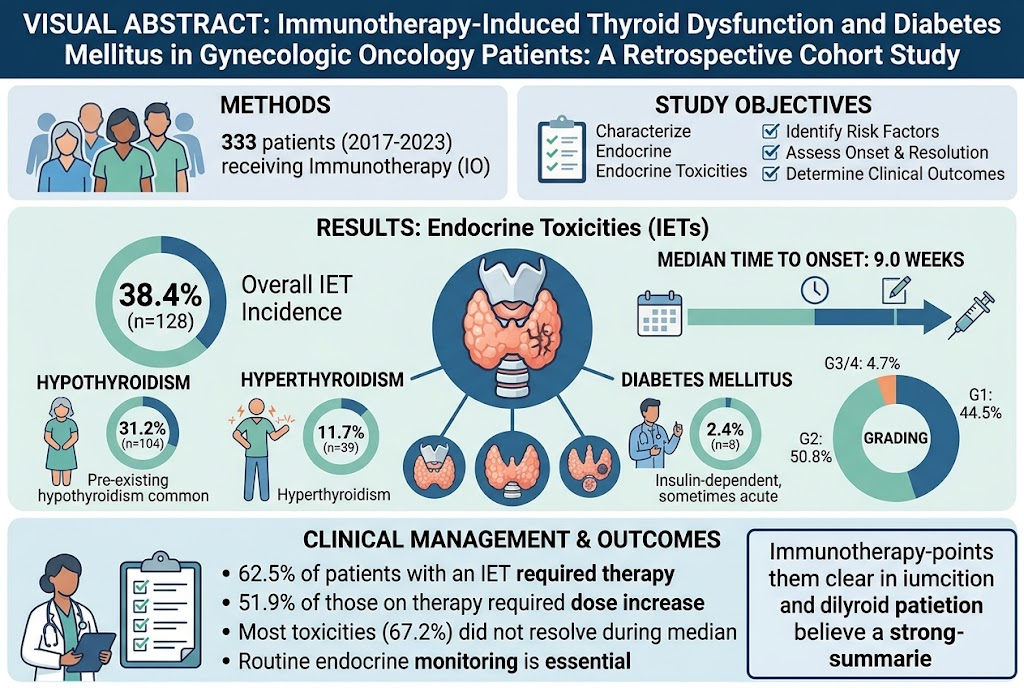
Among the 333 gynecologic cancer patients treated with immunotherapy, 128 (38.4%) developed at least one form of immune-related endocrine toxicity. The breakdown of toxicities revealed hypothyroidism as the most prevalent (31.2%, n=104), followed by hyperthyroidism (11.7%, n=39), and insulin-dependent diabetes mellitus (2.4%, n=8). These findings confirm the thyroid gland as the primary target organ affected by IETs in this clinical context, consistent with existing literature on immunotherapy toxicities.
Regarding severity, most toxicities were mild to moderate with 44.5% of cases graded as 1 and 50.8% as grade 2. A smaller subset experienced severe toxicities graded 3 or 4 (4.7%). This titration toward lower-grade toxicity aligns with typical IET presentations but underscores that serious events, though less frequent, do occur.
The median time from immunotherapy initiation to diagnosis of an endocrine toxicity was 9.0 weeks (interquartile range [IQR], 5.4–18.7 weeks), highlighting that endocrine monitoring should be prioritized early during treatment, especially within the first 3 months. Notably, most endocrine toxicities exhibited a chronic course; 67.2% (n=86) did not resolve during a median follow-up period of 16.4 months.
The management of IETs often required intervention, with 62.5% of affected patients necessitating endocrine-directed therapy such as thyroid hormone replacement or insulin therapy. Furthermore, 56.3% needed immunotherapy dose adjustments, reflecting the clinical impact of IETs on cancer treatment continuity. Among patients with pre-existing endocrine disorders (43.8% of the cohort; primarily hypothyroidism or diabetes), over half (51.9%) required escalation of baseline endocrine medications during immunotherapy, indicating that pre-existing dysfunction may predispose to worsening or complexity in managing IETs.
These observations underscore a two-fold challenge: immune-related endocrine adverse events are common and frequently persistent, necessitating vigilant monitoring and tailored long-term endocrinological care to safely maintain immunotherapy dosing and optimize oncologic outcomes.
Expert Commentary
The findings from this comprehensive retrospective study resonate with broader immuno-oncology experience emphasizing thyroid dysfunction as the most frequent endocrine irAE during checkpoint blockade. The substantial incidence of insulin-dependent diabetes mellitus, though less common, is particularly notable in the gynecologic oncology setting, as this complication often results in irreversible pancreatic β-cell destruction, necessitating lifelong insulin therapy.
Importantly, the study highlights the clinical complexity added by pre-existing endocrinopathies, which may worsen or complicate management during immunotherapy. The data also reaffirm that most IETs manifest relatively early, underscoring the value of baseline endocrine assessment and routine serial monitoring of thyroid function tests and glucose levels throughout treatment.
From a mechanistic perspective, immune checkpoint inhibition induces T-cell–mediated autoimmunity that targets endocrine tissues, leading to glandular inflammation and irreversible damage. Unlike some other irAEs that may resolve quickly upon immunosuppression, endocrine toxicities often necessitate permanent hormonal replacement.
One limitation inherent to the retrospective design is potential incompleteness of data capture and variability in toxicity grading and management protocols. Moreover, single-center data may limit generalizability, and prospective studies are warranted to validate risk factors and optimize monitoring strategies. However, the substantial sample size and thorough documentation strengthen the reliability of the conclusions.
Conclusion
Immune-related endocrine toxicities are a prevalent and clinically significant complication among gynecologic oncology patients undergoing immunotherapy. Predominantly manifesting as thyroid dysfunction and, less commonly, insulin-dependent diabetes mellitus, these endocrine adverse events are usually low-grade but tend to be chronic and require ongoing therapeutic management and adjustment. The presence of pre-existing endocrine disorders often complicates clinical care.
This study underscores the imperative for routine endocrine surveillance before and during immunotherapy, combined with multidisciplinary collaboration between oncologists and endocrinologists. Early detection and proactive management are critical to maintaining immunotherapy treatment intensity and maximizing cancer outcomes while minimizing morbidity related to endocrine dysfunction.
Future research should focus on prospective risk stratification, biomarker identification, and development of standardized clinical algorithms for monitoring and managing IETs in this vulnerable population.
Funding and ClinicalTrials.gov
The source article does not specify funding details or clinical trial registration information.
References
1. Gonzalez A, Chalif J, O’Connor R, et al. Immunotherapy-induced thyroid dysfunction and diabetes mellitus in gynecologic oncology patients: a retrospective cohort study. Gynecol Oncol. 2026;214:7-14. PMID: 42805135.
2. Hodi FS, Mihm MC, et al. Immune-modulating antibody therapy in cancer. Adv Immunol. 2014;125:43-92.
3. Barroso-Sousa R, Barry WT, Garrido-Castro AC, et al. Incidence of endocrine dysfunction following the use of different immune checkpoint inhibitor regimens: a systematic review and meta-analysis. JAMA Oncol. 2018;4(2):173-182.
4. Cukier P, Mattar R, Chaves Junior RF, et al. Immune checkpoint inhibitors and endocrinopathies: A review. Clinics (Sao Paulo). 2020;75:e1386.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.