Cushing’s Syndrome in the Elderly: Diagnostic and Therapeutic Nuances in an Aging Population
Introduction
Cushing’s syndrome (CS), a clinical condition characterized by prolonged exposure to excess glucocorticoids, is rare but clinically significant in the elderly population. Though the biochemical and diagnostic tests mirror those used in younger adults, the elderly often present unique diagnostic challenges and therapeutic considerations. This article discusses the nuances in recognizing, diagnosing, and managing Cushing’s syndrome in older adults, emphasizing the differences relative to younger populations and the pivotal role of individualized care.
Clinical Context and Disease Burden in the Elderly
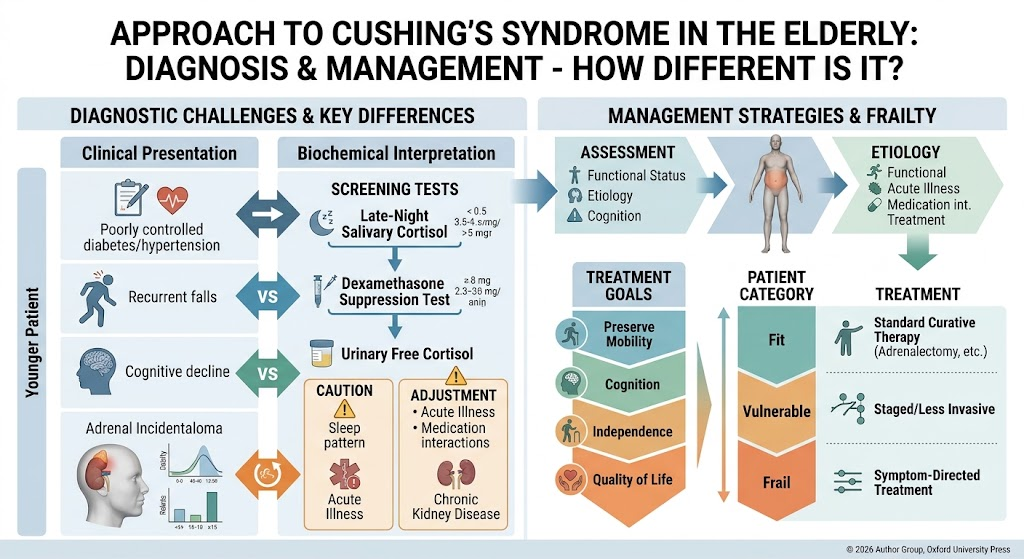
While CS is uncommon in older adults, its clinical implications are profound due to the frequent overlap of hypercortisolism features with common geriatric syndromes. Classic cushingoid signs such as moon face, central obesity, and purple striae may be subtle or absent in this age group. Instead, symptoms like refractory hypertension and diabetes mellitus, rapid osteoporosis with fractures, proximal muscle weakness, cognitive decline, recurrent falls, venous thromboembolism, or incidental adrenal masses often predominate. This presentation overlap leads to a dual diagnostic dilemma: under-recognition of significant CS and overdiagnosis of mild biochemical abnormalities without clinical relevance. Given the associated morbidity, early and accurate diagnosis combined with careful management is critical to improve outcomes.
Differential Diagnosis and Initial Assessment
A key first step is excluding exogenous glucocorticoid exposure, a common cause of iatrogenic hypercortisolism often overlooked in the elderly due to the frequent use of steroids in various formulations. Attention must then focus on identifying progressive and discriminatory clinical features suggestive of endogenous CS. The clinical suspicion threshold may need to be adjusted, given that subtle signs in the elderly may conceal serious pathology.
Diagnostic Testing: Considerations for the Elderly
Diagnostic evaluation includes biochemical testing of cortisol excess, but interpretation requires age-appropriate adjustments:
1. Late-Night Salivary Cortisol (LNSC): This test is convenient and non-invasive but must be repeated and cautiously interpreted, especially in patients with diabetes, sleep disturbances, or acute illnesses common in older adults that can cause false elevations.
2. 24-Hour Urinary Free Cortisol (UFC): Though standard, UFC may be falsely low in chronic kidney disease, which is prevalent in the elderly. Renal function must be reviewed before relying on this test.
3. Dexamethasone Suppression Test (DST): The overnight or low-dose DST remains a cornerstone but requires scrutiny regarding drug interactions (e.g., medications inducing or inhibiting cytochrome P450 enzymes affecting dexamethasone metabolism). Measurement of dexamethasone serum levels in selected patients can clarify ambiguous results.
4. Screening Strategy: Selection of tests should consider comorbidities, polypharmacy, and the probability of non-neoplastic hypercortisolism causes such as pseudo-Cushing’s states (e.g., depression, alcoholism).
Etiological Investigation and Imaging
Once hypercortisolism is biochemically confirmed, subsequent testing aims to differentiate adrenocorticotropic hormone (ACTH)-dependent from ACTH-independent causes. Imaging strategies consider baseline adrenal function and patient frailty. Adrenal incidentalomas, frequently discovered on abdominal imaging in older persons, necessitate careful evaluation to exclude cortisol-secreting adenomas or carcinomas.
Management Principles Tailored to the Elderly
Treatment decisions should prioritize the patient’s functional status, comorbid conditions, and personal preferences over chronological age:
– Fit Older Adults: Candidates for standard curative interventions such as transsphenoidal surgery for pituitary adenomas or adrenalectomy should be offered these therapies given potential for remission and life quality improvement.
– Vulnerable or Frail Patients: For those with limited physiological reserve or multiple comorbidities, staged or less invasive approaches may be preferable, such as medical therapy targeting cortisol synthesis or symptom control.
– Goals of Therapy: Beyond biochemical remission, preservation of mobility, cognitive function, independence, and overall quality of life must be explicitly set as priorities.
– Pharmacologic Treatments: Agents such as steroidogenesis inhibitors or glucocorticoid receptor antagonists can be effective when surgery is contraindicated or declined.
– Multidisciplinary Management: Coordination with geriatricians, endocrinologists, physical therapists, and nutritionists is important for comprehensive care.
Prognosis and Follow-Up
Monitoring involves repeated clinical and biochemical assessments to ensure treatment efficacy and detect relapse. Particular attention to bone health, glucose control, and cardiovascular risk modification is warranted due to heightened vulnerability in older adults.
Conclusion and Future Directions
The diagnosis and management of Cushing’s syndrome in the elderly present distinct challenges shaped by atypical clinical presentations, comorbidities, and pharmacologic complexities. An individualized, pragmatic approach emphasizing functional status and quality of life enables optimal outcomes. Future research should focus on developing geriatric-specific diagnostic algorithms, refining biochemical thresholds, and evaluating less invasive therapeutic modalities. Heightened clinical awareness and multidisciplinary collaboration remain key to improving care for this vulnerable population.
References
1. Liu Y, Yi L, Tan H. Approach to the Patient: Diagnosis and Management of Cushing’s Syndrome in the Elderly – How Different Is It?. The Journal of Clinical Endocrinology and Metabolism. 2026 Sep 6; PMID: 42701317.
2. Nieman LK, et al. The diagnosis of Cushing’s syndrome: an Endocrine Society Clinical Practice Guideline. J Clin Endocrinol Metab. 2008 May;93(5):1526-40.
3. Pivonello R, et al. Pharmacological treatment of Cushing’s syndrome: current options and future perspectives. Endocrine. 2020 Jun;68(3):379-392.
4. Mulatero P, et al. The clinical and biochemical spectrum of cortisol excess in adrenal incidentalomas: a systematic review. Horm Metab Res. 2017 Feb;49(2):105-114.
5. Clayton RN, et al. Diagnosis and treatment of Cushing’s syndrome: An Endocrine Society Clinical Practice Guideline update. J Clin Endocrinol Metab. 2023;108(8):2225–2250.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.