Conduction System Pacing vs Biventricular Pacing After AV Node Ablation in AF with Heart Failure: Insights from the CONDUCT-AF Trial
Highlight
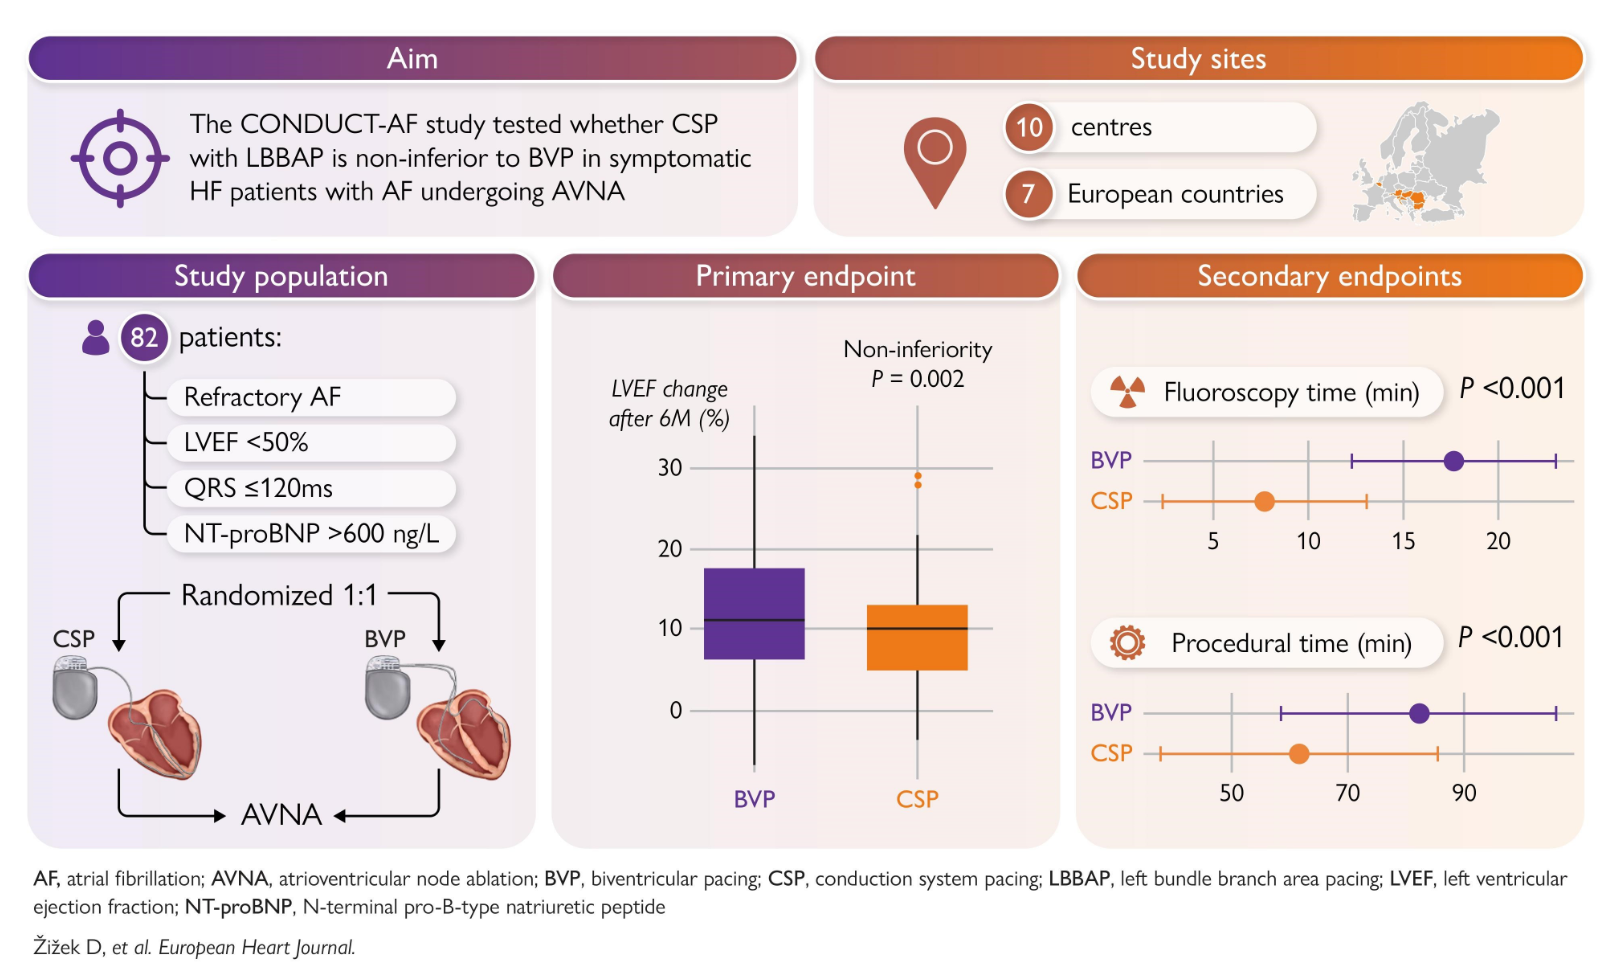
– CONDUCT-AF trial compared conduction system pacing (CSP) using left bundle branch area pacing to biventricular pacing (BVP) after atrioventricular (AV) node ablation in patients with atrial fibrillation and heart failure.
– Both pacing strategies yielded significant and comparable improvement in left ventricular ejection fraction (LVEF) at 6 months.
– CSP was associated with shorter paced QRS duration and reduced procedural and fluoroscopy times compared to BVP.
– Clinical outcomes including heart failure progression and cardiovascular death were similar between groups.
Study Background
Heart failure (HF) with concomitant atrial fibrillation (AF) represents a common and challenging clinical scenario, particularly when AF is refractory to medical therapies. AV node ablation with permanent pacing is an established strategy to control ventricular rate and improve symptoms in this population. Traditionally, biventricular pacing (BVP) has been preferred to maintain ventricular synchrony and optimize cardiac function post-ablation, especially in patients with reduced left ventricular ejection fraction (LVEF). However, conduction system pacing (CSP)—which directly captures the His-Purkinje conduction pathways, such as left bundle branch area pacing—has emerged as a physiological alternative that might improve electrical synchrony more naturally and efficiently while simplifying procedural complexity.
Randomized data comparing these two pacing strategies in AF patients after AV node ablation have been limited. The CONDUCT-AF trial aimed to fill this gap by evaluating the efficacy and safety of CSP versus BVP in patients with refractory AF and HF with LVEF below 50%, narrow baseline QRS, and elevated biomarkers indicative of HF severity.
Study Design
CONDUCT-AF was a multicenter, prospective, randomized controlled study conducted at 10 European centers. Eighty-two patients with refractory AF, left ventricular systolic dysfunction (LVEF <50%), normal or narrow QRS complexes (≤120 ms), and elevated N-terminal pro-B-type natriuretic peptide (NT-proBNP >600 ng/L) were randomized in a 1:1 fashion to receive either:
- Conduction system pacing (CSP)—implantation of a lead for left bundle branch area pacing;
- Biventricular pacing (BVP)—standard cardiac resynchronization therapy device implantation.
The primary endpoint was the change in LVEF after 6 months post-AV node ablation, assessed by an independent echocardiographic core laboratory. Secondary endpoints included changes in left ventricular volumes, clinical heart failure parameters, procedural characteristics (such as fluoroscopy time), and composite outcomes of worsening heart failure or cardiovascular death. The analysis adhered to an intention-to-treat protocol.
Key Findings
The study enrolled predominantly elderly patients (mean age 72 ± 7 years), balanced in gender distribution (46% male). Baseline characteristics including LVEF and QRS duration were comparable between the CSP and BVP groups.
Primary outcome: Both CSP and BVP groups experienced a significant increase in LVEF at 6 months:
- CSP: 36% (95% CI 33-39) to 46% (95% CI 44-49), p<0.001;
- BVP: 34% (95% CI 31-36) to 46% (95% CI 43-49), p<0.001.
The between-group differential in LVEF improvement was 0.4% (95% CI −3.1 to 3.8), meeting the predefined criteria for non-inferiority (p=0.002).
Secondary outcomes: There were no statistically significant differences in left ventricular end-diastolic and end-systolic volumes, clinical heart failure markers, or the composite endpoint of HF worsening or cardiovascular death.
Procedural metrics: CSP was associated with a significantly shorter paced QRS duration by 14 ms (95% CI −19 to −9 ms, p<0.001), indicating potentially better electrical synchronization. Furthermore, procedural and fluoroscopy times were significantly reduced with CSP compared to BVP, reflecting procedural efficiency advantages.
Safety and complications: The study did not report significant differences in device-related complications or adverse events between groups during the follow-up period.
Expert Commentary
The CONDUCT-AF trial provides robust randomized evidence in support of conduction system pacing as a clinically effective and procedural advantageous alternative to traditional biventricular pacing in a challenging population of AF patients with heart failure undergoing AV node ablation. The preservation of physiological ventricular activation through left bundle branch area pacing may translate into comparable improvements in systolic function and clinical status while simplifying implantation.
Limitations include modest sample size and relatively short follow-up duration of 6 months, which may constrain assessment of long-term outcomes such as mortality or device-related complications. Additionally, the study population was selected for narrow QRS and elevated NT-proBNP, potentially limiting external generalizability to broader HF-AF cohorts.
Current guidelines recognize the role of BVP post-AV node ablation, but the emergence of CSP, as demonstrated here, may prompt reconsideration given its electrophysiological advantages and procedural efficiency. Future studies with larger cohorts and longer follow-up are essential to confirm sustained benefits and inform guidelines.
Conclusion
In patients with heart failure and refractory atrial fibrillation undergoing AV node ablation, conduction system pacing with left bundle branch area pacing was non-inferior to biventricular pacing with regard to left ventricular systolic function improvement at 6 months. CSP offers comparable clinical outcomes and a more favorable procedural profile, endorsing its use as a viable pacing strategy in this setting.
These findings support expanding adoption of conduction system pacing in appropriate patients while underscoring the need for continued research to define its long-term impact on morbidity, mortality, and quality of life.
Funding and Clinical Trial Registration
The CONDUCT-AF trial was investigator-initiated and conducted in multiple European centers. Details regarding funding sources were not provided in the published abstract. The trial registration status can be accessed via the study’s publication on PubMed (PMID: 42834810).
References
Žižek D, Ivanovski M, Mrak M, et al. Biventricular vs conduction system pacing after atrioventricular node ablation for heart failure with atrial fibrillation: the CONDUCT-AF trial. European Heart Journal. 2026 Oct 6. PMID: 42834810.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.