Assessing Transvaginal Drainage Versus Laparoscopy for Tubo-Ovarian Abscess: Insights from a Multicenter Randomized Trial
Highlight
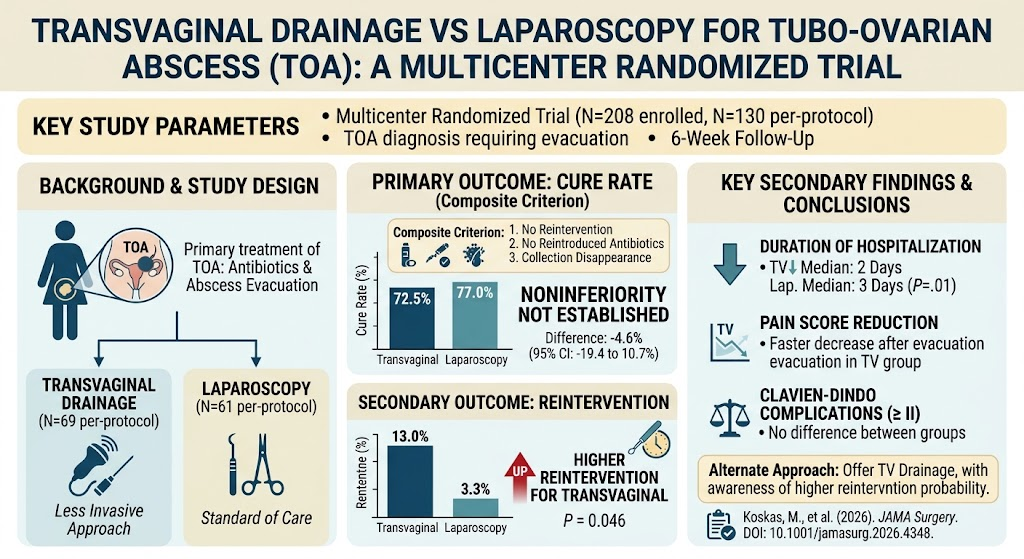
This randomized clinical trial evaluated the noninferiority of transvaginal drainage versus laparoscopy for treating tubo-ovarian abscess (TOA). Though cure rates were comparable within the noninferiority margin, transvaginal drainage showed a significantly higher rate of surgical reintervention. Hospital stays were shorter and postoperative pain decreased faster with transvaginal drainage.
Study Background
Tubo-ovarian abscess is a serious complication of pelvic inflammatory disease characterized by a pus-filled mass involving the fallopian tube and ovary. Prompt management is vital to prevent severe sequelae such as infertility, rupture, or sepsis. Standard treatment generally includes antibiotic therapy combined with abscess evacuation, most commonly via either transvaginal ultrasound-guided drainage or laparoscopy. Each approach has distinct procedural invasiveness, risks, and recovery profiles. However, comparative evidence from rigorously designed trials has been limited. This study addresses an important clinical question: Can the less invasive transvaginal drainage provide equivalent efficacy and safety compared to laparoscopy for TOA management?
Study Design
The PACTOL trial was a multicenter, randomized, controlled open-label noninferiority clinical trial conducted across 19 French hospitals from April 2019 to April 2023. Eligible participants were women aged 18 years or older scheduled for TOA evacuation. A total of 208 women were randomized to either ultrasound-guided transvaginal drainage or laparoscopy. The primary endpoint was a composite cure rate evaluated at 6 weeks post-evacuation, defined by the absence of surgical reintervention, no requirement for additional antibiotic therapy, and resolution of the tubo-ovarian collection confirmed radiologically. Noninferiority was pre-specified as a margin of a 12.5 percentage point difference or less between groups. Secondary outcomes included duration of hospitalization, postoperative pain scores, complications graded by Clavien-Dindo classification, and rates of reintervention.
Key Findings
Among 208 enrolled patients, 130 were included in the per-protocol analysis, comprising 69 in the transvaginal drainage group and 61 in the laparoscopy group. At 6 weeks, cure was achieved in 72.5% of the transvaginal drainage group and 77.0% of the laparoscopy group. The absolute difference in cure rates was –4.6 percentage points (95% confidence interval [CI], –19.4 to 10.7), which failed to conclusively demonstrate noninferiority given the confidence interval exceeded the pre-defined margin.
Reintervention after abscess evacuation was significantly more frequent following transvaginal drainage (13.0%) compared to laparoscopy (3.3%; P = .046). However, no significant differences were observed in persistence of the abscess or need to reintroduce antibiotics. Notably, hospitalization duration was shorter for transvaginal drainage with a median of 2 days versus 3 days for laparoscopy (P = .01). Patients receiving transvaginal drainage also reported a more rapid decline in pain scores post-procedure. Rates of surgical complications classified as Clavien-Dindo grade II or higher were similar between groups, indicating comparable safety profiles.
Expert Commentary
This study provides the largest randomized comparison to date of transvaginal drainage and laparoscopy for TOA treatment, offering clinically important data to inform therapeutic decision-making. Although noninferiority was not statistically established, the modest difference in cure rates may reflect heterogeneity in patient and abscess characteristics rather than intrinsic inferiority of the less invasive approach. The increased reintervention rate with transvaginal drainage, possibly related to incomplete initial evacuation or abscess complexity, warrants consideration and patient counseling.
The shorter hospitalization and quicker pain resolution with transvaginal drainage highlight benefits of reduced invasiveness and resource utilization. Current guidelines variably recommend both approaches but emphasize individualized treatment choices based on abscess size, clinical stability, and institutional expertise. Further research should explore predictors of successful transvaginal drainage and refine indications to optimize outcomes.
Conclusion
In this multicenter randomized clinical trial, ultrasound-guided transvaginal drainage did not demonstrate noninferiority to laparoscopy for tubo-ovarian abscess cure, primarily due to a higher rate of reintervention. Nevertheless, its advantages in terms of shorter hospitalization and faster pain improvement support it as a viable alternative, particularly for selected patients. Clinicians should inform patients about the increased likelihood of additional procedures following transvaginal drainage. Incorporating patient preferences, abscess characteristics, and available expertise into shared decision-making remains paramount.
Funding and ClinicalTrials.gov
The PACTOL trial was supported by institutional and public research funds as detailed in the primary publication. The trial was registered under ClinicalTrials.gov Identifier NCT03819309.
References
Koskas M, Laouenan C, Esposito-Farese M, et al. Transvaginal Drainage vs Laparoscopy for Tubo-Ovarian Abscess: A Randomized Clinical Trial. JAMA Surg. 2026 Sep 23. PMID: 42776546. DOI: 10.1001/jamasurg.2026.XXXX
Workowski KA, Wiesenfeld HC, Berman S, et al. Sexually transmitted infections treatment guidelines, 2021. MMWR Recomm Rep. 2021;70(4):1-187.
Haggerty CL, Wiesenfeld HC, Bass DC. Advances in the diagnosis and management of pelvic inflammatory disease. Obstet Gynecol. 2008;111(3):637-647.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.