Highlight
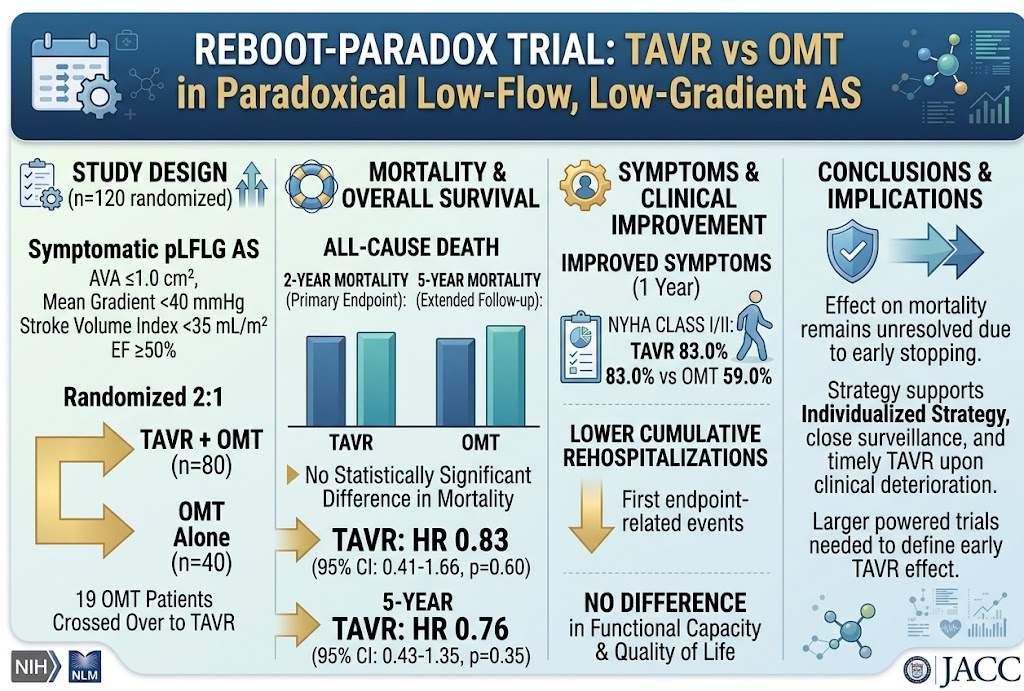
Paradoxical low-flow, low-gradient (pLFLG) aortic stenosis presents a unique clinical challenge due to its association with poor outcomes and the unclear benefit of intervention. The REBOOT-PARADOX trial evaluated transcatheter aortic valve replacement (TAVR) added to optimal medical therapy (OMT) versus OMT alone in symptomatic patients with pLFLG AS. Although TAVR did not significantly reduce all-cause mortality compared to OMT alone, it improved symptoms and reduced rehospitalizations, endorsing an individualized approach with close monitoring and timely intervention.
Study Background and Disease Burden
Aortic stenosis (AS) is a frequent valvular heart disease predominantly affecting elderly populations. Among its phenotypes, paradoxical low-flow, low-gradient AS is characterized by severe valve narrowing (aortic valve area ≤1.0 cm²) despite low transvalvular gradients (<40 mm Hg) and preserved left ventricular ejection fraction (≥50%). It is paradoxical because the low gradients suggest less severity despite critical stenosis, complicating diagnosis and management. Patients with pLFLG AS often have smaller stroke volumes (indexed stroke volume <35 mL/m²) and experience significant symptoms such as dyspnea with an adverse prognosis relative to other AS subtypes due to under-recognition and delayed treatment.
While surgical or transcatheter valve replacement improves outcomes in classic high-gradient AS, the optimal treatment strategy for pLFLG AS remains controversial. Medical therapy alone has limited efficacy, and the benefit of TAVR in this subgroup has yet to be definitively established in randomized trials.
Study Design
The REBOOT-PARADOX trial (NCT03863132) was a multicenter, open-label randomized controlled trial designed to investigate whether adding TAVR to OMT reduces mortality in symptomatic patients with pLFLG AS. Eligible patients had symptomatic pLFLG AS defined by an aortic valve area ≤1.0 cm², mean gradient <40 mm Hg, stroke volume index <35 mL/m², and preserved ejection fraction (≥50%).
Patients were randomized in a 2:1 ratio to either undergo TAVR plus OMT or receive OMT alone. The primary endpoint was all-cause mortality assessed at 2 years following the last patient’s enrollment. Secondary endpoints included symptomatic improvement measured by New York Heart Association (NYHA) functional class, rehospitalization rates, functional capacity, and quality of life assessments.
The trial was prematurely halted due to slow recruitment after enrolling 120 patients out of an initially planned 783. Of these 120 patients (median age 82 years, 53.3% women), 80 underwent TAVR plus OMT while 40 received OMT alone.
Key Findings
The primary endpoint, all-cause mortality at 2 years, occurred in 29.0% of patients in the TAVR plus OMT group versus 37.1% in the OMT alone group (hazard ratio [HR] 0.83; 95% confidence interval [CI], 0.41 to 1.66; P = 0.60), reflecting a nonsignificant difference. Similarly, 5-year mortality was 44.9% with TAVR versus 56.6% with OMT (HR 0.76; 95% CI, 0.43 to 1.35; P = 0.35), also statistically nonsignificant.
Importantly, 19 patients initially assigned to OMT crossed over to receive TAVR, predominantly due to symptomatic deterioration, reflecting clinical practice realities and potentially affecting outcomes.
Symptomatically, the TAVR group exhibited marked improvement in NYHA functional class, with 83.0% achieving NYHA class I or II status at 1 year versus 59.0% in the OMT group. Additionally, TAVR was associated with a reduced cumulative incidence of first rehospitalizations related to study endpoints, signaling better clinical stability.
No statistically significant differences were noted for functional capacity tests or quality-of-life measures between groups.
Expert Commentary
The REBOOT-PARADOX trial contributes valuable prospective randomized data to a field previously dominated by observational studies and retrospective analyses. The failure to demonstrate a clear mortality benefit with early TAVR in pLFLG AS may be related to modest sample size, crossover effects, and the heterogeneity of this patient population.
Experts emphasize that the preserved ejection fraction and low-flow status complicate assessment of AS severity and timing for intervention. The symptomatic and rehospitalization benefits observed with TAVR support its use in patients showing clinical deterioration under medical management.
Current guidelines recommend individualized approaches for pLFLG AS, integrating multimodal imaging, hemodynamic evaluation, and close clinical surveillance. This trial highlights the need for adequately powered randomized studies to clarify the effect of early versus delayed TAVR on survival, functional outcomes, and quality of life in this subgroup.
Conclusion
The REBOOT-PARADOX trial, despite early termination, indicates no definitive mortality reduction from TAVR added to OMT in symptomatic pLFLG AS patients but does show improved symptomatic status and reduced rehospitalizations. These data advocate for an individualized clinical approach with vigilant monitoring and consideration of TAVR upon symptomatic progression.
Further large-scale, well-powered randomized controlled trials are warranted to delineate the optimal timing of TAVR in pLFLG AS and to inform evidence-based clinical guidelines, ultimately improving management and outcomes in this high-risk population.
Funding and Clinical Trials Registration
The REBOOT-PARADOX trial was sponsored by an academic consortium and registered at ClinicalTrials.gov under identifier NCT03863132.
References
- Mehilli J, Steffen J, Rudolph T, et al. Transcatheter Aortic Valve Replacement or Medical Treatment for Paradoxical Low-Flow, Low-Gradient Aortic Valve Stenosis: REBOOT-PARADOX. J Am Coll Cardiol. 2026;78(8):909-920. PMID: 42663358.
- Baumgartner H, Falk V, Bax JJ, et al. 2017 ESC/EACTS Guidelines for the Management of Valvular Heart Disease. Eur Heart J. 2017;38(36):2739-2791.
- Clavel MA, Dumesnil JG, Capoulade R, et al. Impact of Aortic Valve Replacement on Survival in Very Severe Aortic Stenosis. J Am Coll Cardiol. 2015;65(17):1708-1715.


