Robotic vs Thoracolaparoscopic Esophagectomy: Advancing Surgical Precision in Esophageal Cancer Treatment
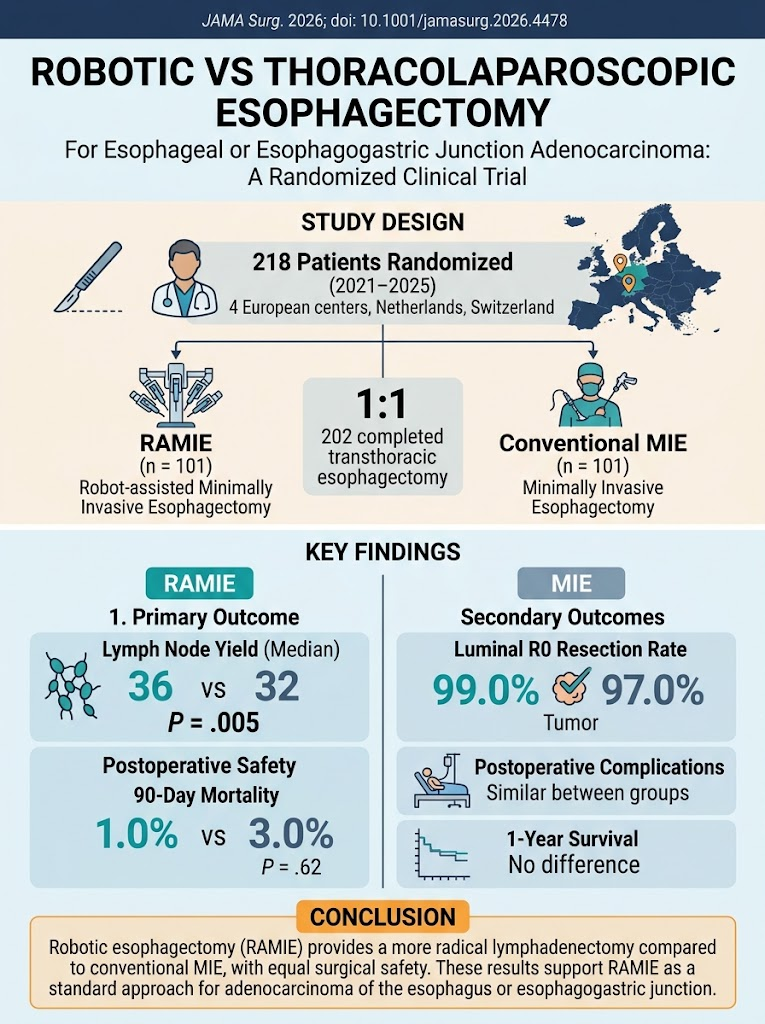
Highlight
- Robotic-assisted minimally invasive esophagectomy (RAMIE) achieves a significantly greater lymph node yield compared to conventional minimally invasive esophagectomy (MIE) in esophageal adenocarcinoma surgery.
- The study demonstrated equivalent surgical safety profiles, postoperative complication rates, and 90-day mortality between RAMIE and MIE.
- No difference was observed in 1-year overall survival between the two surgical approaches, supporting RAMIE as a safe and oncologically effective standard procedure.
Study Background
Esophageal adenocarcinoma represents a highly aggressive malignancy with substantial mortality worldwide. Transthoracic esophagectomy remains a cornerstone of curative treatment, often combined with neoadjuvant therapy. Meticulous lymphadenectomy during surgery is critical for accurate staging and may impact oncologic outcomes such as local control and survival. Conventional minimally invasive esophagectomy (MIE) has reduced surgical trauma and complications compared to open esophagectomy. However, limitations in dexterity and visualization may constrain lymph node dissection extent.
Robot-assisted minimally invasive esophagectomy (RAMIE) offers enhanced three-dimensional visualization, wristed instruments, and tremor filtration, potentially enabling more radical lymphadenectomy while maintaining minimal invasiveness. Prior cohort studies suggested advantages of RAMIE in lymph node yield and postoperative recovery, but high-level evidence from randomized controlled trials remained lacking.
Study Design
This phase 3 multicenter randomized clinical trial enrolled patients from four high-volume European tertiary referral centers specializing in esophageal surgery: Mainz (Germany), Amsterdam (Netherlands), Zurich (Switzerland), and Cologne (Germany). Eligibility criteria included patients with resectable esophageal or esophagogastric junction adenocarcinomas, clinical stages cT1-4a, cN0-3, and cM0. Both primary surgery candidates and those receiving multimodal treatments were included.
A total of 218 patients were randomized in a 1:1 fashion to either RAMIE or conventional thoracolaparoscopic MIE, with 202 completing surgery and primary analysis. The surgical procedure consisted of transthoracic esophagectomy with lymphadenectomy. The primary endpoint was the number of lymph nodes resected, analyzed on a modified intention-to-treat basis. Secondary endpoints included luminal R0 resection rate, postoperative complication rates, 90-day mortality, and 1-year survival.
Key Findings
Among 202 patients (mean age 64.8 years; 89.6% male), 101 underwent RAMIE and 101 MIE. The median resected lymph node number was significantly higher in the RAMIE group compared with MIE (36 vs 32 nodes; p=0.005). This indicates a more radical and extensive lymphadenectomy with the robotic approach.
The luminal R0 resection rates, indicating complete tumor removal with clear margins, were 99.0% with RAMIE and 97.0% with MIE, reflecting excellent oncologic technique in both arms.
Postoperative complication profiles were similar between groups, including pulmonary complications and anastomotic leaks. The 90-day mortality was low and not significantly different (1.0% for RAMIE vs 3.0% for MIE; p=0.62), underscoring comparable safety.
Survival outcomes at one year did not significantly differ, suggesting equivalent medium-term oncological effectiveness despite the greater lymph node yield.
Expert Commentary
This rigorously designed randomized trial provides high-quality evidence favoring RAMIE for achieving superior lymphadenectomy without compromising patient safety. Enhanced dexterity and visualization from the robotic platform may allow surgeons to dissect nodal stations more completely, potentially reducing residual tumor burden and improving staging accuracy.
While higher lymph node yield is associated with better oncologic outcomes in esophageal cancer, this study did not observe an overall survival benefit at one year. Longer-term follow-up is necessary to assess whether the radical lymphadenectomy translates into improved survival or disease-free intervals.
The lack of difference in complication rates and mortality confirms that RAMIE can be adopted safely in experienced centers. Nevertheless, the necessity for specialized training, operating room infrastructure, and cost considerations remain important factors for widespread implementation.
Variability in surgeon experience and institutional volume may affect generalizability, but the multicenter design across established European referral centers enhances applicability. Further comparative effectiveness studies and cost-utility analyses are warranted.
Conclusion
This landmark randomized clinical trial demonstrates that robotic-assisted minimally invasive esophagectomy provides a more comprehensive lymphadenectomy with comparable safety and short-term oncologic outcomes compared to conventional thoracolaparoscopic MIE for esophageal and esophagogastric junction adenocarcinoma.
These findings support considering RAMIE as a standard surgical approach where resources and expertise are available, potentially improving staging accuracy and long-term cancer control. Future research should focus on survival outcomes beyond one year, quality of life, and cost-effectiveness to guide clinical and policy decision-making.
Funding and Trial Registration
The trial was conducted from January 2021 to March 2025 at four European tertiary referral centers. It was registered under ClinicalTrials.gov Identifier NCT04306458. Funding sources were not explicitly stated in the abstract but are expected to be disclosed in the full publication.
References
1. Berlth F, Gisbertz SS, Tagkalos E, et al. Robotic vs Thoracolaparoscopic Esophagectomy for Esophageal Cancer: A Randomized Clinical Trial. JAMA Surg. 2026;doi:10.1001/jamasurg.2026.42814447.
2. Luketich JD, Pennathur A, Awais O, et al. Minimally invasive esophagectomy: outcomes in 222 patients. Ann Surg. 2012;256(1):95-103.
3. Mariette C, Burtin P, Perrodeau E, et al. Hybrid minimally invasive esophagectomy for esophageal cancer. N Engl J Med. 2019;380(2):152-162.
4. van der Sluis PC, van der Horst S, May AM, et al. Robot-assisted minimally invasive esophagectomy versus open transthoracic esophagectomy for resectable esophageal cancer: a randomized controlled trial. Ann Surg. 2019;269(4):621-630.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.