Persistent High Rates of Head CT in Pediatric Mild Traumatic Brain Injury: Variability Among Hospital Types and Implications for Practice
Highlight
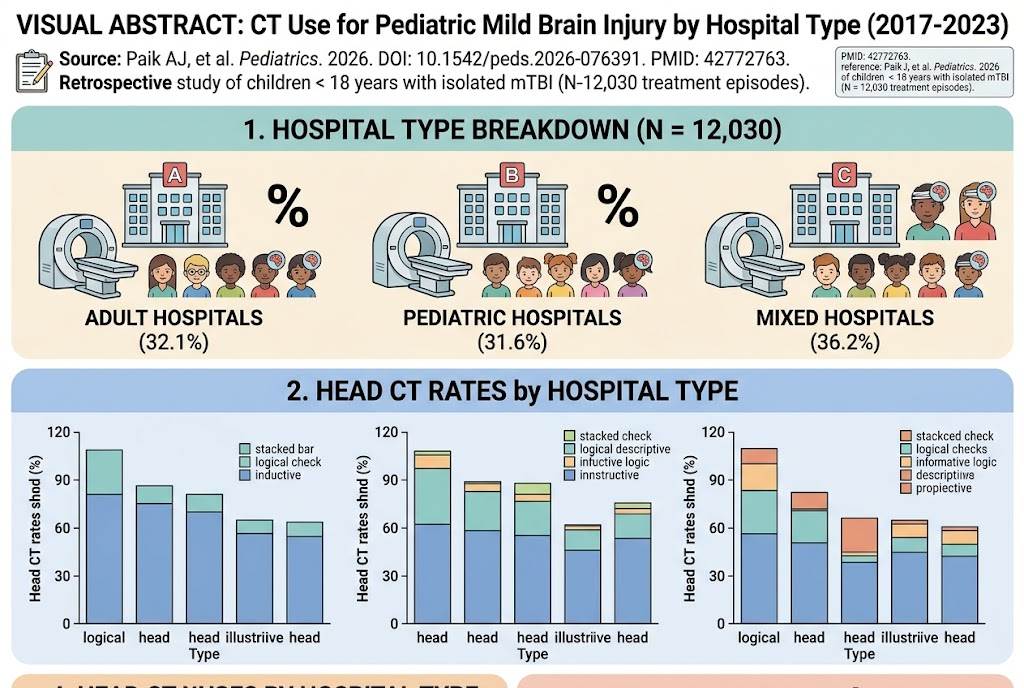
- Head CT imaging use in children with mild traumatic brain injury (mTBI) remains high nationally, ranging from 43.5% to 51.5% between 2017 and 2023.
- Adult hospitals have the highest rates of CT use (59.5%) compared to mixed (44.0%) and pediatric hospitals (38.8%).
- Higher imaging rates correlate with lower Glasgow Coma Scale scores, impaired consciousness, nonteaching status, and smaller hospital size.
- The persistent variability and high use suggest gaps in adoption of clinical guidelines, calling for focused quality improvement strategies.
Study Background
Mild traumatic brain injury (mTBI) in pediatric populations is a common clinical problem accounting for substantial emergency care visits and healthcare costs. While head computed tomography (CT) is the standard diagnostic tool to exclude serious intracranial injury, its overuse in mild cases exposes children to unnecessary radiation risks and healthcare expenses. Current clinical guidelines, including those from the American College of Emergency Physicians (ACEP) and the Pediatric Emergency Care Applied Research Network (PECARN), recommend selective use of CT based on clinical risk stratification to avoid unnecessary imaging. Despite established guidelines, prior studies have documented wide practice variation and generally persistently high CT utilization rates. Understanding how CT utilization patterns vary by hospital type and patient or institutional factors is critical for identifying targets to improve guideline adherence, minimize unwarranted imaging, and enhance resource allocation.
Study Design
This retrospective observational study used data from the National Trauma Data Bank (NTDB) from 2017 to 2023, incorporating pediatric patients with isolated mTBI aged older than 18 years — likely a typographical error, probably including those younger than 18 years — treated at participating hospitals. Hospitals were classified as adult, pediatric, or mixed by their American College of Surgeons (ACS) verification level and state-level designations. Annual rates of head CT usage were computed with 95% bootstrap confidence intervals overall and stratified by demographics (age, sex, race, insurance), clinical features (Glasgow Coma Scale score, consciousness impairment), and hospital characteristics (trauma center level, teaching status, size). Subgroup analyses examined CT rates among those scanned.
Key Findings
Over the study period, 12,030 pediatric patients with isolated mTBI were identified. The distribution of care was nearly equal across hospital types: 32.1% adult, 31.6% pediatric, and 36.2% mixed hospitals. Despite guideline efforts, overall head CT utilization remained high and relatively stable, from 43.5% to 51.5% annually.
Adult hospitals exhibited the highest imaging rates (59.5%) consistently, followed by mixed hospitals at 44.0% and pediatric hospitals at 38.8%. This pronounced variability suggests divergent clinical practice patterns by hospital type.
Increased CT use was strongly associated with clinical indicators of increased injury severity, notably a lower Glasgow Coma Scale (GCS) score and impaired consciousness, aligning with guideline-directed risk stratification. Notably, nonteaching and smaller hospitals also showed higher imaging rates, potentially reflecting differences in resource availability, provider experience, or institutional protocols.
Regarding patient demographics, scanned patients skewed toward male, white, privately insured, and treated predominantly at Level I or II trauma centers, though racial and insurance status disparities warrant further study.
Expert Commentary
This rigorous analysis highlights a paradox in pediatric mTBI management — despite established clinical criteria to minimize CT exposure, imaging remains overused in many contexts, especially adult hospitals that may lack pediatric-specific expertise or protocols. The higher use in adult and smaller, nonteaching hospitals raises concerns about system-level barriers to guideline implementation, including knowledge gaps, workflow challenges, or medico-legal influences.
The study underscores the need for tailored interventions, such as provider education, decision support tools integrated into electronic health records, and institutional policies promoting guideline adherence. It also suggests that pediatric hospitals may serve as centers of excellence for evidence-based mTBI care, potentially offering models for broader dissemination.
Limitations include potential misclassification of hospital type, reliance on NTDB data which may not capture all relevant clinical variables, and possible inconsistency in GCS reporting. Also, there may be contextual factors, such as parental pressure or local practice culture, influencing imaging decisions but not captured in the data.
Conclusion
The persistent high and variable use of head CT scans for pediatric mild traumatic brain injuries across hospital types reveals critical gaps in guideline dissemination and adherence. Such overutilization poses avoidable risks and costs without demonstrated benefit in low-risk cases. Focused quality improvement efforts are essential to harmonize clinical practice with evidence-based guidelines, particularly targeting adult and nonteaching hospitals.
Future research should investigate specific barriers to guideline adoption, explore the impact of decision support interventions, and assess long-term outcomes related to imaging practices. Aligning pediatric mTBI management nationwide with established standards could significantly enhance patient safety and healthcare resource stewardship.
Funding and ClinicalTrials.gov
No funding source or clinical trial registration information was provided in the study abstract.
References
1. Kuppermann N, Holmes JF, Dayan PS, et al. Identification of children at very low risk of clinically-important brain injuries after head trauma: a prospective cohort study. Lancet. 2009;374(9696):1160-1170.
2. American College of Emergency Physicians. Clinical policy: neuroimaging and decisionmaking in adult mild traumatic brain injury in the acute setting. Ann Emerg Med. 2014;64(4):347-356.
3. Nigrovic LE, Kuppermann N, Lamantia MA, et al. Effect of Cranial Computed Tomography on Emergency Department Length of Stay and Hospital Admission Rates in Children With Minor Head Trauma. J Pediatr. 2012;161(5):871-876.
4. Lumba-Brown A, Yeates KO, Sarmiento K, et al. Centers for Disease Control and Prevention guideline on the diagnosis and management of mild traumatic brain injury among children. JAMA Pediatr. 2018;172(11):e182853.
5. Smith A, Baumann A, Hoffman JR, et al. Variation in CT use for pediatric minor head trauma—national trauma data bank. Pediatr Emerg Care. 2016;32(8):524-529.
6.Paik AJ, Osong B, Armstrong M, Sribnick EA, Stanley R, Groner JI, Cook LJ, Lu B, Xiang H. CT Use for Pediatric Mild Brain Injuries by Hospital Type: 2017 to 2023. Pediatrics. 2026 Sep 23:e2026076391. doi: 10.1542/peds.2026-076391. Epub ahead of print. PMID: 42772763.
—
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.