Optimizing Bridging Therapy Before BCMA-Directed CAR T-Cell Treatment in Relapsed/Refractory Multiple Myeloma: A Real-World Multicenter Analysis
Highlight
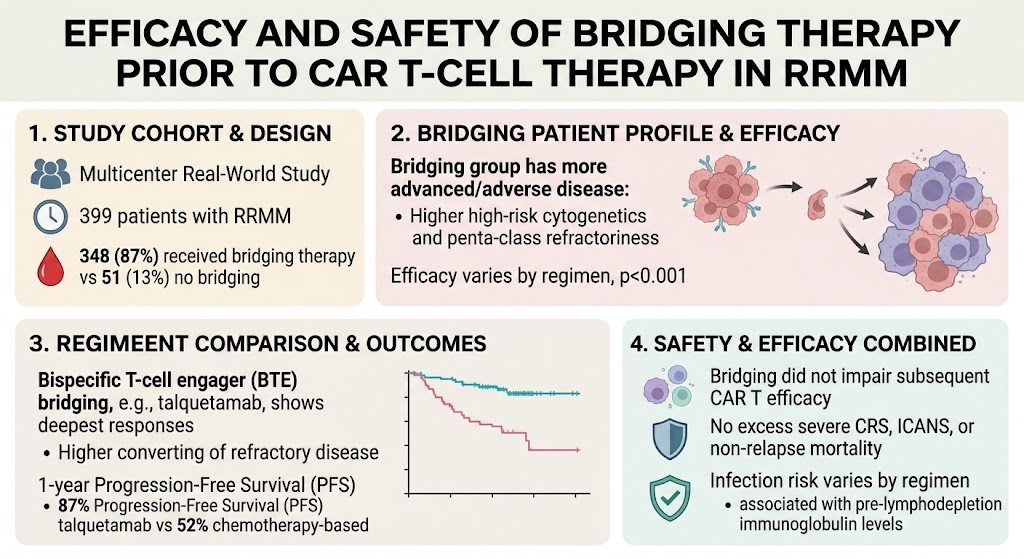
- Bridging therapy is administered in 87% of RRMM patients undergoing BCMA-directed CAR T-cell therapy to prevent disease progression during manufacturing delay.
- Patients receiving bridging therapy exhibit more advanced and biologically aggressive disease, including higher rates of high-risk cytogenetics and penta-class refractoriness.
- Bridging therapy efficacy varies significantly by regimen used, with implications for disease control and safety prior to CAR T-cell infusion.
- These real-world data underscore the necessity for tailored bridging approaches and further prospective studies to optimize outcomes in RRMM patients receiving CAR T-cell therapy.
Study Background
Relapsed or refractory multiple myeloma (RRMM) remains a therapeutic challenge despite advances in targeted therapies. Among emerging approaches, B-cell maturation antigen (BCMA)-directed chimeric antigen receptor (CAR) T-cell therapy has demonstrated promising efficacy. However, the disease burden at the time of CAR T-cell infusion critically influences patient outcomes, with higher tumor load correlating with inferior responses and survival.
Disease progression often occurs during the manufacturing time required for CAR T-cell production, commonly several weeks following leukapheresis. Bridging therapy—interim anti-myeloma treatment administered in this interval—is utilized clinically to prevent rapid disease progression and maintain disease control. However, the clinical benefit and safety profile of bridging therapy options across various regimens have not been definitively established in the RRMM population. This represents an important unmet need in optimizing CAR T-cell therapy efficacy and minimizing adverse events.
Study Design
This investigation was a multicenter real-world cohort study involving 399 patients with relapsed or refractory multiple myeloma who underwent BCMA-directed CAR T-cell therapy. The study population included 348 patients (87%) who received bridging therapy between leukapheresis and CAR T-cell infusion and a minority who did not receive such therapy. Patients were characterized by disease status, cytogenetic risk, and refractoriness to prior therapies.
Bridging regimens varied and encompassed several classes of anti-myeloma agents. The study analyzed the efficacy of different bridging regimens in terms of disease control, response rates, and safety events to correlate bridging strategy with outcomes post-CAR T-cell infusion. Endpoints included progression-free survival, overall survival, treatment-related toxicity, and the impact of disease burden at infusion on CAR T-cell effectiveness.
Key Findings
The study revealed that patients who received bridging therapy generally had more advanced disease features, including a higher frequency of high-risk cytogenetics and penta-class refractory status (refractory to at least five major classes of anti-myeloma drugs), reflecting a more challenging patient population.
Effectiveness of bridging therapy varied considerably by the regimen used. Certain regimens demonstrated superior ability to control disease progression during the manufacturing phase, translating to better disease status at the time of CAR T-cell infusion. Conversely, less effective bridging resulted in higher tumor burden at infusion, which correlated with worse CAR T-cell therapy outcomes.
Safety profiles of bridging regimens also differed. Some regimens were associated with increased toxicity or immune suppression, which could potentially impact the safety and efficacy of subsequent CAR T-cell infusion. Careful selection of bridging therapy is essential to minimize overlapping toxicities and preserve patient fitness for CAR T-cell administration.
The data support the concept that controlling disease burden pre-infusion is pivotal. The balance between adequate disease control and minimizing additional toxicity from bridging regimens is crucial to optimize the CAR T-cell therapy window.
Expert Commentary
Expert opinion recognizes the importance of bridging therapy as a pragmatic approach to manage disease progression risk while awaiting CAR T-cell manufacturing. However, there is consensus on the need to individualize bridging therapy based on patient disease biology, disease kinetics, and prior treatment exposures. This multicenter real-world study adds valuable evidence on the heterogeneity of bridging regimen outcomes and stresses the importance of prospective trials to define optimal bridging protocols.
Current guidelines highlight bridging therapy but lack specific recommendations on regimen choice or sequencing, indicating a gap in clinical consensus and standardization. Mechanistically, lower disease burden at the time of CAR T infusion is hypothesized to reduce immune exhaustion and improve CAR T-cell expansion and persistence, boosting efficacy.
Limitations of the study include its observational real-world design, which may introduce selection bias and heterogeneity in clinical decision-making. Nevertheless, these data provide a robust foundation for future controlled research.
Conclusion
Bridging therapy prior to BCMA-directed CAR T-cell infusion in RRMM is commonly employed and critically impacts disease burden and outcomes. This extensive real-world study reveals significant variability in bridging therapy effectiveness and safety profiles correlated with patient disease characteristics. Achieving optimal disease control before CAR T-cell infusion while limiting toxicity is essential for enhancing therapeutic success.
Prospective studies are urgently needed to establish evidence-based bridging strategies, guiding regimen selection to improve clinical response rates and minimize complications in the RRMM setting. Personalized bridging therapy, informed by biological risk and treatment history, represents a forward path to maximizing the transformative potential of CAR T-cell therapy in multiple myeloma.
Funding and Clinical Trials Registration
The published study by Wesener et al. does not specify funding sources in the abstract. Details on trial registration, if applicable, should be retrieved from the original publication or clinical trial databases.
References
1. Wesener MC, Demel UM, Pabst T, Teipel R, Albici AM, Von Tresckow B, et al. Efficacy and safety of bridging therapy prior to CAR T-cell therapy in relapsed or refractory multiple myeloma. Haematologica. 2026 Sep 3. PMID: 42687830.
2. Brudno JN, Kochenderfer JN. Chimeric antigen receptor T-cell therapies for lymphoma. Nat Rev Clin Oncol. 2018;15(1):31-46.
3. Munshi NC, Anderson LD Jr, Shah N, et al. Idecabtagene vicleucel in relapsed and refractory multiple myeloma. N Engl J Med. 2021 Apr 22;384(8):705-716.
4. National Comprehensive Cancer Network. NCCN Clinical Practice Guidelines in Oncology Multiple Myeloma. Version 5.2024.
5. Kumar S, Paiva B, Anderson KC, et al. International Myeloma Working Group consensus criteria for response and minimal residual disease assessment in multiple myeloma. Lancet Oncol. 2016;17(8):e328-e346.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.