Optimizing Acellular Dermal Matrix Timing in 2-Stage Prepectoral Breast Reconstruction: Balancing Capsular Contracture and Complications
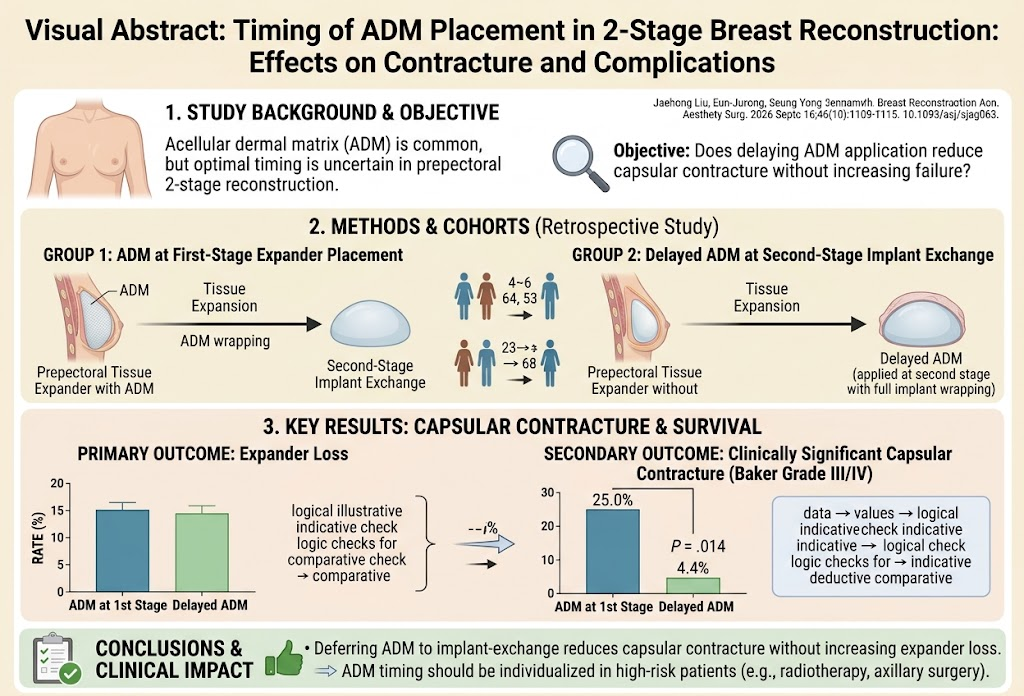
Highlight
• Delaying ADM placement to the second-stage implant exchange significantly reduces the incidence of clinically meaningful capsular contracture in prepectoral 2-stage breast reconstruction.
• Tissue expander loss rates are comparable between early and delayed ADM application.
• Delayed ADM use is associated with higher seroma occurrence in patients receiving postmastectomy radiotherapy and/or axillary lymph node dissection.
• Individualizing ADM timing based on patient risk factors, coupled with seroma mitigation strategies, may optimize reconstruction outcomes.
Study Background
Implant-based breast reconstruction is among the most common reconstructive procedures performed after mastectomy for breast cancer. The use of acellular dermal matrix (ADM) has become widespread as it can provide structural support, improve aesthetic outcomes, and potentially reduce postoperative complications such as capsular contracture. Capsular contracture—the pathological tightening of the fibrous capsule around the implant—remains a significant clinical challenge, potentially leading to pain, deformity, and need for revision surgery.
In prepectoral 2-stage tissue expander-implant reconstruction, ADM is typically used either at the initial tissue expander placement (first stage) or delayed until the definitive implant exchange (second stage). However, optimal timing of ADM placement remains uncertain, with limited data regarding its impact on capsular contracture rates and other complications such as expander loss, seroma, hematoma, and infection.
Study Design
This investigation was a retrospective cohort study conducted at a single institution, analyzing adult women undergoing immediate, prepectoral 2-stage tissue expander breast reconstruction. Patients were stratified into two groups based on timing of ADM placement: one group received ADM at the first-stage expander insertion, while the other group underwent delayed ADM application at the second-stage implant exchange, wherein ADM was used to fully wrap the implant.
The primary endpoint was tissue expander loss, an indicator of reconstructive failure. Secondary outcomes included rates of seroma, hematoma, infection, and capsular contracture assessed using the Baker grading scale, focusing on clinically significant contracture defined as Baker grade III or IV. Multivariable logistic regression adjusted for confounding variables such as body mass index (BMI), mastectomy weight, chemotherapy status, and cancer stage.
Key Findings
The study found no statistically significant difference in tissue expander loss between early versus delayed ADM placement groups, indicating similar reconstructive success rates regardless of ADM timing.
Early postoperative complications including hematoma and infection were comparable in both cohorts. However, delayed ADM application was linked to a higher frequency of seroma events, particularly pronounced among patients who had received postmastectomy radiotherapy and/or undergone axillary lymph node dissection—procedures known to increase lymphatic disruption and seroma risk.
Crucially, delayed ADM placement at implant exchange was associated with a markedly lower incidence of clinically meaningful capsular contracture (4.4%) compared with ADM use at the initial tissue expander stage (25.0%). This difference was statistically significant (P = .014) and persisted after adjusting for relevant covariates, with an adjusted odds ratio of 0.13 (95% CI, 0.02–0.89; P = .038), suggesting a strong protective effect against contracture by deferring ADM application.
Expert Commentary
The findings provide important clinical insights into the timing of ADM use in prepectoral breast reconstruction. Capsular contracture is a multifactorial process influenced by inflammation, fibrosis, and foreign body response. Delaying ADM application until the definitive implant placement may reduce early inflammatory stimuli associated with initial tissue expansion, thereby lowering contracture risk. Additionally, the full wrapping technique of ADM at the second stage may provide more uniform implant coverage and support, enhancing biocompatibility.
Nonetheless, the increased seroma observed with delayed ADM in patients undergoing radiotherapy or extensive axillary surgery warrants cautious patient selection. Seroma can predispose to infection and may complicate reconstruction. Surgeons should consider adjunctive techniques such as meticulous hemostasis, use of closed suction drains, or fibrin sealants to mitigate seroma formation in this subset.
Limitations of the study include its retrospective design and single-center setting, which may limit generalizability. Prospective randomized trials are necessary to confirm these findings and to establish standardized protocols for ADM timing tailored to individual patient risk profiles.
Conclusion
In summary, this study supports the strategy of delaying ADM placement to the second-stage implant exchange in prepectoral 2-stage breast reconstruction to reduce capsular contracture without increasing tissue expander loss. Clinicians should individualize ADM timing decisions based on patient-specific factors such as radiotherapy and axillary surgery status, with careful attention to seroma prevention. Adoption of this tailored approach has potential to improve reconstructive outcomes and patient satisfaction.
Funding and Clinical Trial Registration
The original study did not specify funding sources or clinicaltrials.gov registration. Future studies should ensure transparency regarding funding and registration to enhance research quality and reproducibility.
References
1. Liu J, Yang EJ, Song SY. Timing of Acellular Dermal Matrix Placement in 2-Stage Breast Reconstruction: Effects on Contracture and Complications. Aesthetic Surgery Journal. 2026;46(10):1109-1115. PMID: 41947611
2. Sbitany H, Piper M, Hess CL, et al. Prepectoral breast reconstruction: rationale, indications, and preliminary results. Plast Reconstr Surg. 2017;139(2):287-294.
3. Nahabedian MY. Acellular dermal matrix in secondary breast reconstruction. Plast Reconstr Surg. 2012;130(1):70S-79S.
4. Spear SL, Onyewu C. Staging strategies for breast reconstruction in the setting of postmastectomy radiation therapy. Plast Reconstr Surg. 2006;118(4 Suppl):61S-69S.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.