Highlight
- Octreotide therapy significantly reduces plasma catecholamine levels in patients with catecholamine-secreting pheochromocytomas and paragangliomas (PPGLs).
- Adjunctive treatment with octreotide leads to improved blood pressure control and glycemic parameters in this patient population.
- Octreotide may serve as a safe and effective bridge to surgery and in perioperative preparation for PPGL patients.
Study Background
Pheochromocytomas and paragangliomas (PPGLs) are rare neuroendocrine tumors arising from chromaffin cells of the adrenal medulla or extra-adrenal paraganglia, respectively. These tumors often hypersecrete catecholamines (primarily norepinephrine, epinephrine, and sometimes dopamine), resulting in challenging clinical manifestations such as hypertension, tachyarrhythmias, and metabolic disturbances including hyperglycemia. Effective management before surgical resection is critical due to the potential risk of catecholamine surges leading to hypertensive crises and other cardiovascular events. While alpha- and beta-adrenergic blockade remain mainstays of preoperative management, some cases remain refractory or difficult to stabilize. This underscores an unmet clinical need for adjunct therapies that target tumor biology more directly.
Somatostatin receptors are expressed in many neuroendocrine tumors, including PPGLs, providing a therapeutic rationale for somatostatin analogs like octreotide. However, clinical evidence supporting their use specifically in catecholamine-secreting PPGLs has been limited.
Study Design
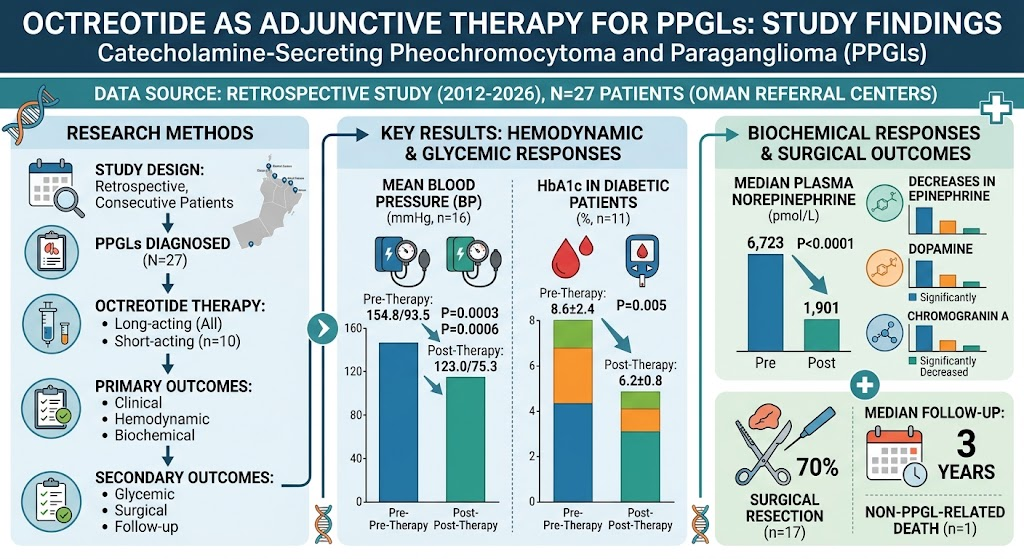
This retrospective cohort study evaluated 27 consecutive patients with biochemically active PPGLs treated with octreotide at two tertiary referral centers in Muscat, Oman, between January 2012 and March 2026. The cohort consisted of 14 paragangliomas and 13 pheochromocytomas. All patients received long-acting octreotide formulations, with a subset (10 patients) also receiving short-acting octreotide.
The primary outcomes included clinical response defined by symptom control, hemodynamic stability (blood pressure measurements), and biochemical response measured by plasma catecholamine levels and chromogranin A concentrations. Secondary outcomes assessed were glycemic control (HbA1c levels), surgical outcomes following tumor resection, and long-term follow-up data including mortality.
Key Findings
Following octreotide treatment, median plasma norepinephrine levels decreased significantly from 6,723 to 1,901 pmol/L (P < 0.0001). Corresponding significant reductions were observed in plasma epinephrine, dopamine, and chromogranin A. These biochemical improvements parallel with clinical stabilization correlating to better symptom control and less catecholamine-induced toxicity.
Hemodynamically, mean systolic blood pressure decreased markedly from 154.8 mmHg to 123.0 mmHg (P = 0.0003), and mean diastolic pressure from 93.5 mmHg to 75.3 mmHg (P = 0.0006) in 16 evaluable patients. These results demonstrate improved blood pressure control—crucial for reducing perioperative cardiovascular risk.
Among the 11 patients with diabetes, mean HbA1c levels improved significantly from 8.6% ± 2.4 to 6.2% ± 0.8 (P = 0.005), indicating a favorable metabolic effect possibly mediated by reduced catecholamine excess or a direct effect of octreotide on pancreatic islet function.
Seventeen patients underwent surgical resection after octreotide treatment. The perioperative period was reportedly uneventful with no PPGL-related mortality. Over a median follow-up of 3 years, only one non-PPGL-related death occurred, suggesting octreotide’s safety as an adjunct in preparation for and during surgery.
Expert Commentary
This study adds valuable clinical evidence supporting the targeted use of somatostatin analogs in patients with biochemically active PPGLs. Prior treatments focusing solely on adrenergic blockage do not modify tumor secretory activity. Octreotide, by binding somatostatin receptors expressed on PPGL cells, may suppress catecholamine secretion at its source, thereby improving hemodynamic control and reducing systemic toxic effects.
Limitations include the retrospective design, modest sample size, and lack of a control group. Additionally, long-term oncologic outcomes with octreotide remain to be established. Nevertheless, the consistent biochemical and clinical improvements underscore biological plausibility and therapeutic promise.
Future prospective studies and randomized controlled trials could clarify optimal dosing strategies, identify predictive markers of response (such as somatostatin receptor subtypes), and evaluate combined modalities including newer somatostatin analogs with higher receptor affinity or radiolabeling for theranostic applications.
Conclusion
Octreotide represents a valuable adjunctive treatment for catecholamine-secreting pheochromocytomas and paragangliomas, demonstrating significant biochemical, hemodynamic, and metabolic improvements. Its use as a bridging therapy before surgery and during perioperative preparation may enhance patient safety and surgical outcomes. This approach addresses the critical challenge of stabilizing patients with PPGLs who are difficult to manage with standard adrenergic blockade alone.
Clinicians should consider incorporating somatostatin receptor-targeted therapies like octreotide in managing select patients with catecholamine-secreting PPGLs, while awaiting further prospective validation.
Funding and ClinicalTrials.gov
The study was conducted without external funding disclosures. No clinical trial registration was reported, consistent with the retrospective observational study design.
References
- Elshafie O, Bou Khalil A, Salman BH, Itkin BL, Woodhouse N, Alzahrani AS. Octreotide as Adjunctive Therapy for Catecholamine-Secreting Pheochromocytoma and Paraganglioma. J Clin Endocrinol Metab. 2026 Aug 21:dgag343. doi: 10.1210/clinem/dgag343. Epub ahead of print. PMID: 42626938.
- Lenders JWM, Duh Q-Y, Eisenhofer G, et al. Pheochromocytoma and Paraganglioma: An Endocrine Society Clinical Practice Guideline. J Clin Endocrinol Metab. 2014 Jun;99(6):1915-42. doi:10.1210/jc.2014-1498.
- Plouin PF, Gimenez-Roqueplo AP, Lenders JW, et al. Pheochromocytoma and paraganglioma: management of systolic hypertension. Endocr Pract. 2021;27(5):511-519. doi:10.4158/EP-2020-0435.
- Yao JC, Pavel M, Lombard-Bohas C, et al. Everolimus for advanced pancreatic neuroendocrine tumors. N Engl J Med. 2011 Feb 17;364(6):514-23. doi:10.1056/NEJMoa1009290.