Lidocaine Versus Amiodarone for Refractory Ventricular Fibrillation in Adult In-Hospital Cardiac Arrest: Evidence from a Nationwide Chinese Registry
Highlight
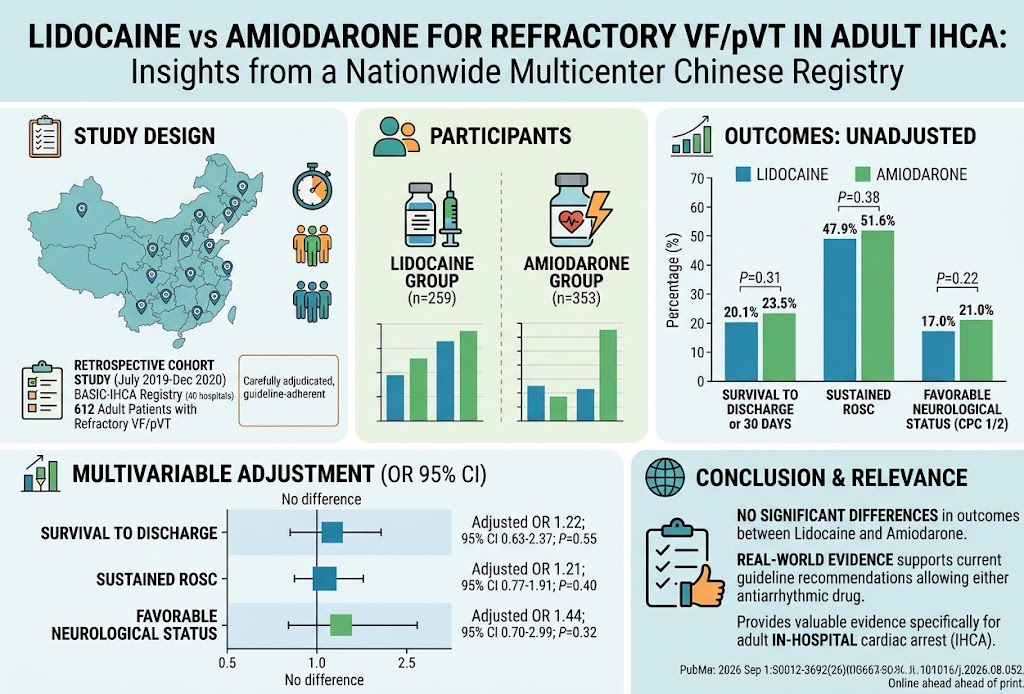
This multicenter prospective registry study evaluated the comparative effectiveness of lidocaine and amiodarone for refractory ventricular fibrillation (VF) or pulseless ventricular tachycardia (pVT) during adult in-hospital cardiac arrest (IHCA). It found no statistically significant differences in survival to hospital discharge, sustained return of spontaneous circulation (ROSC), or favorable neurological outcomes between the two drugs, supporting current resuscitation guidelines endorsing either agent.
Study Background
Ventricular fibrillation (VF) and pulseless ventricular tachycardia (pVT) are life-threatening arrhythmias commonly encountered during cardiac arrest. Prompt defibrillation and antiarrhythmic drug therapy are cornerstones of advanced cardiac life support (ACLS). While out-of-hospital cardiac arrest (OHCA) literature has informed current guidelines recommending amiodarone or lidocaine for refractory VF/pVT, evidence specifically focused on adult in-hospital cardiac arrest (IHCA) is scarce. IHCA patients often have distinct clinical profiles, comorbidities, and arrest etiologies compared to OHCA cases. Therefore, it is critical to clarify whether lidocaine or amiodarone yields superior outcomes in this population to optimize resuscitation practices and allocation of healthcare resources.
Study Design
This analysis used data from the Baseline Investigation of In-Hospital Cardiac Arrest (BASIC-IHCA), a nationwide, multicenter, prospective registry collecting Utstein-style IHCA data from 40 Chinese hospitals between July 2019 and December 2020. Adults with refractory VF/pVT—defined as persisting after initial defibrillation attempts—who received either lidocaine or amiodarone during resuscitation were included.
Key methodology components included rigorous case adjudication by medical record review to ensure accurate indication for antiarrhythmic drug use per guideline recommendations. Primary outcome was survival to hospital discharge or at 30 days. Secondary outcomes comprised sustained ROSC and favorable neurological status at discharge or 30 days, defined as Cerebral Performance Category (CPC) score 1 or 2. Multilevel mixed-effects logistic regression assessed associations, adjusting for confounders, with predefined subgroup analyses exploring effect consistency across patient subsets.
Key Findings
Among 32,545 adult IHCA events screened, 612 cases with refractory VF/pVT receiving lidocaine (n=259) or amiodarone (n=353) met inclusion criteria.
| Outcome | Lidocaine (n=259) | Amiodarone (n=353) | P-value |
|---|---|---|---|
| Survival to discharge/30 days | 20.1% | 23.5% | 0.31 |
| Sustained ROSC | 47.9% | 51.6% | 0.38 |
| Favorable neurological outcome (CPC 1/2) | 17.0% | 21.0% | 0.22 |
On multivariable adjustment—including hospital-level clustering and relevant clinical covariates—no statistically significant differences emerged between lidocaine and amiodarone groups: survival adjusted OR 1.22 (95% CI 0.63-2.37; P=0.55), sustained ROSC adjusted OR 1.21 (95% CI 0.77-1.91; P=0.40), and neurological outcome adjusted OR 1.44 (95% CI 0.70-2.99; P=0.32). Exploratory subgroup analyses stratified by age, initial rhythm type, or comorbidities consistently showed no meaningful interaction with treatment effect.
No increased safety signals or adverse events attributable to either drug were reported, although the study primarily focused on effectiveness outcomes.
Expert Commentary
This study provides important real-world evidence directly addressing a knowledge gap in IHCA resuscitation pharmacotherapy. Prior randomized controlled trials and meta-analyses have predominantly enrolled OHCA patients, leaving the IHCA population underrepresented despite differing clinical characteristics and arrest settings. The rigorous registry design, broad patient inclusion across diverse Chinese hospitals, and careful adjudication enhance the robustness and generalizability of findings within similar healthcare contexts.
The absence of significant difference between lidocaine and amiodarone supports current international ACLS guidelines that consider both medications acceptable options for refractory VF/pVT. Given amiodarone’s complex pharmacologic profile, potential drug interactions, and longer half-life, lidocaine—being more readily available and easier to administer—may be equally appropriate in many IHCA scenarios.
Limitations include the nonrandomized observational nature, which cannot exclude residual confounding despite adjustment. Also, the study focused on short-term outcomes without longer-term follow-up beyond 30 days. Differences in dosing protocols or timing of administration between centers were not detailed, which might influence effectiveness.
Future research could explore pharmacogenomic factors modulating response, integration of antiarrhythmic therapy with mechanical interventions (e.g., extracorporeal life support), and patient-centered long-term functional outcomes.
Conclusion
This nationwide multicenter Chinese registry study demonstrates that among adults experiencing in-hospital cardiac arrest with refractory ventricular fibrillation or pulseless ventricular tachycardia, lidocaine and amiodarone achieve comparable rates of survival, sustained ROSC, and favorable neurological outcomes. These findings provide high-quality, real-world evidence endorsing guideline recommendations which allow either agent during resuscitation, enhancing flexibility for clinicians managing complex IHCA cases.
Incorporating these data into clinical decision-making may facilitate optimized pharmacologic strategies tailored to institutional logistics and patient-specific factors, ultimately improving cardiac arrest outcomes. Continued research should refine the selection and timing of antiarrhythmic therapies to advance IHCA resuscitation care further.
Funding and Clinical Trials Registry
The study was supported by relevant Chinese research grants as described in the original publication. It is registered with clinical data collection in the BASIC-IHCA registry. Details on specific funding sources and trial registration numbers can be found in the original article.
References
- Niu X, Jiang T, Zheng W, et al. Comparative Effectiveness of Lidocaine and Amiodarone for Refractory VF/pVT in Adult In-Hospital Cardiac Arrest: Insights from a Nationwide Multicenter Chinese Registry. Chest. 2026 Sep 21; PMID: 42767592.
- Neumar RW, Shuster M, Callaway CW, et al. 2015 American Heart Association Guidelines Update for Cardiopulmonary Resuscitation and Emergency Cardiovascular Care. Circulation. 2015;132(18 Suppl 2):S315-67.
- Wang HE, Schmicker RH, Daya M, et al. Comparative Effectiveness of Lidocaine Versus Amiodarone for Shock-Refractory Out-of-Hospital Cardiac Arrest. Circulation. 2020;141(6):484-493.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.