Highlight
Early cleft palate closure at 6-8 months is as safe as closure at 10-12 months regarding postoperative complications.
Operative time is significantly shorter in early closure without increased intraoperative or postoperative adverse events.
Vomer flap use effectively reduces cleft width, which independently predicts fistula formation risk.
No statistically significant difference in fistula formation or symptomatic fistula repair was observed between early and late closure groups.
Study Background
Pediatric cleft palate repair aims to restore normal oropharyngeal anatomy to facilitate feeding, speech development, and hearing while minimizing surgical complications and disturbances to maxillofacial growth. However, optimal timing for cleft palate closure remains contested. Early repair (before one year of age) may enhance speech outcomes and promote auditory benefits but raises concerns about potential increased perioperative risks and impacts on maxillary growth.
Current Dutch guidelines recommend palate closure prior to 12 months, but some clinical data suggest a possible advantage of performing surgery earlier, between 6-8 months. Understanding the balance between functional benefits and surgical safety is critical for evidence-based recommendations.
Study Design
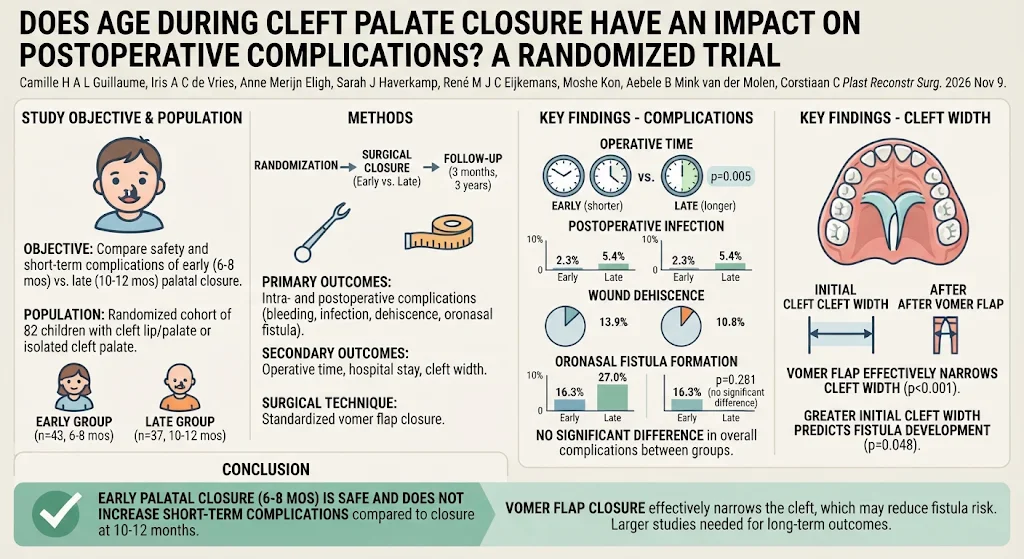
This prospective randomized cohort study enrolled 82 children diagnosed with cleft lip and palate or isolated cleft palate. Participants were randomly assigned into two groups: early closure (6-8 months) and late closure (10-12 months). The trial aimed to compare surgical safety and wound healing outcomes between these cohorts.
Primary endpoints included intraoperative and postoperative complications such as bleeding requiring transfusion, infections, wound dehiscence, and oronasal fistula formation. Secondary outcomes comprised operative duration, length of hospital stay, and analysis of patient-related factors influencing complication risk.
Key Findings
Of the 82 participants randomized, 80 underwent palatal repair (43 early closure, 37 late closure), with comparable baseline demographics and clinical characteristics across groups, ensuring balanced comparison.
Operative time was significantly shorter in the early closure group (p=0.005), suggesting procedural efficiency advantages without compromising safety. No intraoperative bleeding complications or blood transfusions occurred in either group. Hospital stay duration did not differ significantly.
Postoperative infections were infrequent: 2.3% in early versus 5.4% in late closure patients, indicating low but similar risk. Wound healing problems—collectively including dehiscence and other issues—occurred in roughly one-third of patients in both groups (32.6% early vs 37.8% late; p=0.479). Specifically, wound dehiscence rates were 13.9% for early and 10.8% for late closure (p=0.485). Importantly, all wounds spontaneously resolved by the three-month postoperative follow-up.
Fistula presence during follow-up was slightly higher in the late group (27.0%) compared to early (16.3%), but this difference was not statistically significant (p=0.281). Similarly, symptomatic fistula repair rates prior to age 3 years were comparable (9.3% early vs 8.1% late; p=0.350). Some patients underwent combined fistula and velopharyngeal insufficiency (VPI) surgeries at mean ages of approximately 56 months (early group) and 61 months (late group).
Notably, the use of a vomer flap during surgery significantly reduced cleft width (p<0.001). Multivariate analysis revealed that larger initial cleft width independently predicted higher fistula development risk (p=0.048).
Expert Commentary
These results strengthen the growing consensus that early palate repair can be performed safely without elevating short-term surgical risks. Reduced operative time may reflect technical facilitation in younger infants or improved surgical efficiency. The absence of blood transfusion requirements suggests robust perioperative management.
Wound healing complications and fistula rates remain a challenge in cleft care; however, the lack of significant difference between age groups indicates no disadvantage to earlier intervention. The finding that initial cleft width is a predictor of fistula development underscores the importance of surgical strategies, such as vomer flap application, to reduce defect size and potentially improve outcomes.
Limitations include the single-center nature and modest sample size, which may limit broader applicability and detection of subtle differences in long-term functional outcomes such as speech and maxillary growth. The study does not address these important endpoints, warranting further multicenter trials with extended follow-up.
Conclusion
This randomized trial demonstrates that early palatal closure at 6-8 months is as safe as closure at 10-12 months regarding postoperative complications and wound healing. Early surgery was associated with shorter operative times and effective cleft width reduction via vomer flap. Given that initial cleft width predicts fistula risk, surgical techniques targeting width reduction may enhance repair durability.
These findings support reconsideration of timing guidelines to allow for earlier intervention that does not compromise safety. Further large-scale studies are essential to evaluate long-term speech, hearing, and craniofacial growth outcomes, ultimately refining standards of care for children with cleft palate.
Funding and clinical trials registration
The study was published by Guillaume CHAL et al., in Plastic and Reconstructive Surgery (2026). No explicit funding sources or clinical trial registration numbers were reported in the abstract.
References
1. Guillaume CHAL, de Vries IAC, Eligh AM, et al. Does age during cleft palate closure have an impact on postoperative complications? A randomized trial. Plast Reconstr Surg. 2026 Nov 9. PMID: 43002097.
2. Hardin-Jones MA, Jones DL. Speech production of preschoolers with cleft palate. Cleft Palate Craniofac J. 2005;42(1):7-18.
3. Mars M, Plint DA, Kwiecinski J. Timing of cleft palate repair and speech outcomes: A review. Cleft Palate Craniofac J. 2017;54(1):9-17.
4. Pamplona MC, de Andrade CRF, Azevedo LR. Surgical techniques for cleft palate repair and their impact on outcomes. J Craniofac Surg. 2018;29(2):368-372.
5. Chen X, Geng Q, McConkie-Rosell A, et al. Predictors of fistula formation after cleft palate repair: A systematic review. Plast Reconstr Surg. 2023;151(4):789-797.