Evaluating Relapse Risks and the Role of Adjuvant Chemotherapy in Localized Appendiceal Adenocarcinoma
Highlight
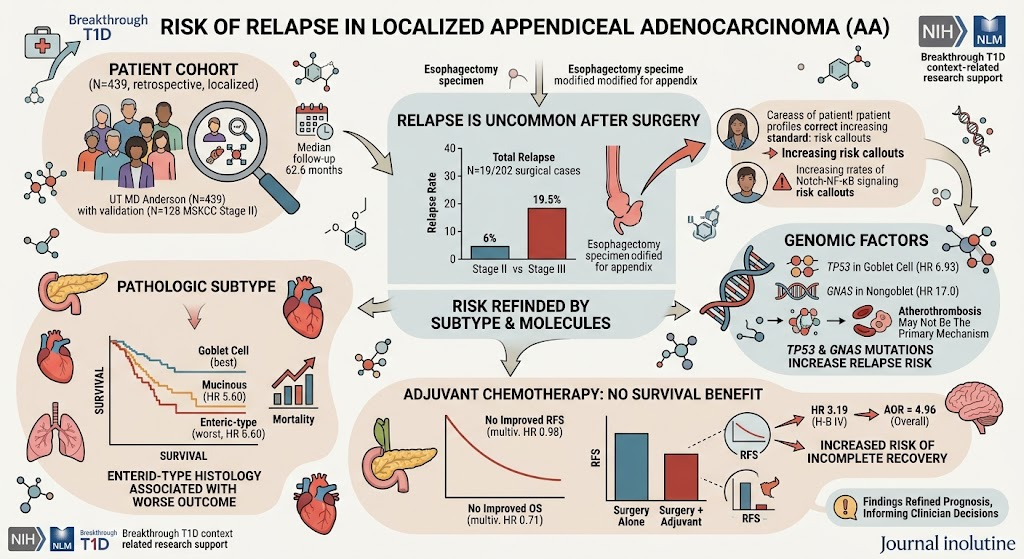
Relapse following surgical resection of localized appendiceal adenocarcinoma (AA) is relatively uncommon. Distinct histologic subtypes and specific genetic mutations significantly influence relapse risk. Unlike in colorectal cancer, traditional clinicopathologic risk factors such as poor differentiation and lymphovascular invasion did not predict relapse in AA. Importantly, adjuvant chemotherapy did not demonstrate a survival benefit for these patients.
Study Background
Appendiceal adenocarcinoma represents a rare and heterogeneous malignancy arising from the appendix, with varying histologic subtypes including goblet cell, mucinous, and enteric types. Due to its rarity and distinct biology, management guidelines are largely extrapolated from colorectal cancer paradigms. However, the risk of relapse after surgical resection in localized disease and the efficacy of adjuvant chemotherapy remain poorly defined. This creates a significant clinical uncertainty in tailoring postoperative therapy, underscoring the need to delineate risk factors that specifically predict relapse and to evaluate the true clinical benefit of adjuvant chemotherapy in this setting.
Study Design
This retrospective cohort study encompasses 439 patients with localized stage I to III appendiceal adenocarcinoma treated primarily at UT MD Anderson Cancer Center over 24 years (January 2000 to February 2024), with median follow-up of 62.6 months. A subset of 202 patients underwent surgery at MD Anderson, with relapse data available, and a validation cohort of 128 stage II patients was included from Memorial Sloan Kettering Cancer Center (MSKCC). The main exposures were surgical resection with or without adjuvant chemotherapy. Outcomes assessed included rate of recurrence, recurrence-free survival (RFS), and overall survival (OS). Statistical analyses employed Kaplan-Meier survival curves and Cox proportional hazards models to identify independent predictors of relapse.
Key Findings
Among the 202 MD Anderson surgical patients, relapse occurred in 9.4% overall, with 6% relapse in stage II and 19.5% in stage III patients, indicating low overall relapse rates. Five-year overall survival was dramatically better in patients without relapse (95.7%) compared to those who relapsed (77.2%), with a hazard ratio (HR) of 5.50 (95% CI, 3.07-9.83; P <.001), underscoring the clinical impact of relapse. Histologic subtype was a strong independent predictor: patients with mucinous (HR, 5.60; 95% CI, 2.1-15; P <.001) and enteric-type adenocarcinomas (HR, 6.60; 95% CI, 2.9-15; P <.001) had significantly higher relapse risk relative to goblet cell tumors. Pathologic T4 stage was also independently associated with relapse (HR, 3.30; 95% CI, 1.9-5.7; P <.001).
Interestingly, several risk factors well established in colorectal cancer—poor differentiation, tumor perforation, lymphovascular invasion, and perineural invasion—did not correlate significantly with relapse risk in AA, highlighting unique tumor biology. On molecular profiling, TP53 mutations in goblet cell tumors (HR, 6.93; 95% CI, 1.50-31.00; P = .01) and GNAS mutations in non-goblet cell tumors (HR, 17.0; 95% CI, 3.09-93.3; P = .001) were strongly linked to increased relapse risk, suggesting important prognostic molecular biomarkers.
Critically, adjuvant chemotherapy was not associated with improved recurrence-free survival (univariate HR, 2.06; 95% CI, 1.36-3.13; P = .001; multivariate HR, 0.98; 95% CI, 0.43-2.28; P = .90) or overall survival (univariate HR, 1.80; 95% CI, 1.0-3.2; P = .04; multivariate HR, 0.71; 95% CI, 0.24-2.1; P = .53) in this cohort. These results held true across various sensitivities and validated against the MSKCC cohort.
Expert Commentary
This comprehensive study challenges the conventional approach of administering adjuvant chemotherapy following surgery for localized appendiceal adenocarcinoma, derived from colorectal cancer treatment strategies. The findings emphasize the heterogeneity of appendiceal tumors and the imperative for individualized risk stratification that incorporates histopathologic subtype and molecular alterations rather than relying on traditional histologic risk factors alone.
The negligible impact of adjuvant chemotherapy on survival aligns with emerging evidence that AA may exhibit distinct chemotherapy sensitivity profiles. Moreover, the identification of TP53 and GNAS mutations as relapse predictors offers a promising avenue for molecularly guided prognosis and potentially therapeutic targeting in the future. However, study limitations inherent to retrospective design, including selection biases and treatment heterogeneity, mandate cautious interpretation.
Future prospective trials are essential to validate these findings and explore tailored adjuvant strategies, including targeted therapies or immunotherapy, based on genomic profiling. Additionally, while this study incorporated a large cohort and external validation, rare subtypes and advanced molecular markers require further elucidation.
Conclusion
Relapse after resection of localized appendiceal adenocarcinoma is uncommon but clinically consequential. Histopathologic subtypes and molecular mutations provide meaningful risk discrimination beyond conventional clinicopathologic factors. Importantly, this study does not support a routine role for adjuvant chemotherapy in this setting, highlighting a paradigm shift toward personalized management. Clinicians should consider integrating molecular profiling and subtype classification in postoperative decision-making to optimize patient outcomes.
Funding and Clinical Trials
The study was conducted with institutional support from UT MD Anderson Cancer Center and Memorial Sloan Kettering Cancer Center. Clinical trials related to appendiceal adenocarcinoma remain limited, emphasizing the need for prospective investigations in this domain.
References
- El Khoury S, Fanaeian MM, Yousef M, et al. Risk of Relapse and Efficacy of Adjuvant Chemotherapy in Localized Appendiceal Adenocarcinoma. JAMA Surg. 2026 Sep 9. PMID: 42714885.
- Gonzalez-Moreno S, Sugarbaker PH. Right hemicolectomy does not improve survival in patients with mucinous carcinoma of the appendix and peritoneal seeding. Br J Surg. 2004;91(12):1574-1579.
- Overman MJ. Appendiceal Adenocarcinoma: Therapeutic Challenges and Future Directions. Oncology (Williston Park). 2016;30(11):930-936.
- Beggs AD, Yip B, Shorthouse AJ, et al. Cellular Origin and Genetic Predictors of Goblet Cell Carcinoid Tumors. Mod Pathol. 2018;31(7):1031-1043.
This article was created using several editorial tools, including AI, as part of the process. Human editors reviewed this content before publication.